Related Experiment Video
Updated: Feb 3, 2026


Author Spotlight: Simulating Pediatric Cardiac Surgery Using a Neonatal Piglet Model
Published on: May 26, 2023
Use of antifibrinolytics in pediatric cardiac surgery: Where are we now?
David Faraoni1, Cornelius Rahe1, Karen A Cybulski1
1Division of Cardiac Anesthesia, Department of Anesthesia and Pain Medicine, The Hospital for Sick Children, University of Toronto, Toronto, Ontario, Canada.

Insights
Antifibrinolytic agents like tranexamic acid can reduce bleeding in pediatric cardiac surgery. Aprotinin is not recommended; further research is needed for optimal dosing of lysine analogs.
Area of Science:
- Pediatric Cardiac Surgery
- Hematology
- Pharmacology
Background:
- Fibrinolytic activation is a significant cause of bleeding in neonates and children during cardiac surgery with cardiopulmonary bypass.
- Prophylactic antifibrinolytic agents can mitigate this bleeding and reduce the need for blood transfusions, based on existing literature.
Purpose of the Study:
- To review the efficacy and safety of antifibrinolytic agents in pediatric cardiac surgery.
- To provide recommendations for the use of specific antifibrinolytics in this patient population.
Main Methods:
- Literature review of adult and pediatric studies on antifibrinolytic agents in cardiac and noncardiac surgery.
- Analysis of safety profiles, particularly renal failure and mortality risks associated with aprotinin.
- Evaluation of the effectiveness and side effects of lysine analogs (tranexamic acid, ϵ-aminocaproic acid).
Main Results:
- Aprotinin is not recommended for neonates and children due to safety concerns (renal failure, mortality).
- Lysine analogs, tranexamic acid and ϵ-aminocaproic acid, are considered safe and effective.
- High-dose tranexamic acid should be avoided to prevent seizures; optimal dosing remains under investigation.
Conclusions:
- Tranexamic acid and ϵ-aminocaproic acid are preferred antifibrinolytic agents for pediatric cardiac surgery.
- Further research is essential to determine optimal dosing regimens for lysine analogs in neonates and children.
- Additional doses may be necessary in cases of massive bleeding or observed fibrinolytic activation.
Abstract:
Fibrinolytic activation is a major and preventable source of bleeding in neonates and children undergoing cardiac surgery with cardiopulmonary bypass. Based on the existing literature (adult and pediatric; cardiac and noncardiac), prophylactic administration of antifibrinolytic agents can help reduce fibrinolytic activation, and consequently reduces perioperative bleeding and the requirement for blood product transfusion. Due to the increased risk of renal failure and mortality reported in adults undergoing cardiac surgery, aprotinin should not be considered as a safe option in neonates and children. Further well-designed studies would be required before the prophylactic administration of aprotinin could be considered in pediatric cardiac surgery. The lysine analogs, tranexamic acid and ϵ-aminocaproic acid,, should be considered as safe and effective antifibrinolytic agents. Although no major side effects have been reported following the administration of lysine analogs in children undergoing cardiac surgery, high-dose tranexamic acid should not be recommended in order to avoid the increased risk of clinical seizures. Despite the recent advances made in our understanding of the pharmacokinetics of tranexamic acid and ϵ-aminocaproic acid,, the optimal plasmatic concentration to be targeted remains unknown. Further studies are therefore urgently needed to better define the optimal dose regimen to be used in neonates and children. In the meantime, the dose regimen published in the most recent pharmacokinetic studies can be used. Although no studies have assessed the effect of massive bleeding and transfusion on the plasmatic concentrations of the lysine analogs, additional boluses might be considered in the presence of bleeding and/or when signs of fibrinolytic activations are observed on viscoelastic hemostatic assays.
More Related Videos


Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:19
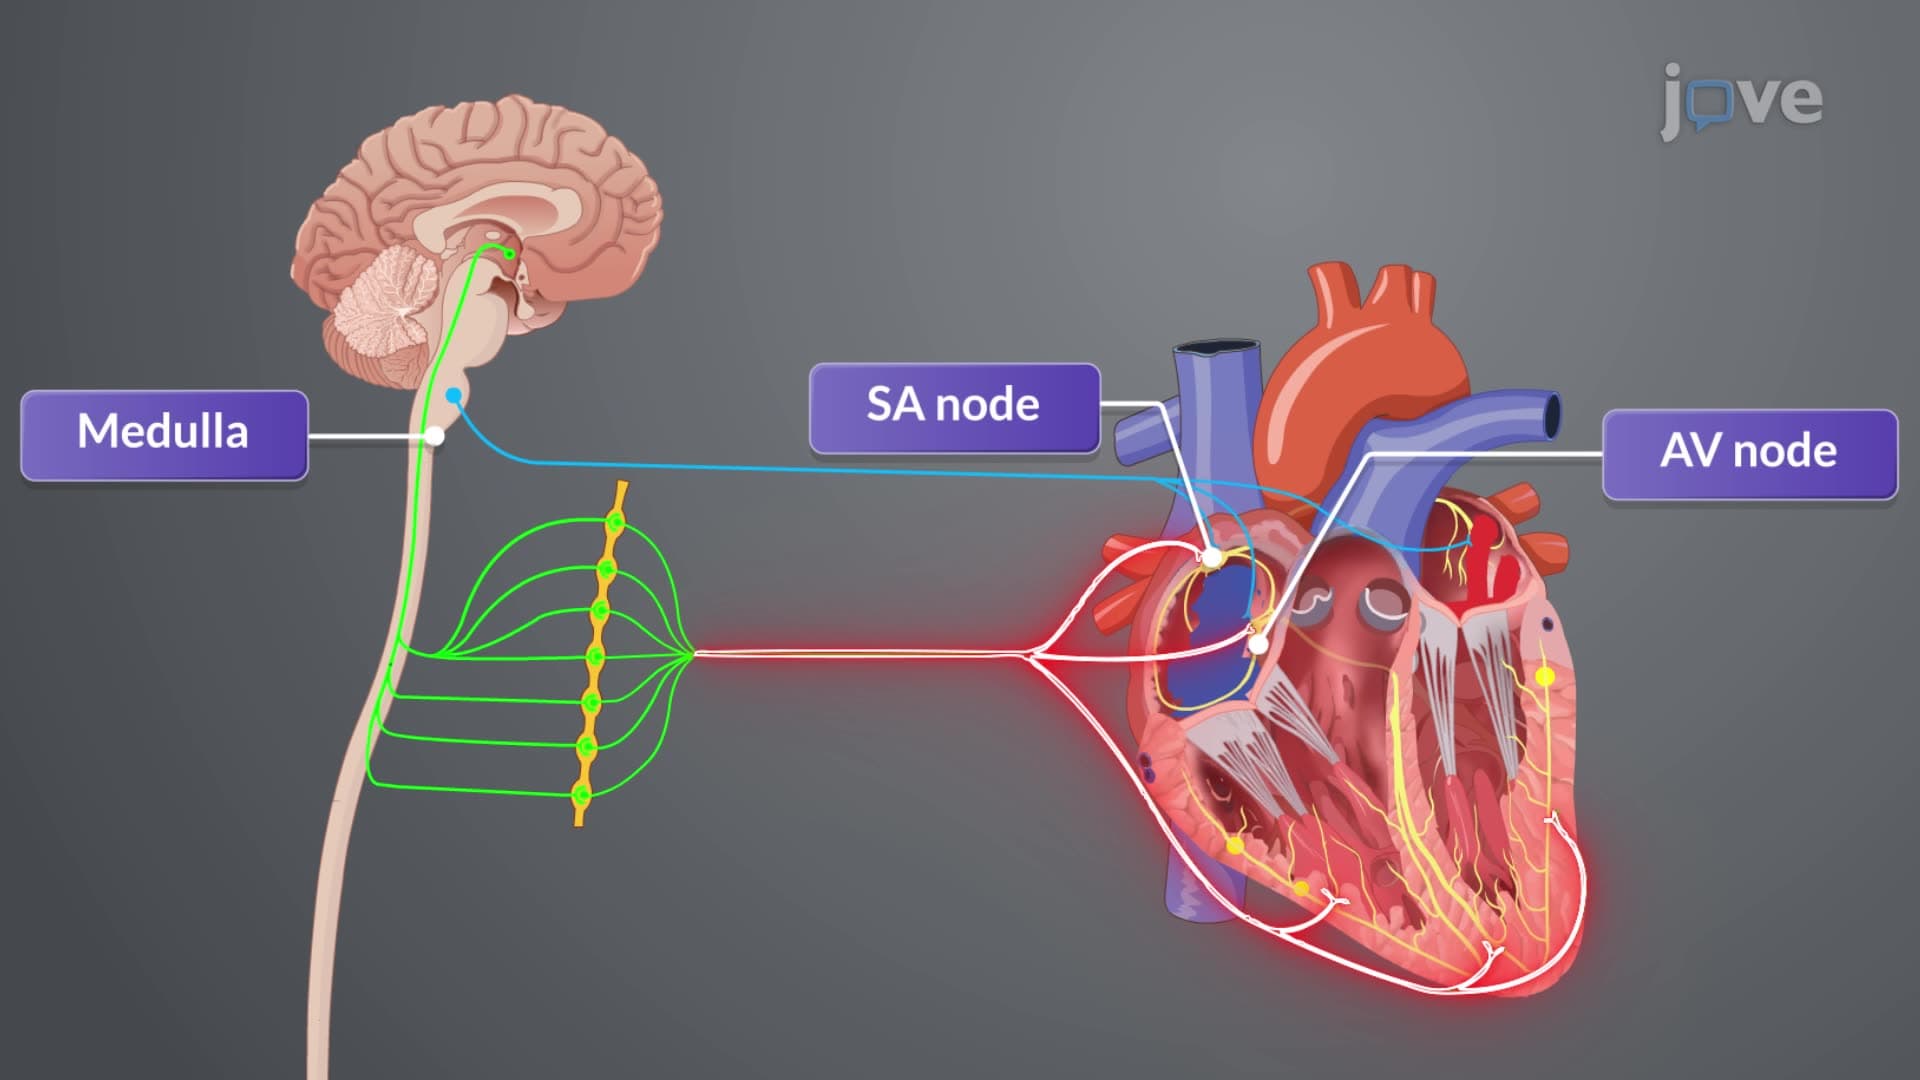
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...