Towards a non-invasive cardiac arrest monitor: An in vivo pilot study
John C Kucewicz1, David D Salcido2, Adeyinka A Adedipe3
1Applied Physics Laboratory, University of Washington, Seattle, WA, United States.

Introduction:
Hemodynamic-guided cardiopulmonary resuscitation (HGCPR) achieves better outcomes than standard resuscitation. Currently, HGCPR requires an invasive procedure, infeasible during resuscitation. Non-invasive measures of blood flow could provide useful hemodynamic guidance to rescuers.
Objective:
We describe initial efforts to develop a device that detects, analyzes, and measures the velocity of carotid artery blood flow (CABF) towards the brain at pre-arrest baseline ('baseline') and during cardiopulmonary resuscitation, here tested in a swine model of cardiac arrest (CA). A key element of that device consists of non-imaging diagnostic ultrasound, due to its simplicity and small form factor, hence potential for deployment during HGCPR in a bandage placed on the neck.
Methods:
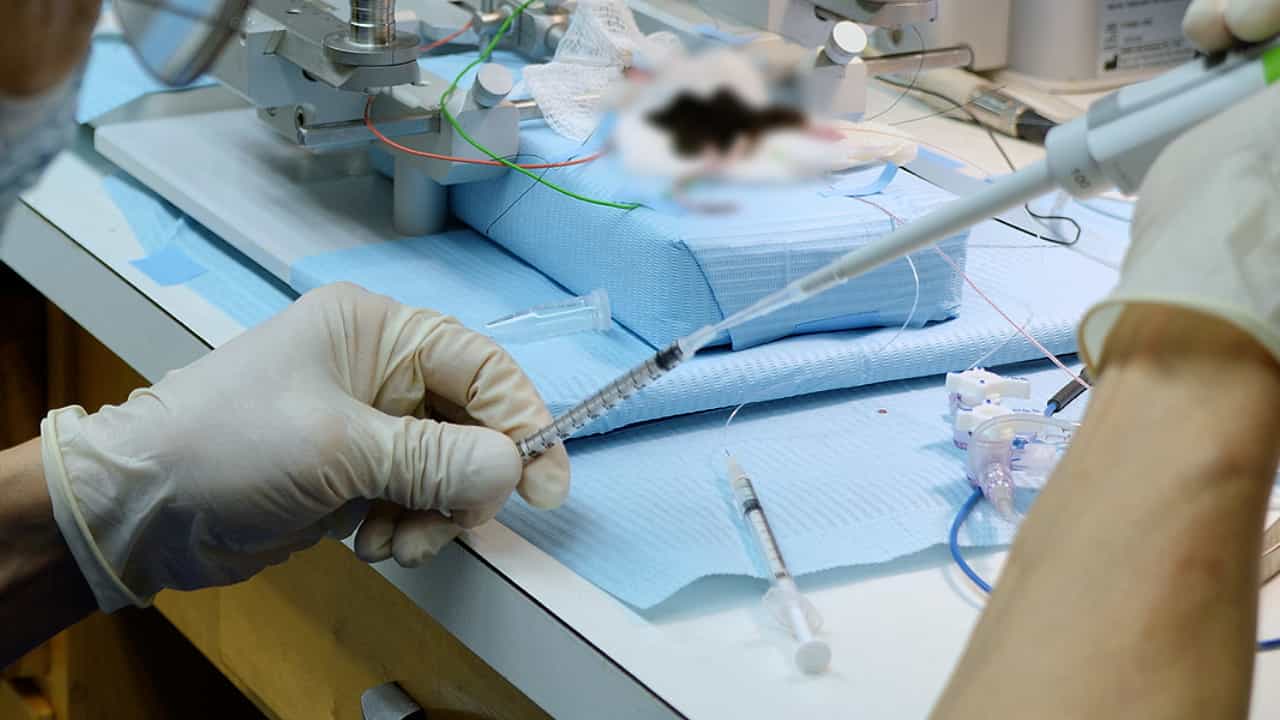
Sixteen mixed-breed domestic swine were sedated, anesthetized and paralyzed, followed by endotracheal intubation and mechanical ventilation. Cardiac arrest was induced with a 3-s 100 mA transthoracic shock or bolus of fentanyl, after which all animals received mechanical CPR. A non-imaging ultrasound probe was manually applied to the neck over the carotid artery to capture CABF during baseline, as verified with diagnostic ultrasound imaging, and during mechanical resuscitation.
Results:
We successfully collected CABF measurements at baseline in 14/16 swine and during attempted resuscitation with mechanical chest compression in 5/16 swine. Signal characteristics include peak blood flow both towards (90.4 +/-20.4 cm/s) and away from the brain (-44.2 +/-31.8 cm/s) during resuscitation, each larger than flow towards (41.7+/-14.8 cm/s) and away from brain (-3.0 +/-7.8 cm/s) during baseline.
Conclusion:
Measurement of CABF before and during CPR in swine with a non-imaging ultrasound probe is feasible before CA and informative when achieved during CPR. For example, observations of reverse flow within the carotid artery during CPR merits further study for its prevalence and effect on resuscitation outcomes. Also, tissue motion represents a significant obstacle for CABF measurement during CPR. Additional work will determine the feasibility and utility of non-imaging ultrasound measurements of CABF during resuscitation.
Related Concept Videos
 01:21
Pilot and Numeric Relaying
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...