Related Experiment Video
Updated: Feb 3, 2026


Author Spotlight: Simulating Pediatric Cardiac Surgery Using a Neonatal Piglet Model
Published on: May 26, 2023
Variation in Adjusted Mortality for Medical Admissions to Pediatric Cardiac ICUs
Michael Gaies1,2, Nancy S Ghanayem3, Jeffrey A Alten4
1Department of Pediatrics and Communicable Diseases, C.S. Mott Children's Hospital and University of Michigan Medical School, Ann Arbor, MI.

Insights
This study developed a case-mix adjusted model to assess mortality in pediatric cardiac intensive care units (CICUs) for medical admissions. It identified significant variation in mortality rates across different CICUs, highlighting areas for quality improvement.
Area of Science:
- Pediatric Critical Care Medicine
- Healthcare Quality Improvement
- Biostatistics
Background:
- Pediatric cardiac intensive care units (CICUs) manage complex medical and surgical cardiac conditions.
- Existing quality metrics lack case-mix adjustment for medical admissions in CICUs.
- There is a need for standardized methods to evaluate CICU performance for non-surgical patients.
Purpose of the Study:
- To measure case-mix adjusted mortality rates for medical admissions in pediatric CICUs.
- To assess the variation in these adjusted mortality rates across participating centers in the Pediatric Cardiac Critical Care Consortium (PC4).
- To establish a quality metric for evaluating CICU performance in managing critically ill cardiac patients without surgery.
Main Methods:
- An observational analysis of the Pediatric Cardiac Critical Care Consortium (PC4) clinical registry was conducted.
- A multivariable logistic regression model was developed to adjust for patient case-mix at admission.
- Standardized mortality ratios (SMRs) were calculated for each CICU, with outlier identification based on 95% confidence intervals.
Main Results:
- The study analyzed 11,042 medical admissions across 25 CICUs from August 2014 to May 2017, with an observed mortality rate of 4.3%.
- The final case-mix adjustment model included variables such as age, nutritional status, prior surgery, admission details, high-risk diagnoses, and need for mechanical support.
- The model demonstrated strong predictive accuracy (C-statistic = 0.87). SMRs varied from 0.5 to 1.7, with three CICUs identified as significant outliers (two with lower-than-expected and one with higher-than-expected mortality).
Conclusions:
- This study presents the first case-mix adjusted mortality metric for medical admissions in pediatric CICUs.
- The developed metric reveals significant variation in quality of care across CICUs within the PC4 network.
- This metric will enable CICUs to benchmark performance, identify areas for improvement, and foster collaborative learning to enhance patient outcomes.
Objectives:
Pediatric cardiac ICUs should be adept at treating both critical medical and surgical conditions for patients with cardiac disease. There are no case-mix adjusted quality metrics specific to medical cardiac ICU admissions. We aimed to measure case-mix adjusted cardiac ICU medical mortality rates and assess variation across cardiac ICUs in the Pediatric Cardiac Critical Care Consortium.
Design:
Observational analysis.
Setting:
Pediatric Cardiac Critical Care Consortium clinical registry.
Patients:
All cardiac ICU admissions that did not include cardiac surgery.
Interventions:
None.
Measurements And Main Results:
The primary endpoint was cardiac ICU mortality. Based on multivariable logistic regression accounting for clustering, we created a case-mix adjusted model using variables present at cardiac ICU admission. Bootstrap resampling (1,000 samples) was used for model validation. We calculated a standardized mortality ratio for each cardiac ICU based on observed-to-expected mortality from the fitted model. A cardiac ICU was considered a statistically significant outlier if the 95% CI around the standardized mortality ratio did not cross 1. Of 11,042 consecutive medical admissions from 25 cardiac ICUs (August 2014 to May 2017), the observed mortality rate was 4.3% (n = 479). Final model covariates included age, underweight, prior surgery, time of and reason for cardiac ICU admission, high-risk medical diagnosis or comorbidity, mechanical ventilation or extracorporeal membrane oxygenation at admission, and pupillary reflex. The C-statistic for the validated model was 0.87, and it was well calibrated. Expected mortality ranged from 2.6% to 8.3%, reflecting important case-mix variation. Standardized mortality ratios ranged from 0.5 to 1.7 across cardiac ICUs. Three cardiac ICUs were outliers; two had lower-than-expected (standardized mortality ratio <1) and one had higher-than-expected (standardized mortality ratio >1) mortality.
Conclusions:
We measured case-mix adjusted mortality for cardiac ICU patients with critical medical conditions, and provide the first report of variation in this quality metric within this patient population across Pediatric Cardiac Critical Care Consortium cardiac ICUs. This metric will be used by Pediatric Cardiac Critical Care Consortium cardiac ICUs to assess and improve outcomes by identifying high-performing (low-mortality) centers and engaging in collaborative learning.


Related Concept Videos
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:25
The Anchoring-and-Adjustment Heuristic
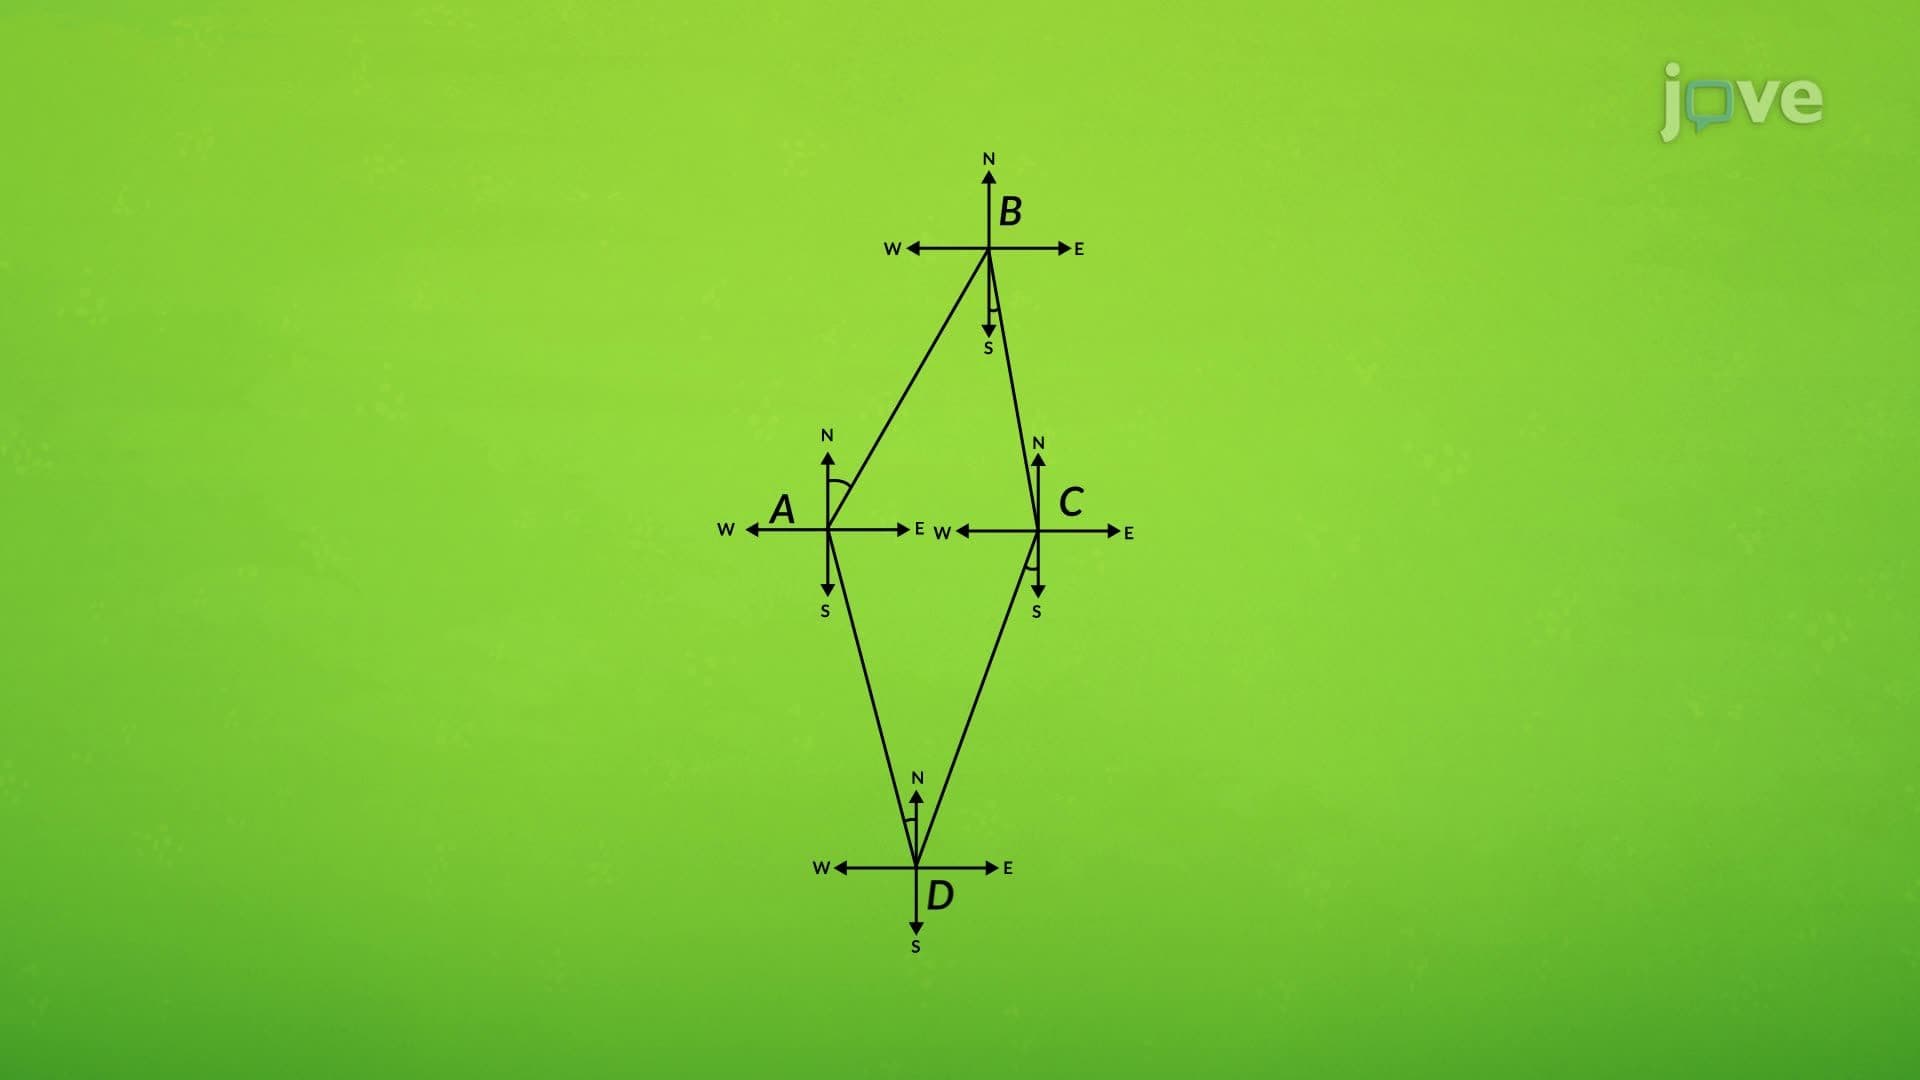 01:12
Adjusting a Traverse
 01:19
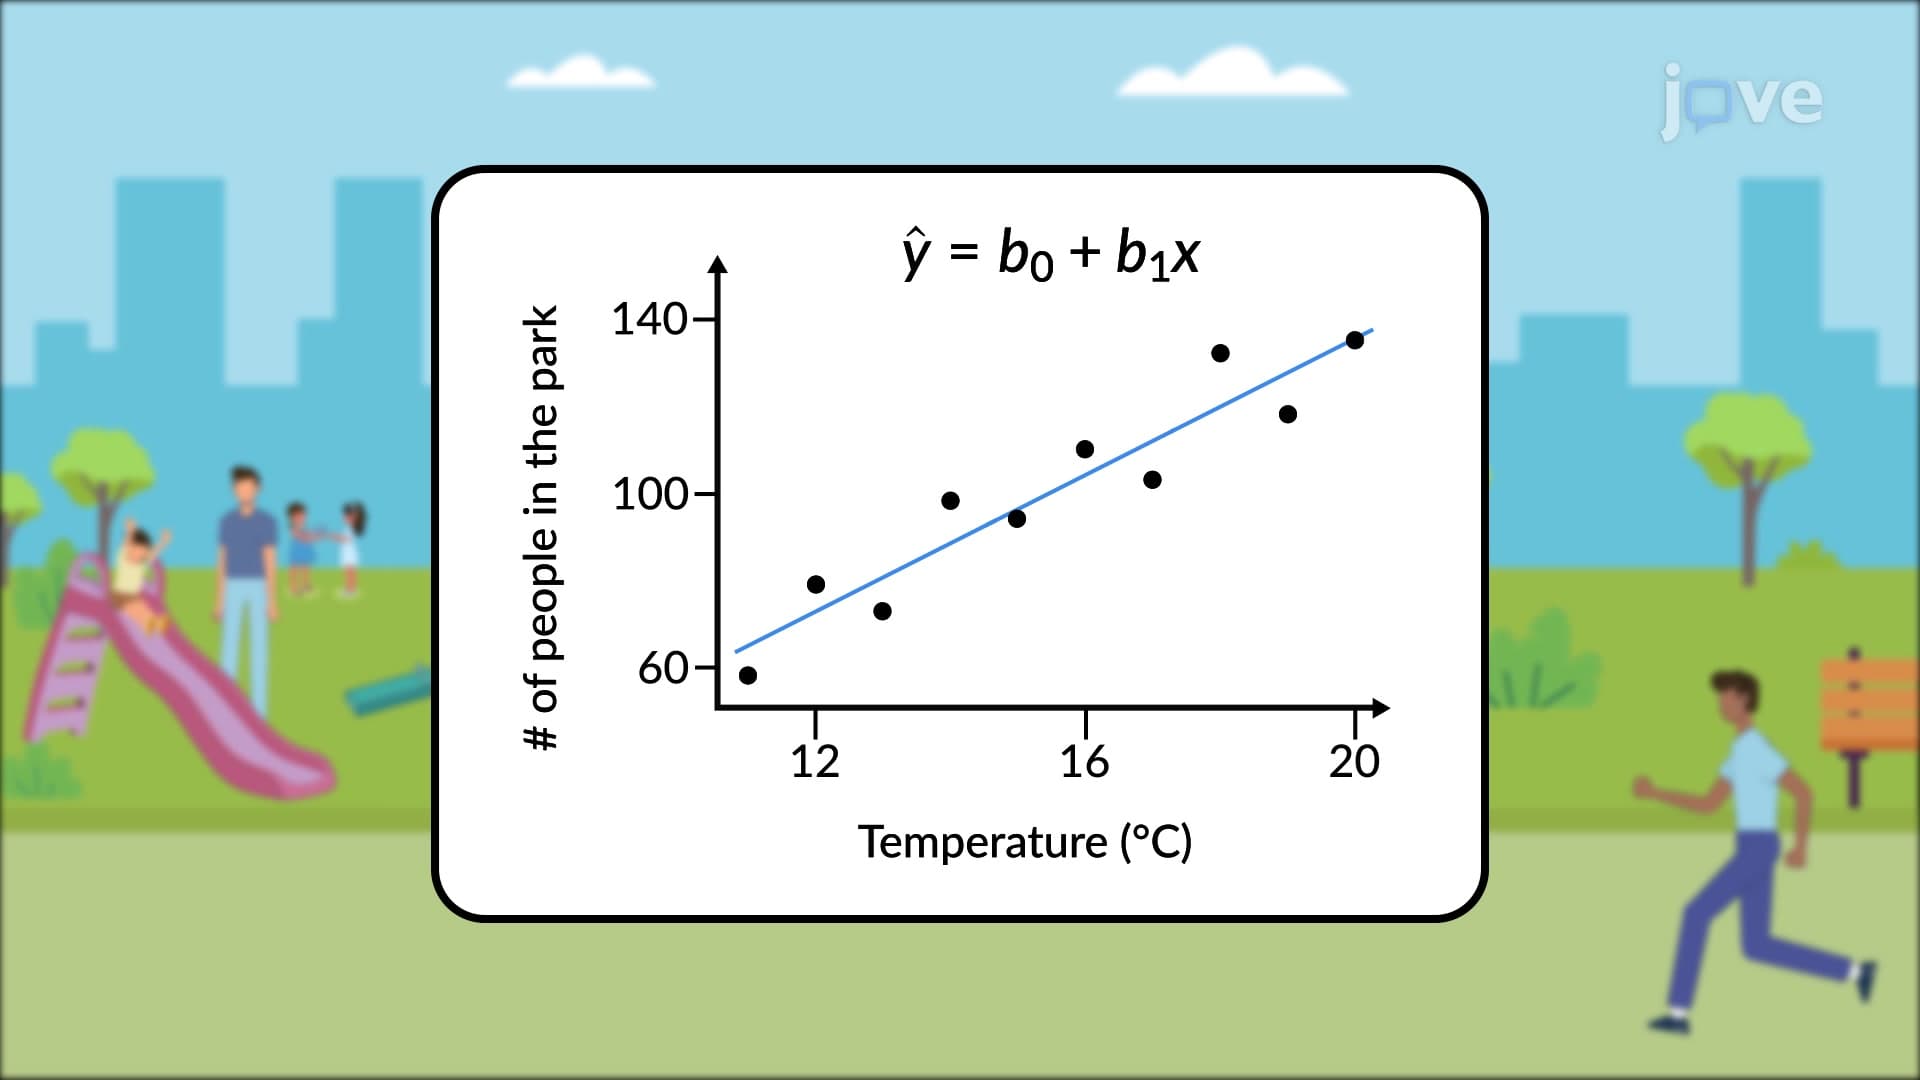
Variation
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:18
Variation of Atmospheric Pressure
Assuming the air temperature is constant at a given altitude and that the ideal gas law of thermodynamics describes the atmosphere to a good approximation, one can find the variation of atmospheric pressure with height.
Let p(y) be the atmospheric pressure at...