Related Experiment Video
Updated: Feb 3, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Augmented renal clearance in pediatric intensive care: are we undertreating our sickest patients?
Evelyn Dhont1,2, Tatjana Van Der Heggen3, Annick De Jaeger4
1Department of Pediatric Intensive Care, Ghent University Hospital, Ghent, Belgium. evelyn.dhont@ugent.be.

Insights
Augmented renal clearance (ARC) in critically ill children leads to faster drug elimination and potential treatment failure. Early detection and adjusted dosing are crucial for effective pediatric intensive care.
Area of Science:
- Critical care medicine
- Pediatric nephrology
- Pharmacokinetics
Background:
- Critically ill patients often exhibit augmented renal clearance (ARC), characterized by increased renal perfusion and hyperfiltration.
- ARC can lead to accelerated drug elimination, potentially causing subtherapeutic drug concentrations and treatment failure.
- This phenomenon is increasingly recognized in critically ill children, mirroring observations in adult intensive care units.
Purpose of the Study:
- To review current knowledge on ARC in critically ill children.
- To explore the pathophysiological mechanisms underlying ARC in this population.
- To evaluate methods for screening ARC and its impact on drug therapy and outcomes.
Main Methods:
- Literature review focusing on augmented renal clearance in pediatric intensive care.
- Analysis of existing data on renal function assessment in critically ill children.
- Examination of pharmacokinetic studies related to drug dosing in pediatric critical care.
Main Results:
- Standard glomerular filtration rate (GFR) equations are unreliable for critically ill children with fluctuating renal function.
- Urinary creatinine clearance is currently the most reliable method for detecting ARC in this population.
- ARC is associated with subtherapeutic drug levels, particularly antimicrobials, leading to therapeutic failure.
Conclusions:
- ARC is a significant factor affecting drug efficacy in critically ill children.
- Accurate assessment of renal function is essential for appropriate drug dosing.
- Development of real-time GFR monitoring tools is needed to optimize treatment in pediatric critical care.
Abstract:
Many critically ill patients display a supraphysiological renal function with enhanced renal perfusion and glomerular hyperfiltration. This phenomenon described as augmented renal clearance (ARC) may result in enhanced drug elimination through renal excretion mechanisms. Augmented renal clearance seems to be triggered by systemic inflammation and therapeutic interventions in intensive care. There is growing evidence that ARC is not restricted to the adult intensive care population, but is also prevalent in critically ill children. Augmented renal clearance is often overlooked due to the lack of reliable methods to assess renal function in critically ill children. Standard equations to calculate glomerular filtration rate (GFR) are developed for patients who have a steady-state creatinine production and a stable renal function. Those formulas are not reliable in critically ill patients with acutely changing GFR and tend to underestimate true GFR in patients with ARC. Tools for real-time, continuous, and non-invasive measurement of fluctuating GFR are most needed to identify changes in kidney function during critical illness and therapeutic interventions. Such devices are currently being validated and hold a strong potential to become the standard of practice. In the meantime, urinary creatinine clearance is considered the most reliable method to detect ARC in critically ill patients. Augmented renal clearance is clearly associated with subtherapeutic antimicrobial concentrations and subsequent therapeutic failure. This warrants the need for adjusted dosing regimens to optimize pharmacokinetic and pharmacodynamic target attainment. This review aims to summarize current knowledge on ARC in critically ill children, to give insight into its possible pathophysiological mechanism, to evaluate screening methods for ARC in the pediatric intensive care population, and to illustrate the effect of ARC on drug exposure, therapeutic efficacy, and clinical outcome.
More Related Videos
 10:38
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
 09:26
Combining Augmented Reality and 3D Printing to Display Patient Models on a Smartphone
Published on: January 2, 2020
Related Concept Videos
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:06
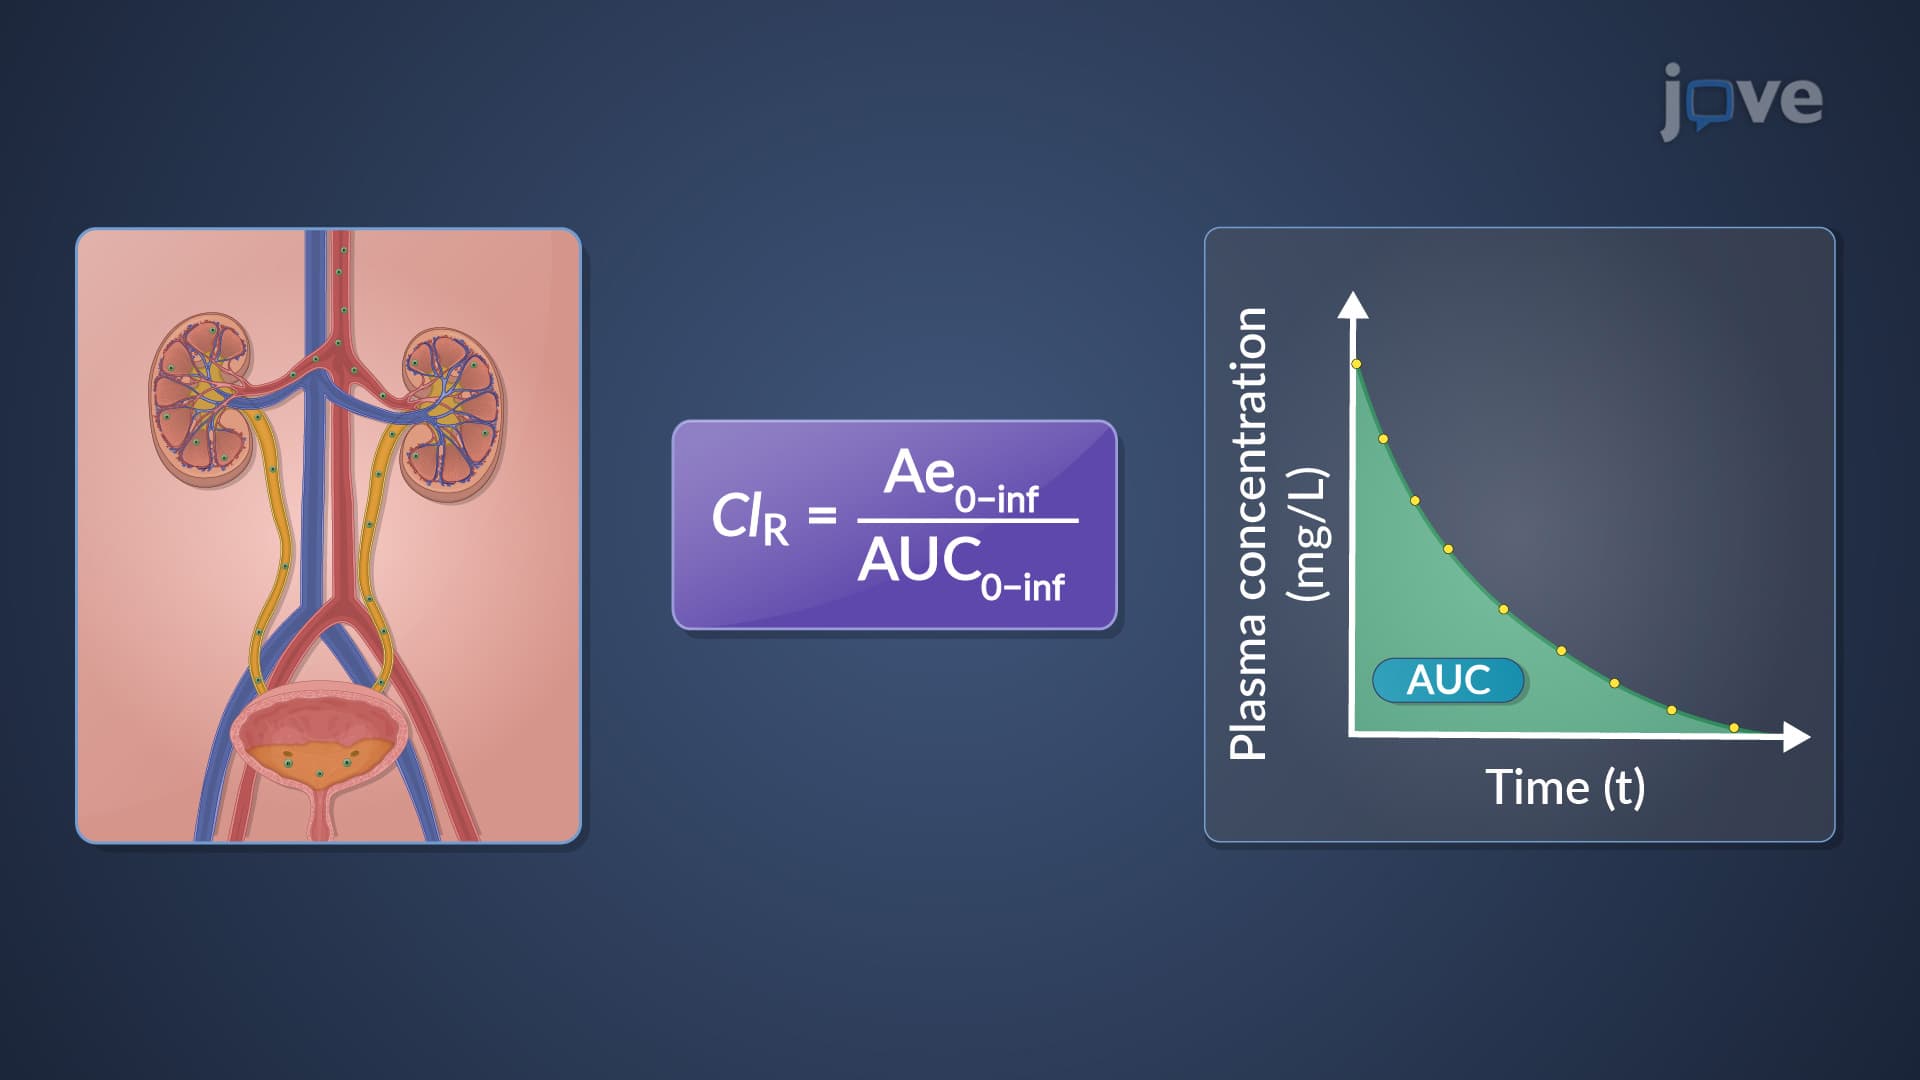
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:08
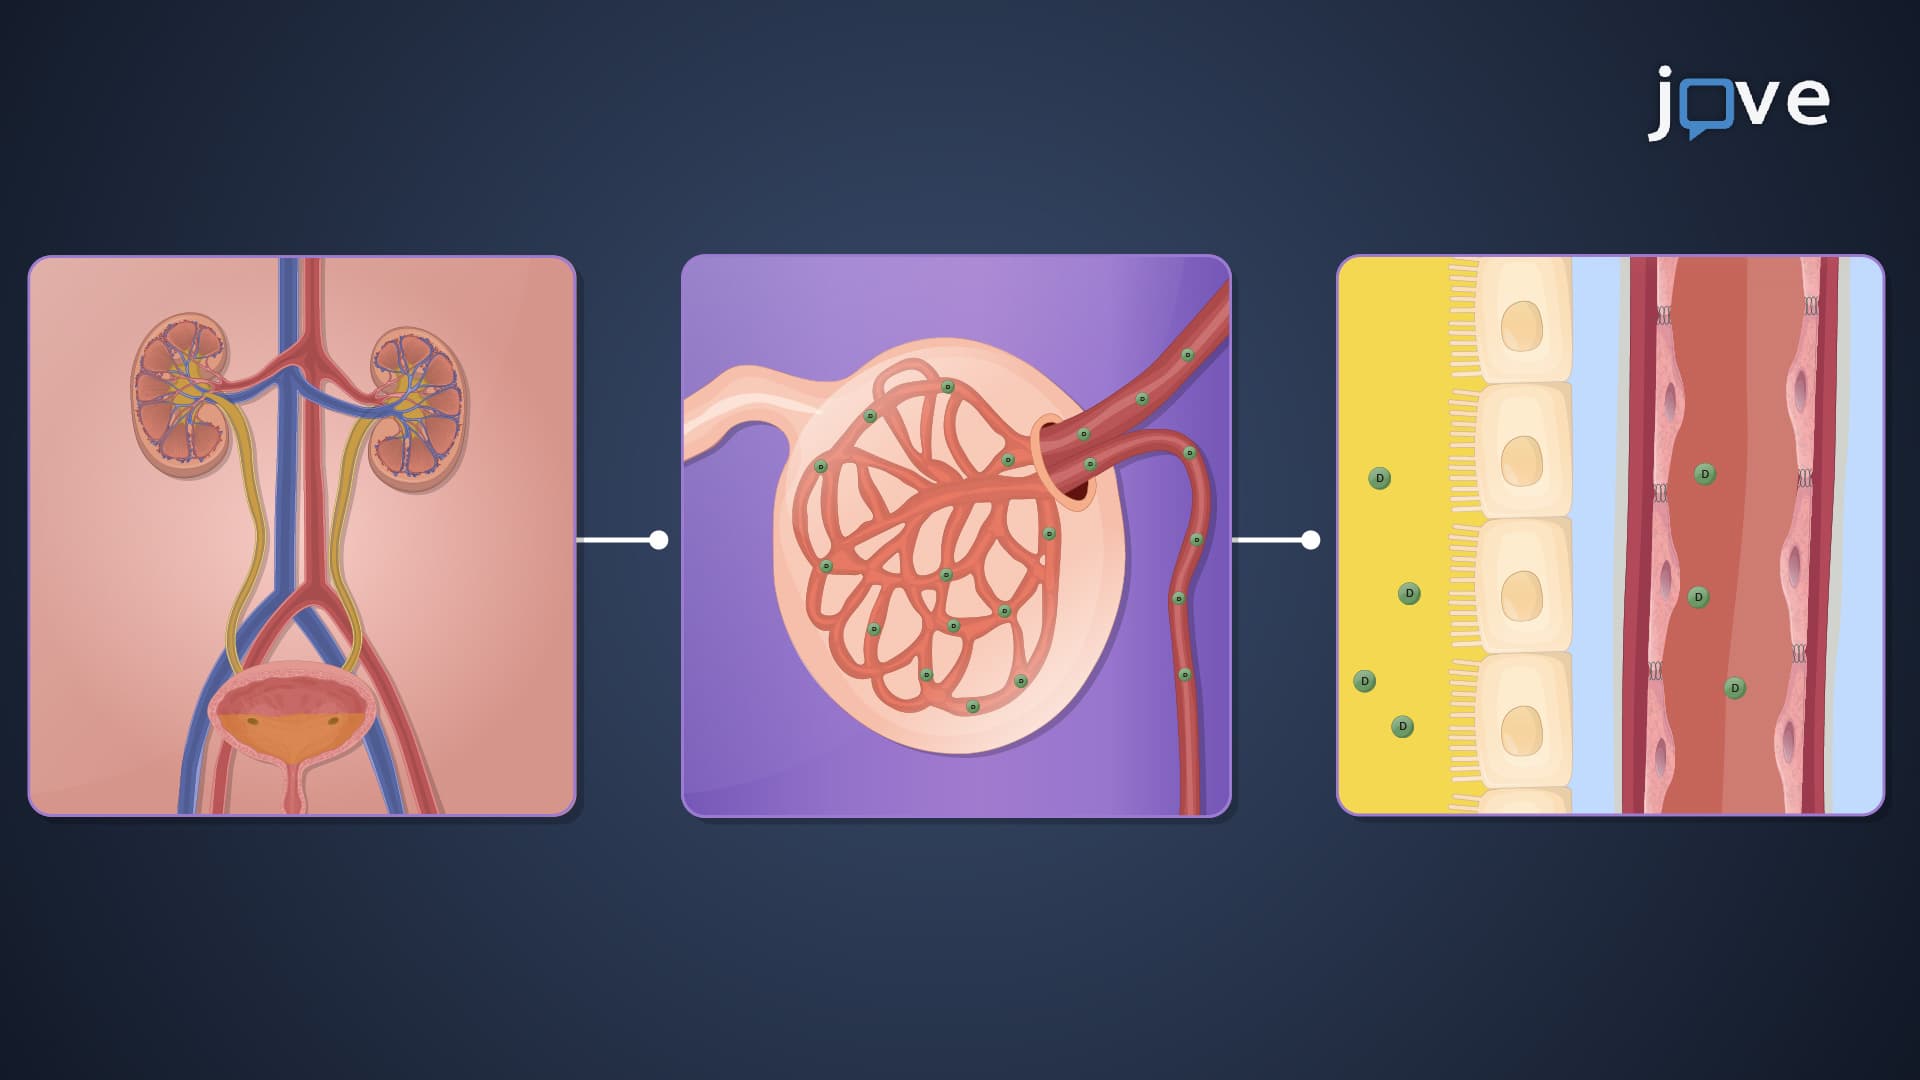
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:13
Patient-centered Care
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion