Related Experiment Video
Updated: Feb 3, 2026


Manufacturing Chimeric Antigen Receptor CAR T Cells for Adoptive Immunotherapy
Published on: December 17, 2019
Pitfalls of immunotherapy: lessons from a patient with CTLA-4 haploinsufficiency
Leisa Rebecca Watson1, Charlotte A Slade2,3,4, Samar Ojaimi1,5
11Faculty of Medicine, Nursing and Health Sciences, Monash University, Clayton, VIC Australia.

Background:
Daclizumab is a humanized monoclonal antibody that blocks CD25, the high affinity alpha subunit of the interleukin-2 receptor. Daclizumab therapy targets T regulatory cell and activated effector T cell proliferation to suppress autoimmune disease activity, in inflammatory conditions like relapsing and remitting multiple sclerosis. Here, we present the first report of agranulocytosis with daclizumab therapy in a patient with relapsing and remitting multiple sclerosis.
Case Presentation:
Our patient was a 24-year-old Australian female with a clinical history of atopy, lymphocytic enteritis complicated by B12 deficiency, relapsing and remitting multiple sclerosis, recurrent lower respiratory tract infections, vulval/cervical intraepithelial neoplasia and melanoma. She was commenced on daclizumab therapy after failing several lines of treatment for relapsing and remitting multiple sclerosis. During a hospital admission for lymphocytic enteritis, she was incidentally diagnosed with combined immunodeficiency with hypogammaglobulinaemia and declined proposed regular intravenous immunoglobulin infusions. Following six months of daclizumab therapy, our patient presented to hospital with febrile neutropenia. No clear infective cause was found, despite numerous investigations. However, bone marrow biopsy revealed agranulocytosis with an apparent maturation block at the myeloblasts stage. Neustrophil recovery occurred following cessation of daclizumab and the initiation of T cell immunosuppressive agents including systemic corticosteroids and methotrexate. The patient was further investigated for combined immunodeficiency and whole exome sequencing revealed a novel heterozygous missense variant in cytotoxic T lymphocyte antigen 4 (CTLA4), leading to a diagnosis of CTLA-4 haploinsufficiency with autoimmune infiltration (CHAI).
Conclusion:
This case demonstrates that autoimmune disease may be the presenting feature of primary immunodeficiency and should be appropriately investigated prior to the commencement of immunotherapy. Genetic clarification of underlying primary immunodeficiency may provide critical clinical information that alters the safety of the proposed treatment strategy.

Related Concept Videos
 01:27
Tumor Immunotherapy
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:20
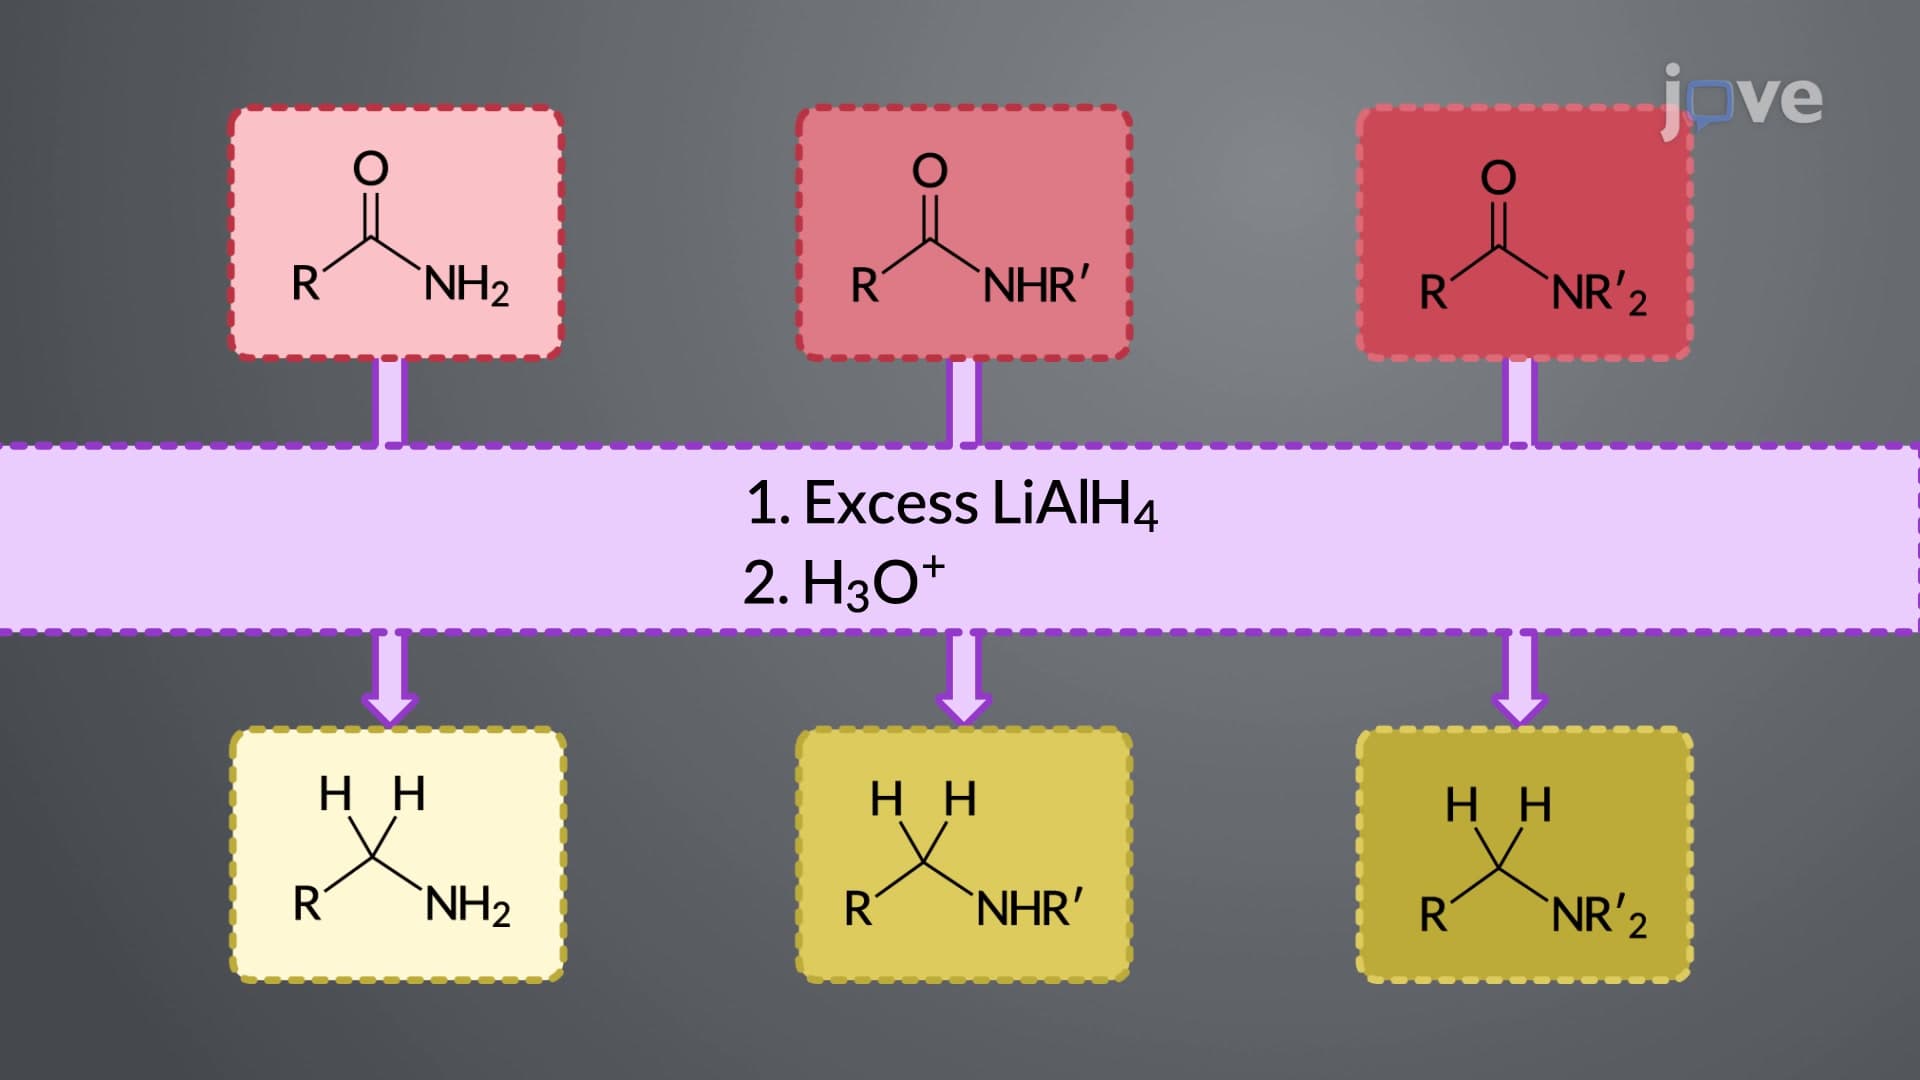
Amides to Amines: LiAlH4 Reduction
Amide reduction requires two equivalents of the reducing agent, acting as a source of hydride ions. As shown in the figure, the reaction is initiated with a nucleophilic attack by the hydride ion at the carbonyl carbon to form a tetrahedral intermediate.
 01:19
Piaget's Stage 4 of Cognitive Development
Abstract Reasoning and Hypothetical-Deductive Thinking
Unlike the concrete operational...
 00:55
Nitriles to Amines: LiAlH4 Reduction
As shown below, the mechanism involves three steps. Firstly, the hydride ion acting as a nucleophile attacks the nitrile carbon to form an anion. In the second step, a second equivalent of the hydride ion attacks the anion to...
 01:19
Acid Halides to Alcohols: LiAlH4 Reduction
The mechanism proceeds in three steps. First, the nucleophilic hydride ion attacks the carbonyl carbon of the acid halide to form a tetrahedral intermediate. Next, the carbonyl group is re-formed, and the halide ion departs as a leaving group, generating an aldehyde. A second nucleophilic attack by the hydride yields an alkoxide ion, which, upon protonation, gives a primary alcohol as...