Related Experiment Video
Updated: Feb 2, 2026

Use of Interferon-γ Enzyme-linked Immunospot Assay to Characterize Novel T-cell Epitopes of Human Papillomavirus
Published on: March 8, 2012
Performance of Tuberculin Skin Tests and Interferon-γ Release Assays in Children Younger Than 5 Years
Eneritz Velasco-Arnaiz1,2, Antoni Soriano-Arandes3, Irene Latorre4
1From the Malalties Infeccioses i Resposta Inflamatòria Sistèmica en Pediatria, Unitat d´Infeccions, Servei de Pediatria, Institut de Recerca Pediàtrica Hospital Sant Joan de Déu, Barcelona, Spain.

Insights
Limited data exist for optimal tuberculosis (TB) diagnosis in young children. A dual testing strategy with tuberculin skin tests (TST) and QuantiFERON-TB Gold (QFT-GIT) may not be needed for BCG-unvaccinated children with TB contact.
Area of Science:
- Pediatric infectious diseases
- Diagnostic immunology
- Public health
Background:
- Optimal diagnostic approaches for tuberculosis (TB) in infants and preschool children are not well-established.
- Limited data exist regarding the comparative performance of different TB diagnostic tests in this age group.
Purpose of the Study:
- To compare the effectiveness of tuberculin skin tests (TST) and QuantiFERON-TB Gold In-Tube (QFT-GIT) assays in diagnosing TB in children under 5 years old.
- To evaluate the agreement and discordance between TST and QFT-GIT in various pediatric populations at risk for TB.
Main Methods:
- A prospective observational study involving 383 children under 5 years old was conducted at two tertiary TB units.
- Children underwent both TST and QFT-GIT testing.
- Follow-up was performed to assess the development of active TB or latent TB infection.
Main Results:
- Overall agreement between TST and QFT-GIT was moderate (κ = 0.551), but high in BCG-unvaccinated children (κ = 0.816) and after TB contact (κ = 0.801).
- Discordant results (TST+/QFT-GIT-) were observed in 16.8% of cases, primarily in BCG-vaccinated and new-entrant children.
- Both TST (100% sensitivity) and QFT-GIT (93.7% sensitivity) showed high sensitivity for active TB detection in children.
Conclusions:
- A parallel dual testing strategy with TST and QFT-GIT may be unnecessary for young, BCG-unvaccinated children with recent TB contact.
- The clinical significance of TST+/QFT-GIT- discordance requires further investigation.
- QFT-GIT assays do not demonstrate superior performance over TST in diagnosing active TB in children.
Background:
Available data to assess the optimal diagnostic approach in infants and preschool children at risk of tuberculosis (TB) are limited.
Methods:
We conducted a prospective observational study in children younger than 5 years undergoing assessment with both tuberculin skin tests (TST) and QuantiFERON-TB Gold In-Tube (QFT-GIT) assays at 2 tertiary TB units in Barcelona, Spain.
Results:
A total of 383 children were included. One of 304 participants considered uninfected developed active TB during follow-up {median [interquartile range (IQR)]: 47 [30; 48] months}, compared with none of 40 participants with latent TB infection [follow-up since completion of anti-TB treatment: 42 (32; 45) months]. Overall test agreement between TST and QFT-GIT was moderate (κ = 0.551), but very good in children screened after TB contact (κ = 0.801) and in Bacillus Calmette-Guérin (BCG)-unvaccinated children (κ = 0.816). Discordant results (16.8%, all TST+/QFT-GIT-) were mainly observed in new-entrant screening and in BCG-vaccinated children. Children with indeterminate QFT-GIT results were on average younger than those with determinate results (median age: 12 vs. 30 months; P < 0.001). The sensitivity of TSTs and QFT-GIT assays in children with confirmed active TB was 100% (95% confidence interval: 79.4%-100%) and 93.7% (95% confidence interval: 69.8%-99.8%), respectively. In patients with latent TB infection or active TB, there was no correlation between age and antigen-stimulated interferon-γ responses (r = -0.044; P = 0.714).
Conclusions:
In young BCG-unvaccinated children with recent TB contact, a dual testing strategy using TST and QFT-GIT in parallel may not be necessary. However, TST+/QFT-GIT- discordance is common, and it remains uncertain if this constellation indicates TB infection or not. In active TB, QFT-GIT assays do not perform better than TSTs.
More Related Videos
 10:10
Experimental Infection with Listeria monocytogenes as a Model for Studying Host Interferon-γ Responses
Published on: November 16, 2016
 15:57
Application of Long-term cultured Interferon-γ Enzyme-linked Immunospot Assay for Assessing Effector and Memory T Cell Responses in Cattle
Published on: July 11, 2015
Related Concept Videos
 01:10
In Vitro Drug Release Testing: Overview, Development and Validation
 01:04
5-Number Summary
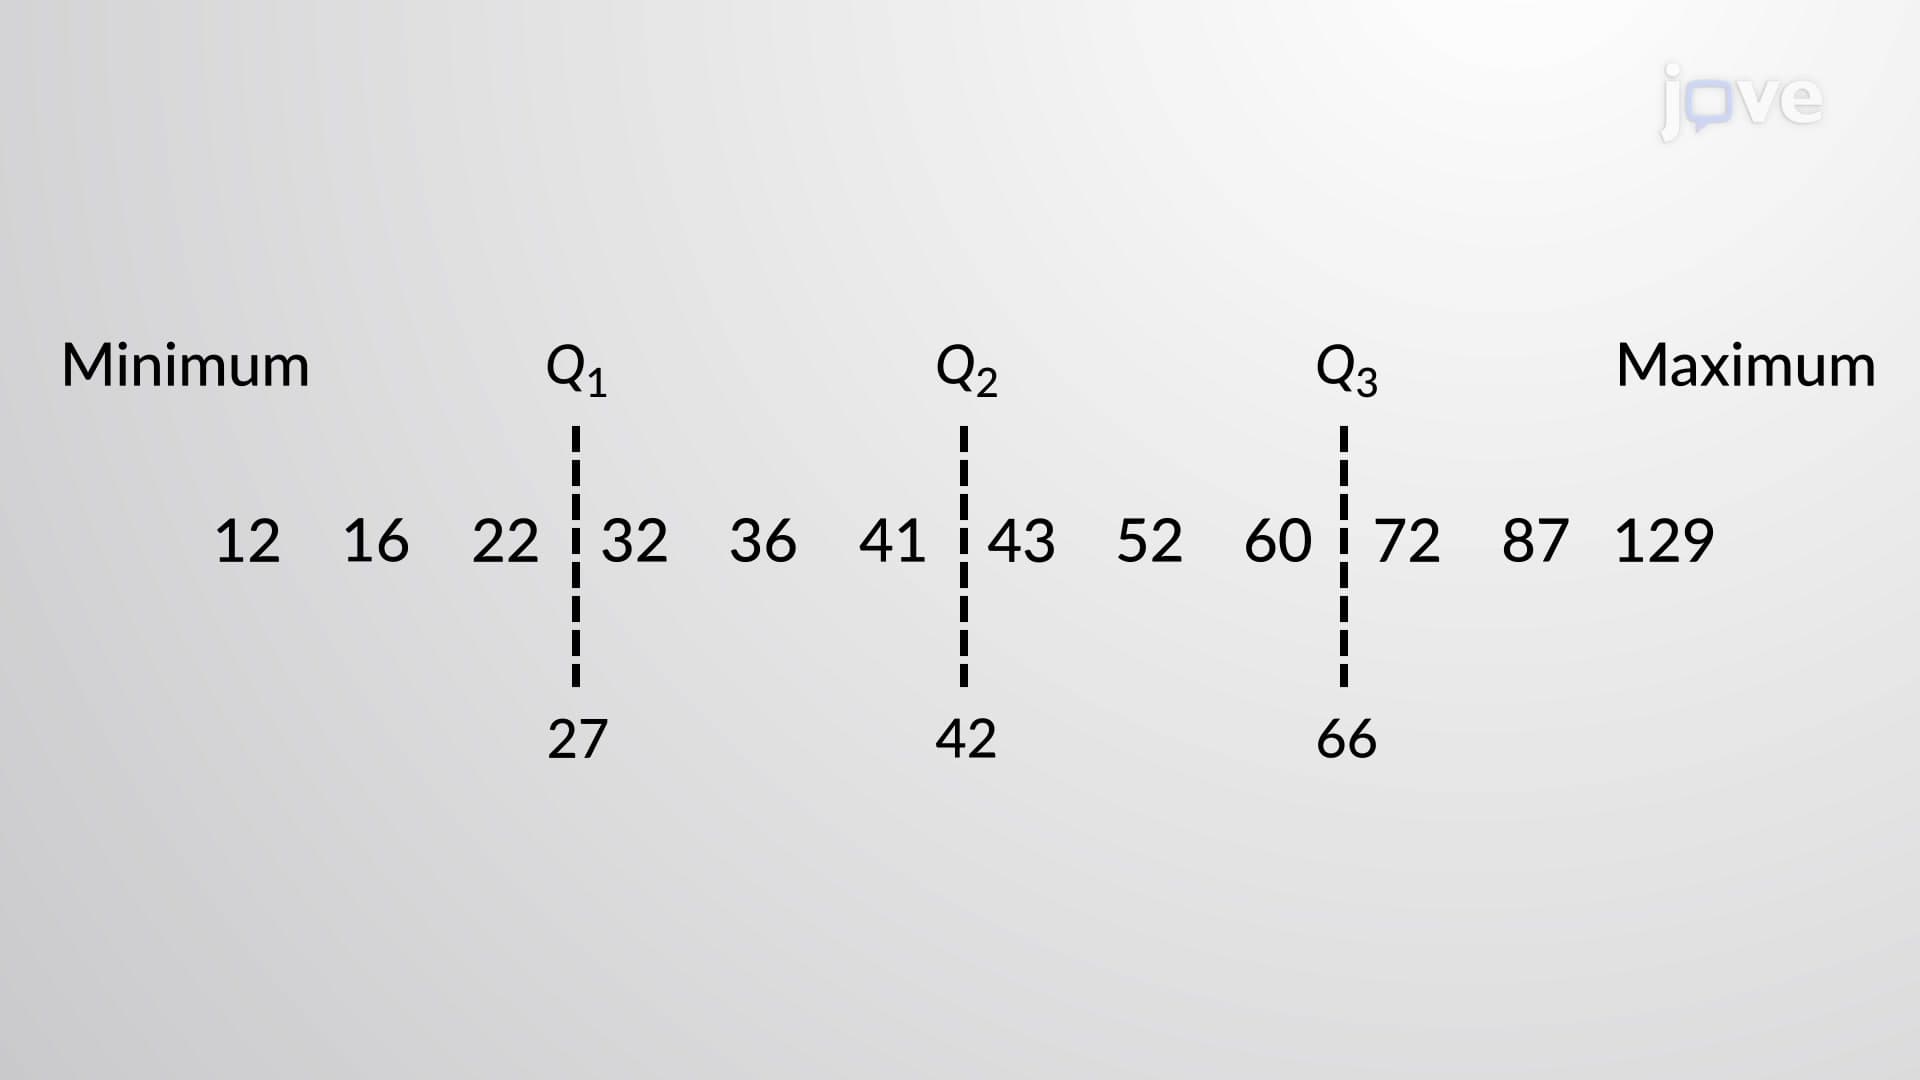
In a box plot, the minimum and maximum data values represent the lower and upper whiskers in the graph, and the median is designated as the center of the box in the chart. The first quartile and third...
 01:28
Energy-releasing Steps of Glycolysis
The first energy-releasing step—the 6th step of glycolysis...
 01:29
Drug Dosing: Infants and Children
 01:30
Skin Cancer
Basal Cell Carcinoma (BCC): BCC is the most common type of skin cancer, accounting for about 80% of cases. It typically develops in...
 01:31
ATP Energy Storage and Release
One example of energy coupling using ATP involves a...