Related Experiment Video
Updated: Feb 2, 2026


Activity-based Training on a Treadmill with Spinal Cord Injured Wistar Rats
Published on: January 16, 2019
Pain assessment in hospitalized spinal cord injured patients - a controlled cross-sectional study
Amalie Rosendahl1, Søren Krogh2, Helge Kasch3,4
1Spinal Cord Injury Center of Western Denmark, Regional Hospital Viborg, Viborg, Denmark.

Abstract:
Background and aims Following spinal cord injury (SCI), a majority of individuals may develop neuropathic pain, which further reduces quality of life. Pain is difficult to treat by medication; in fact, medication overuse may aggravate neuropathic pain in SCI by causing central sensitization (CS): a mechanism of hyper-reactivity of the dorsal horn neurons in the spinal cord with amplified cerebral pain response. The purpose of this study was to examine the presence of neuropathic pain and CS above the spinal lesion in SCI, and to investigate whether injury characteristics or medication influenced pain response. Methods Twenty-four SCI patients with various injury characteristics (eight subacute, traumatic injuries, eight chronic, traumatic injuries, eight non-traumatic injuries) and 12 able-bodied controls underwent sensory testing:pressure algometry, Von Frey filaments (sensitivity), and repetitive pinprick stimulation (pain windup). SCI participants also fulfilled a modified version of the McGill Pain Questionnaire. Data were analyzed regarding (i) SCI patients compared with controlgroup and (ii) SCI subgroup comparison (grouped by a) injury characteristics and (b) intake of analgesics, where low-medicated subgroup were prescribed only non-opioids and high-medicated potent opioids). Results Neuropathic pain was present in 21 of 24 SCI patients. Chronic and non-traumatic SCI patients reported considerably higher present pain intensity than sub-acute traumatic SCI patients on a five-point scale (3.13±0.99, 1.75±1.75 and 0.13±0.35, respectively, p<0.005). Reduced pressure pain detection thresholds (PPDT) were found in SCI patients at several supra-lesional anatomical points compared to controls. Contrarily, tactile detection thresholds were higher in SCI. SCI subgroup analyses showed that i) the low-medicated SCI subgroup displayed significantly lower PPDT compared to the high-medicated subgroup, ii) pain-windup was present in all subgroups although the sub-acute and non-traumatic subgroups displayed lesser pain windup than controls, and the chronic SCI subgroup mainly displayed higher pain windup. Conclusions The reduced PPDT found above lesion suggests the presence of CS in SCI. However, findings regarding SCI subgroup comparison did not support our hypothesis that more medication leads to increased CS. Implications The development of CS may complicate diagnosis and pain treatment following SCI. Prospective studies of SCI with a healthy control group are needed.
More Related Videos
 08:00
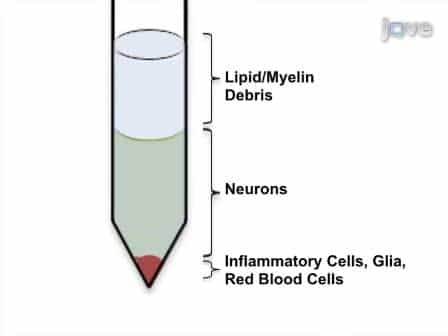
Quantitative Assessment of Immune Cells in the Injured Spinal Cord Tissue by Flow Cytometry: a Novel Use for a Cell Purification Method
Published on: April 9, 2011
 04:42
Treating Low Back Pain in Failed Back Surgery Patients with Multicolumn-lead Spinal Cord Stimulation
Published on: June 26, 2018
Related Concept Videos
 01:16
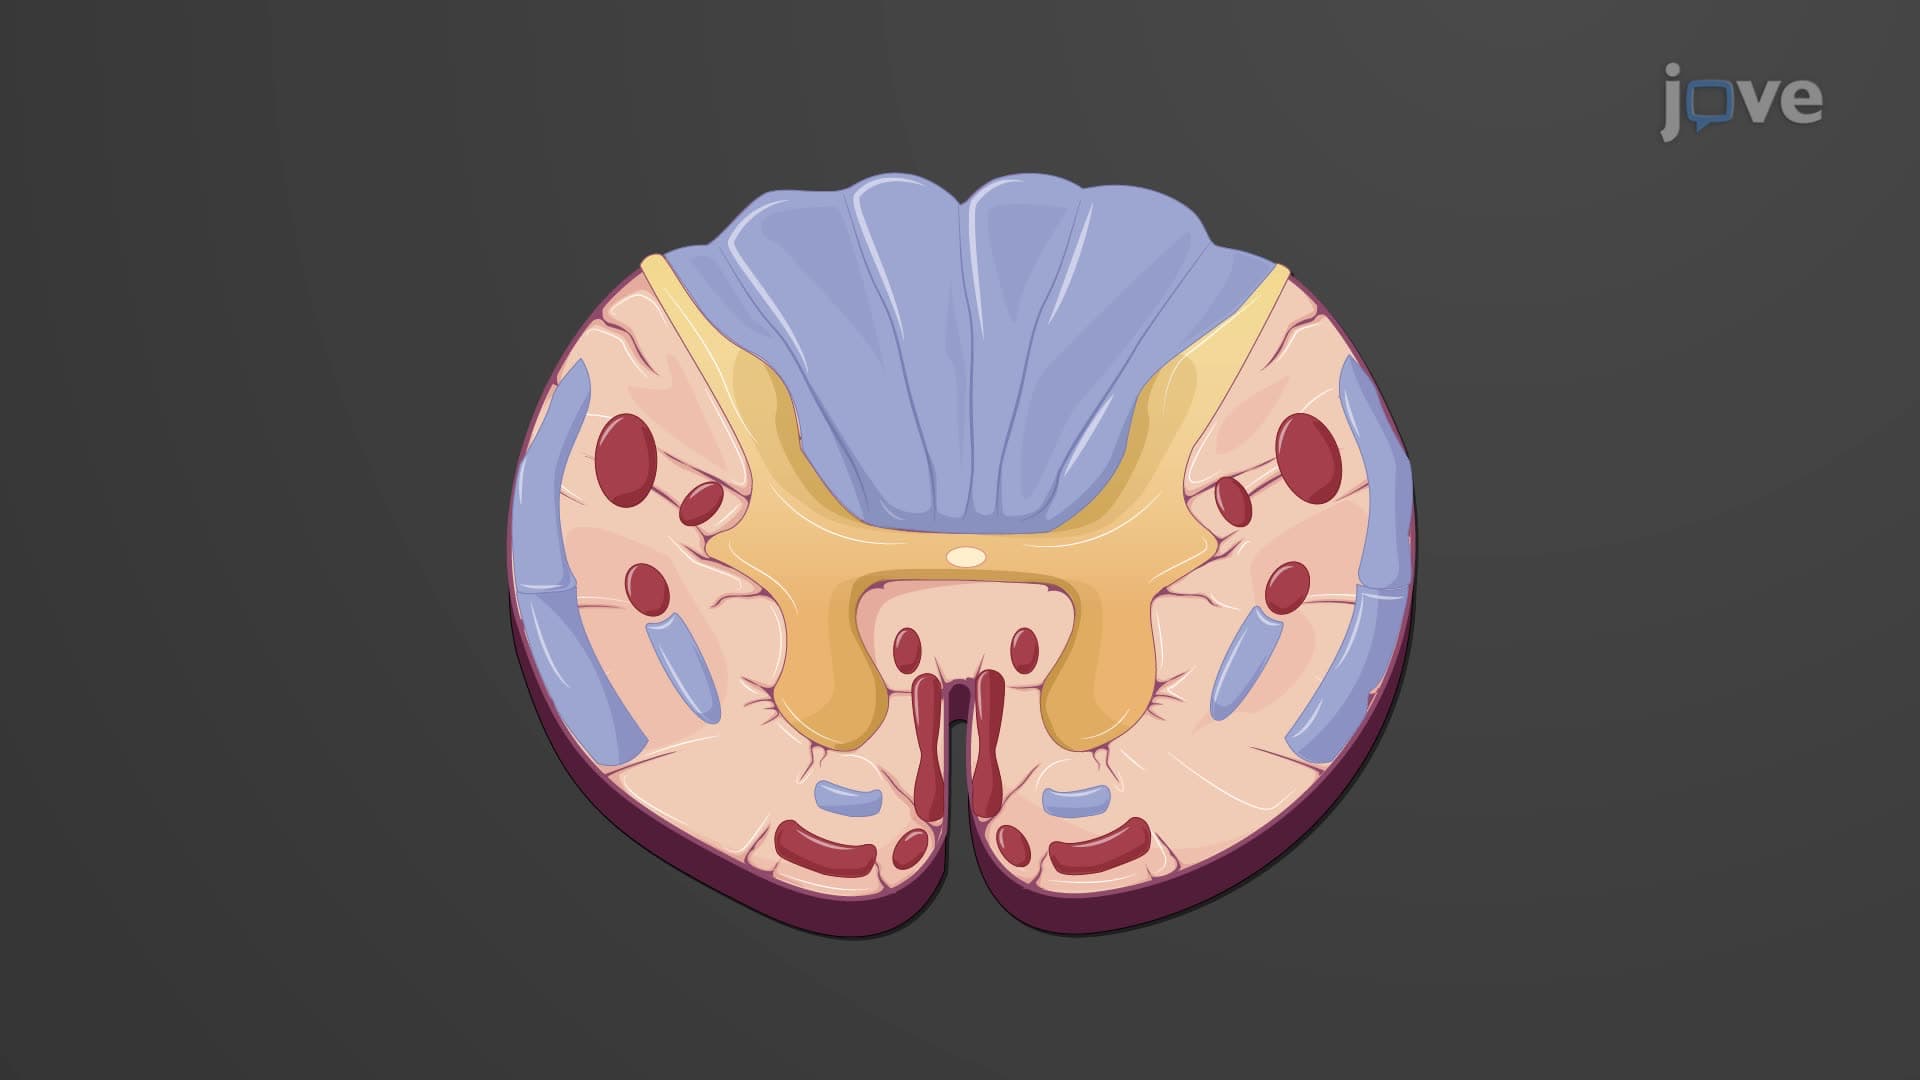
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:50
Cross-Sectional Research
 01:26
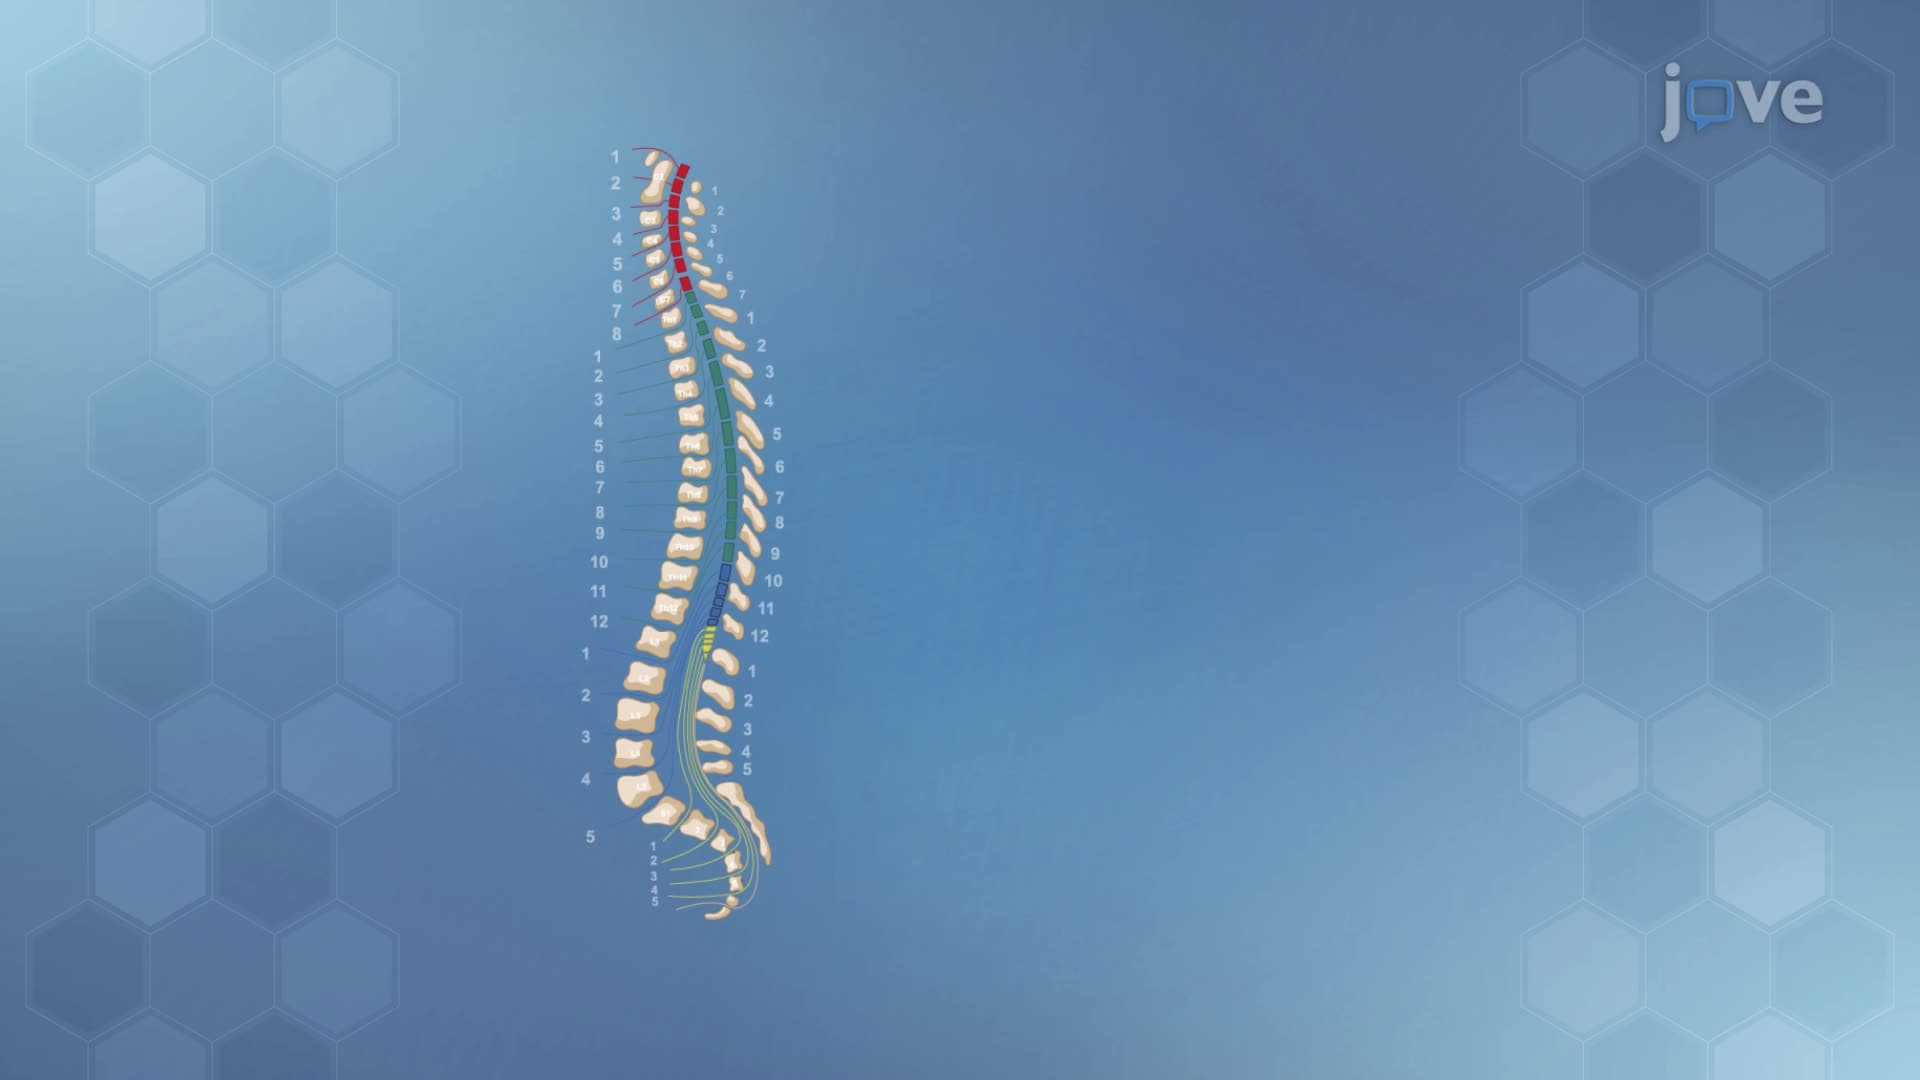
Spinal Cord
 01:54
The Spinal Cord
 00:59
Hospitals-II
Nurses that work in...
 01:10
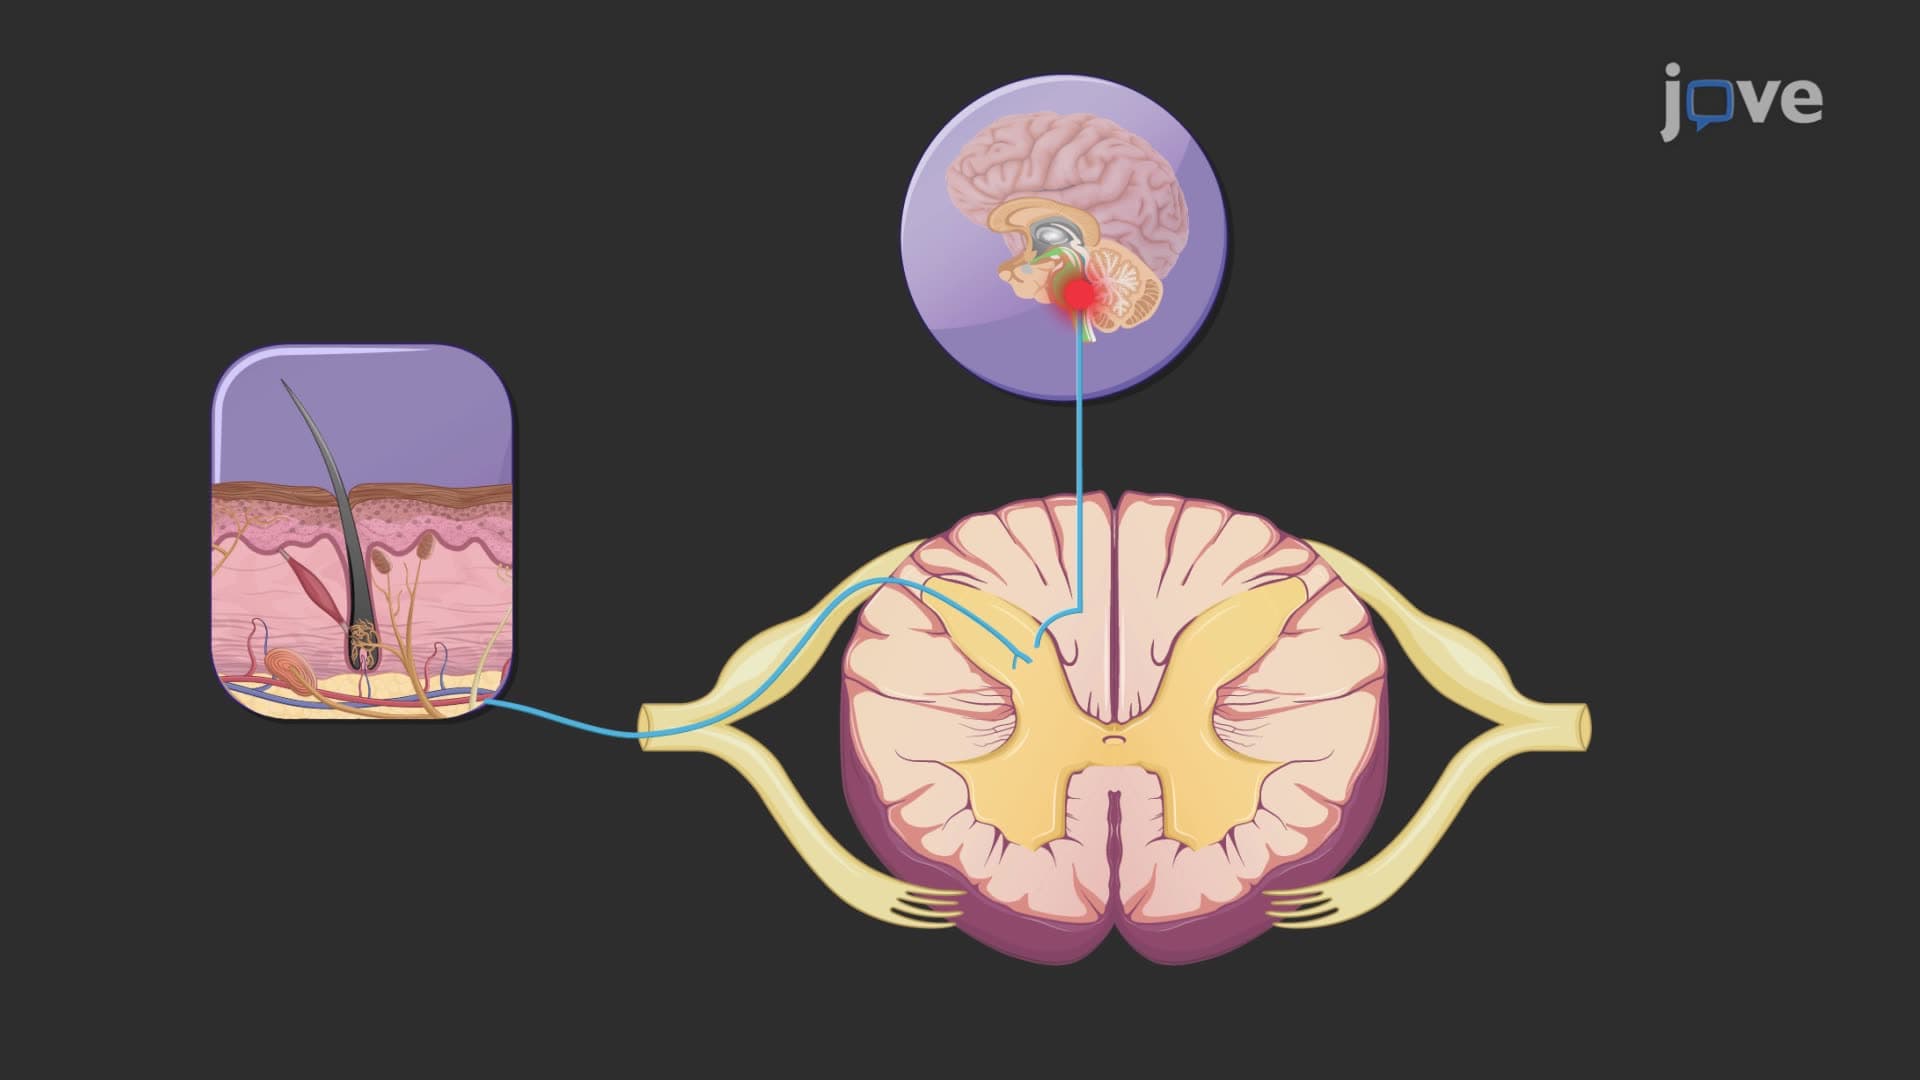
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...