Related Experiment Video
Updated: Jul 30, 2026

Corneal Donor Tissue Preparation for Descemet's Membrane Endothelial Keratoplasty
Published on: September 17, 2014
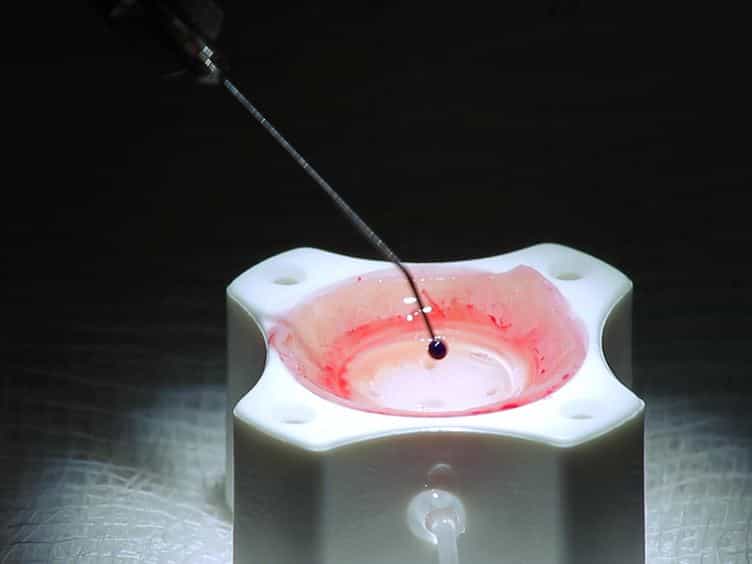
"Ghost DMEK" Technique: Circular Peripheral Staining of Descemet's Membrane Endothelial Keratoplasty Grafts
Eitan Livny1,2, Irit Bahar1,2, Yoav Nahum1,2
1Department of Ophthalmology, Rabin Medical Center, Petach Tikva, Israel.

Purpose:
To describe the ghost Descemet's membrane endothelial keratoplasty (DMEK) technique that allows for real-time evaluation of DMEK graft orientation, location, and folding status within the anterior chamber, by simple observation at the surgical microscope.
Methods:
This is a retrospective case series done in a university hospital. The study included 10 patients who underwent ghost DMEK surgery because of corneal endothelial insufficiency for Fuchs' endothelial dystrophy (N = 5), pseudophakic bullous keratopathy (N = 2), and failed previous posterior lamellar keratoplasty (N = 3). Cases were reviewed for feasibility of graft preparation, intra- and postoperative complications, postoperative clearing of the cornea, corrected distance visual acuity, and endothelial cell loss.
Results:
All graft preparations were uneventful. The circular staining was readily apparent and did not fade away during surgery. Graft orientation and folding status were determined using only direct observation through the operating microscope. Complications included one intraoperative hyphema, one graft detachment requiring rebubbling, and one pupillary block on the first postoperative day, which was resolved surgically. At last visit, 8 of 10 eyes had visual acuity of 6/12 or better and 7 of 10 eyes had visual acuity of 6/8.5 or better. Mean cell loss rates 1 to 3 months postoperatively were 48% ± 17% (range, 22%-71%). All corneas were clear by the first to second postoperative month. Mean follow-up time was 3 months (range, 1-8 months).
Conclusions:
Peripheral staining of DMEK grafts (ghost DMEK) is a simple and effective method for graft visualization in the anterior chamber, obviating the need for trypan blue staining and other techniques and devices currently used for the identification of graft orientation and folding status, thus simplifying and shortening surgery.