Related Experiment Video
Updated: Feb 2, 2026

Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
PTH, FGF23, and Intensive Blood Pressure Lowering in Chronic Kidney Disease Participants in SPRINT
Charles Ginsberg1,2, Timothy E Craven3, Michel B Chonchol4
1Nephrology Section, Veterans Affairs San Diego Healthcare System, San Diego, California.

Insights
Intensive blood pressure control in chronic kidney disease (CKD) patients benefits cardiovascular health, but high parathyroid hormone (PTH) levels may reduce this protection. FGF23 did not affect outcomes.
Area of Science:
- Nephrology
- Cardiology
- Endocrinology
Background:
- Chronic kidney disease (CKD) is linked to elevated parathyroid hormone (PTH) and fibroblast growth factor-23 (FGF23).
- These factors are associated with increased cardiovascular disease (CVD) risk.
- The SPRINT trial showed intensive blood pressure (BP) lowering reduced CVD but accelerated eGFR decline.
Purpose of the Study:
- To investigate if serum PTH or FGF23 concentrations modify the effects of intensive BP control on cardiovascular events, heart failure, and mortality in SPRINT participants with CKD.
- To assess the independent association of PTH and FGF23 with adverse outcomes in this population.
Main Methods:
- Analysis of 2486 SPRINT participants with estimated glomerular filtration rate (eGFR) <60 ml/min per 1.73 m².
- Measurement of intact PTH and intact FGF23 levels at baseline.
- Use of Cox models to evaluate associations and interactions between PTH, FGF23, and intensive BP control on clinical outcomes.
Main Results:
- Higher PTH concentrations were associated with increased risk of cardiovascular events (HR 1.29) and heart failure (HR 1.32).
- Significant interactions between PTH and BP treatment arm were observed for cardiovascular events (P=0.01) and heart failure (P=0.004).
- Individuals with high PTH showed attenuated benefits from intensive BP control for cardiovascular events compared to those with low PTH. FGF23 showed no significant associations or modifications.
Conclusions:
- In SPRINT participants with CKD, elevated serum PTH levels diminish the cardiovascular protective benefits of intensive BP lowering.
- Intensive BP therapy offers less cardiovascular protection to CKD patients with high PTH compared to those with lower PTH.
- FGF23 did not influence the outcomes or modify the intervention's effects.
Background And Objectives:
The Systolic Blood Pressure Intervention Trial (SPRINT) demonstrated that intensive BP lowering reduced the risk of cardiovascular disease, but increased eGFR decline. Serum parathyroid hormone (PTH) and fibroblast growth factor-23 (FGF23) concentrations are elevated in CKD and are associated with cardiovascular disease. We evaluated whether intact PTH or intact FGF23 concentrations modify the effects of intensive BP control on cardiovascular events, heart failure, and all-cause mortality in SPRINT participants with CKD.
Design, Setting, Participants, & Measurements:
We measured PTH and FGF23 in 2486 SPRINT participants with eGFR<60 ml/min per 1.73 m2 at baseline. Cox models were used to evaluate whether serum PTH and FGF23 concentrations were associated with cardiovascular events, heart failure, and all-cause mortality, and whether PTH and FGF23 modified the effects of intensive BP control.
Results:
The mean age of this subcohort was 73 years, 60% were men, and mean eGFR was 46±11 ml/min per 1.73 m2. Median PTH was 48 (interquartile range [IQR], 35-67) pg/ml and FGF23 was 66 (IQR, 52-88) pg/ml. There were 261 composite cardiovascular events, 102 heart failure events, and 179 deaths within the subcohort. The adjusted hazard ratio (HR) per doubling of PTH concentration for cardiovascular events, heart failure, and all-cause mortality were 1.29 (95% confidence interval [95% CI], 1.06 to 1.57), 1.32 (95% CI, 0.96 to 1.83), and 1.04 (95% CI, 0.82 to 1.31), respectively. There were significant interactions between PTH and BP arm for both the cardiovascular (P-interaction=0.01) and heart failure (P-interaction=0.004) end points. Participants with a PTH above the median experienced attenuated benefits of intensive BP control on cardiovascular events (adjusted HR, 1.02; 95% CI, 0.72 to 1.42) compared with participants with a PTH below the median (adjusted HR, 0.67; 95% CI, 0.45 to 1.00). FGF23 was not independently associated with any outcome and did not modify the effects of the intervention.
Conclusions:
SPRINT participants with CKD and a high serum PTH received less cardiovascular protection from intensive BP therapy than participants with a lower serum PTH.
More Related Videos
 08:27
A Real-World High-Intensity Interval Training Protocol for Cardiorespiratory Fitness Improvement
Published on: February 22, 2022
 07:40
Impact of High-intensity Interval Exercise and Moderate-Intensity Continuous Exercise on the Cardiac Troponin T Level at an Early Stage of Training
Published on: October 10, 2019
Related Concept Videos
 03:28
Vapor Pressure Lowering
 01:25
Chronic Kidney Disease I: Introduction
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:05
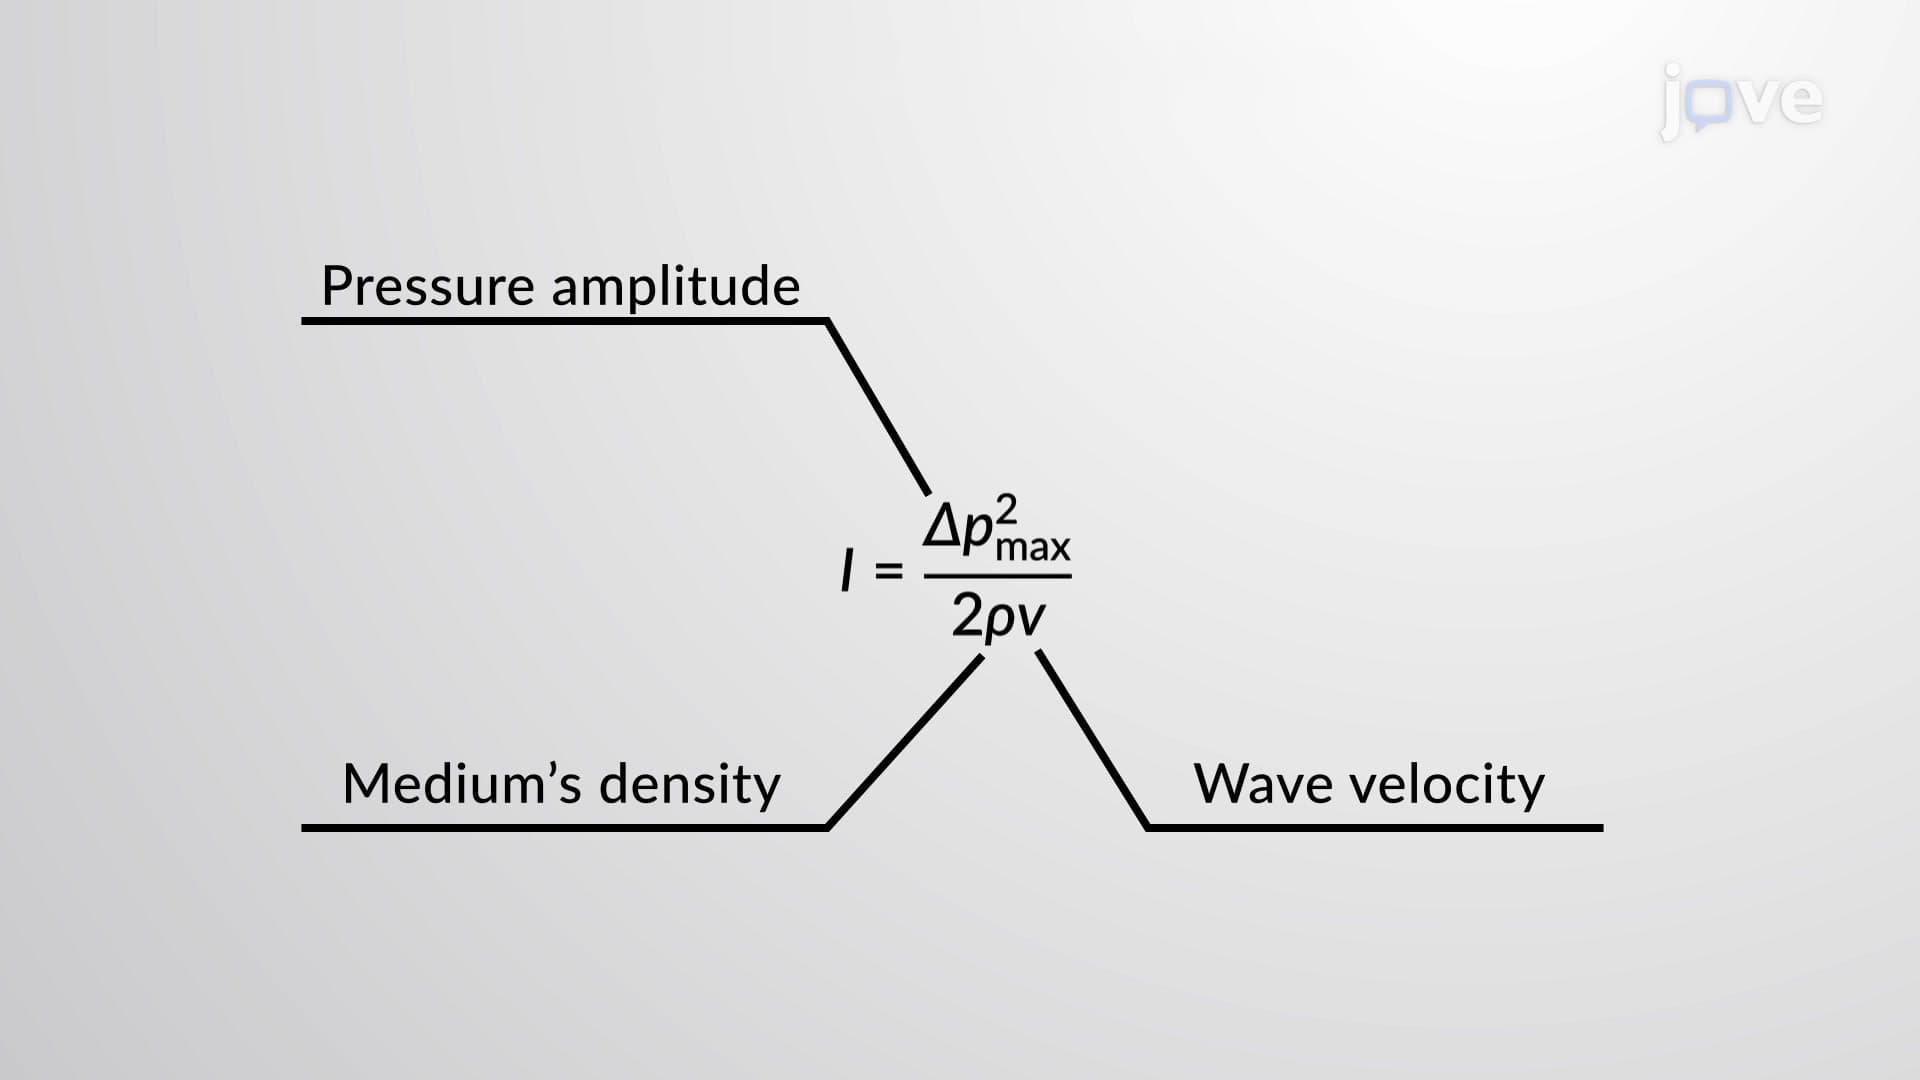
Intensity and Pressure of Sound Waves
Unlike the time average of a sinusoidal term, which is zero since it is positive...