Related Experiment Video
Updated: Aug 9, 2026


Primary Outcome Assessment in a Pig Model of Acute Myocardial Infarction
Published on: October 14, 2016
[Ventricular late potentials in acute myocardial infarct]
H W Höpp1, I Treis-Müller, A Osterspey
1Medizinische Klinik III der Universität zu Köln.

Insights
Ventricular late potentials indicate delayed conduction in ischemic heart muscle, signaling reentry circuits. Their detection aids in assessing ventricular function and predicting arrhythmias or sudden cardiac death risk.
Area of Science:
- Cardiology
- Electrophysiology
- Cardiac Pathophysiology
Context:
- Ventricular late potentials (VLPs) are linked to myocardial ischemia and reentry circuits.
- VLPs correlate with impaired ventricular function and increased risk of tachyarrhythmias or sudden cardiac death.
- Arrhythmias in acute myocardial infarction involve distinct pathomechanisms across three phases.
Purpose:
- To differentiate arrhythmogenesis mechanisms in acute myocardial infarction.
- To explain the role of ventricular late potentials in various cardiac conditions.
- To describe the detection methods for ventricular late potentials.
Summary:
- Phase 1 (early hours): Injury currents from ischemia trigger reentry tachycardia.
- Phase 2 (hours to days): Subendocardial Purkinje fibers exhibit focal arrhythmogenicity (abnormal automaticity).
- Phase 3 (days to weeks) & Reperfusion: Reentry mechanisms dominate due to electrophysiologic changes and infarct scar barriers.
Impact:
- Understanding these mechanisms aids in predicting and managing ventricular arrhythmias.
- Detection of VLPs, invasively or noninvasively, provides prognostic information.
- Differentiated understanding of arrhythmia phases in myocardial infarction improves clinical strategies.
Abstract:
Ventricular late potentials are regarded as an expression of delayed impulse conduction in an area of myocardial ischemia and, accordingly, indicative of a preformed reentry circuit. Late potentials can be detected in chronic, stable coronary artery disease and their presence correlates closely with impairment of ventricular function and with the probability of future occurrence of tachyarrhythmic events or sudden cardiac death. While repetitive ventricular arrhythmias in the chronic stage of coronary artery disease result almost invariably from circling intraventricular wavefronts, tachyarrhythmias associated with acute myocardial infarction appear attributable to differing pathomechanisms. According to experimental studies, in acute myocardial infarction, three phases of arrhythmogenesis can be differentiated: phase 1 encompasses the first hours after vessel occlusion which generally corresponds with the prehospital phase. Due to the difference in potential of up to 25 mV between ischemic and nonischemic cardiac muscle areas, an injury current is called into existence which leads to depolarization of normal cardiac muscle tissue. The ectopic impulses so precipitated, the conduction of which is supported by the functional inhomogeneity of the infarcted region, are capable of initiating reentry tachycardia. During phase 2, a few hours to days after the ischemic event, only the subendocardial Purkinje fibers in the infarcted region exhibit focal arrhythmogenicity. In contrast to the working myocardial cells, the latter survive due to their immediate proximity to the cardiac chamber and show, ischemia-induced, a propensity to high-frequency impulse formation in terms of abnormal automaticity. Similar to the experimental findings, the cause of the frequently-observed ventricular arrhythmias in the early hospital phase appears predominantly attributable to a focal arrhythmia mechanism. During phase 3, several days to weeks after the acute myocardial ischemic event, reentry mechanisms again are in the foreground in which the electrophysiologic changes in the Purkinje fibers, in terms of increasing desynchronization, together with conduction barriers arising through the infarct scar, pave the way for reentry phenomenon. After abrupt restoration of patency of a previously occluded vessel the very frequent "reperfusion arrhythmias" are also attributable primarily to reentry mechanisms due to inhomogeneous improvement of the conduction properties in the region of the reperfused myocardium. Ventricular late potentials can be registered both invasively by means of epi- or endocardial leads as well as noninvasively from the body surface.(ABSTRACT TRUNCATED AT 400 WORDS)
More Related Videos
 08:19
Transthoracic Echocardiography to Assess Post-Resuscitation Left Ventricular Dysfunction After Acute Myocardial Infarction and Cardiac Arrest in Pigs
Published on: July 12, 2022
 10:17
Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Related Concept Videos
 01:19
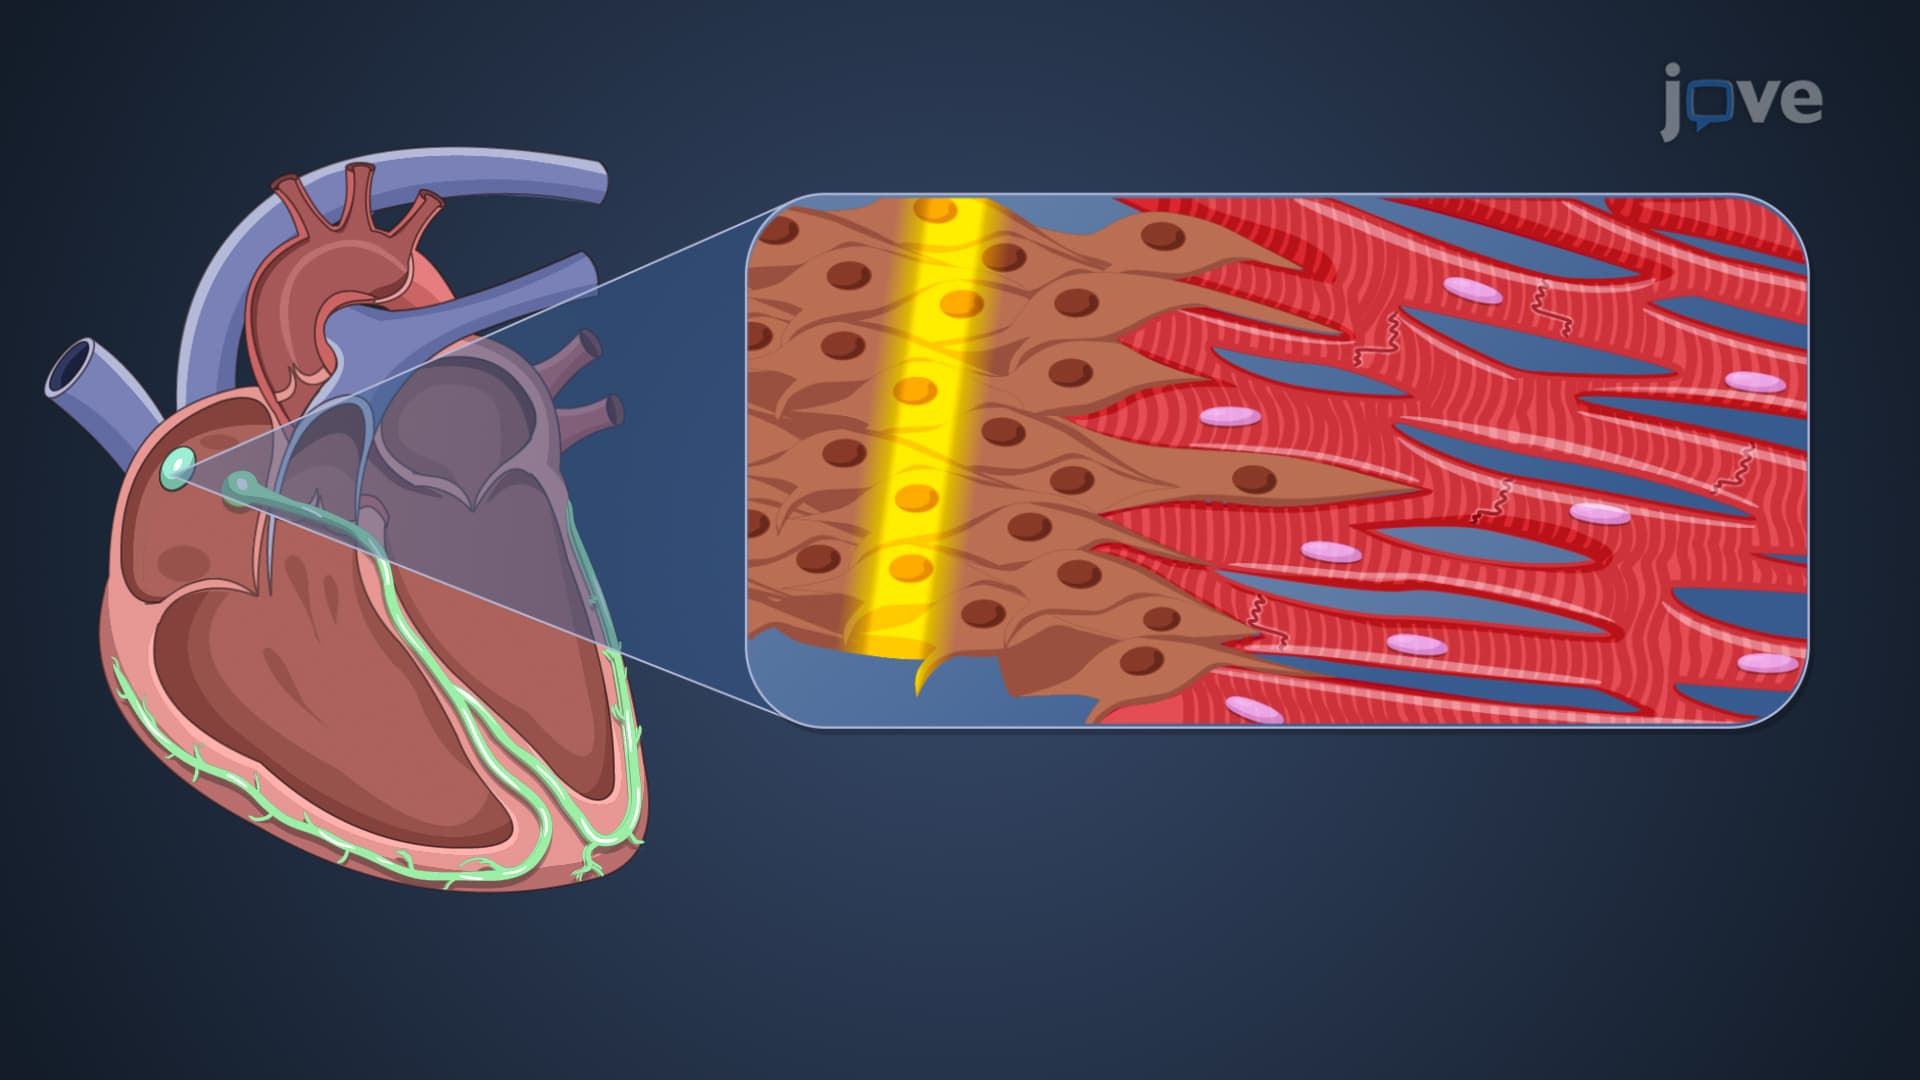
Electrophysiology of Normal Cardiac Rhythm
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:30
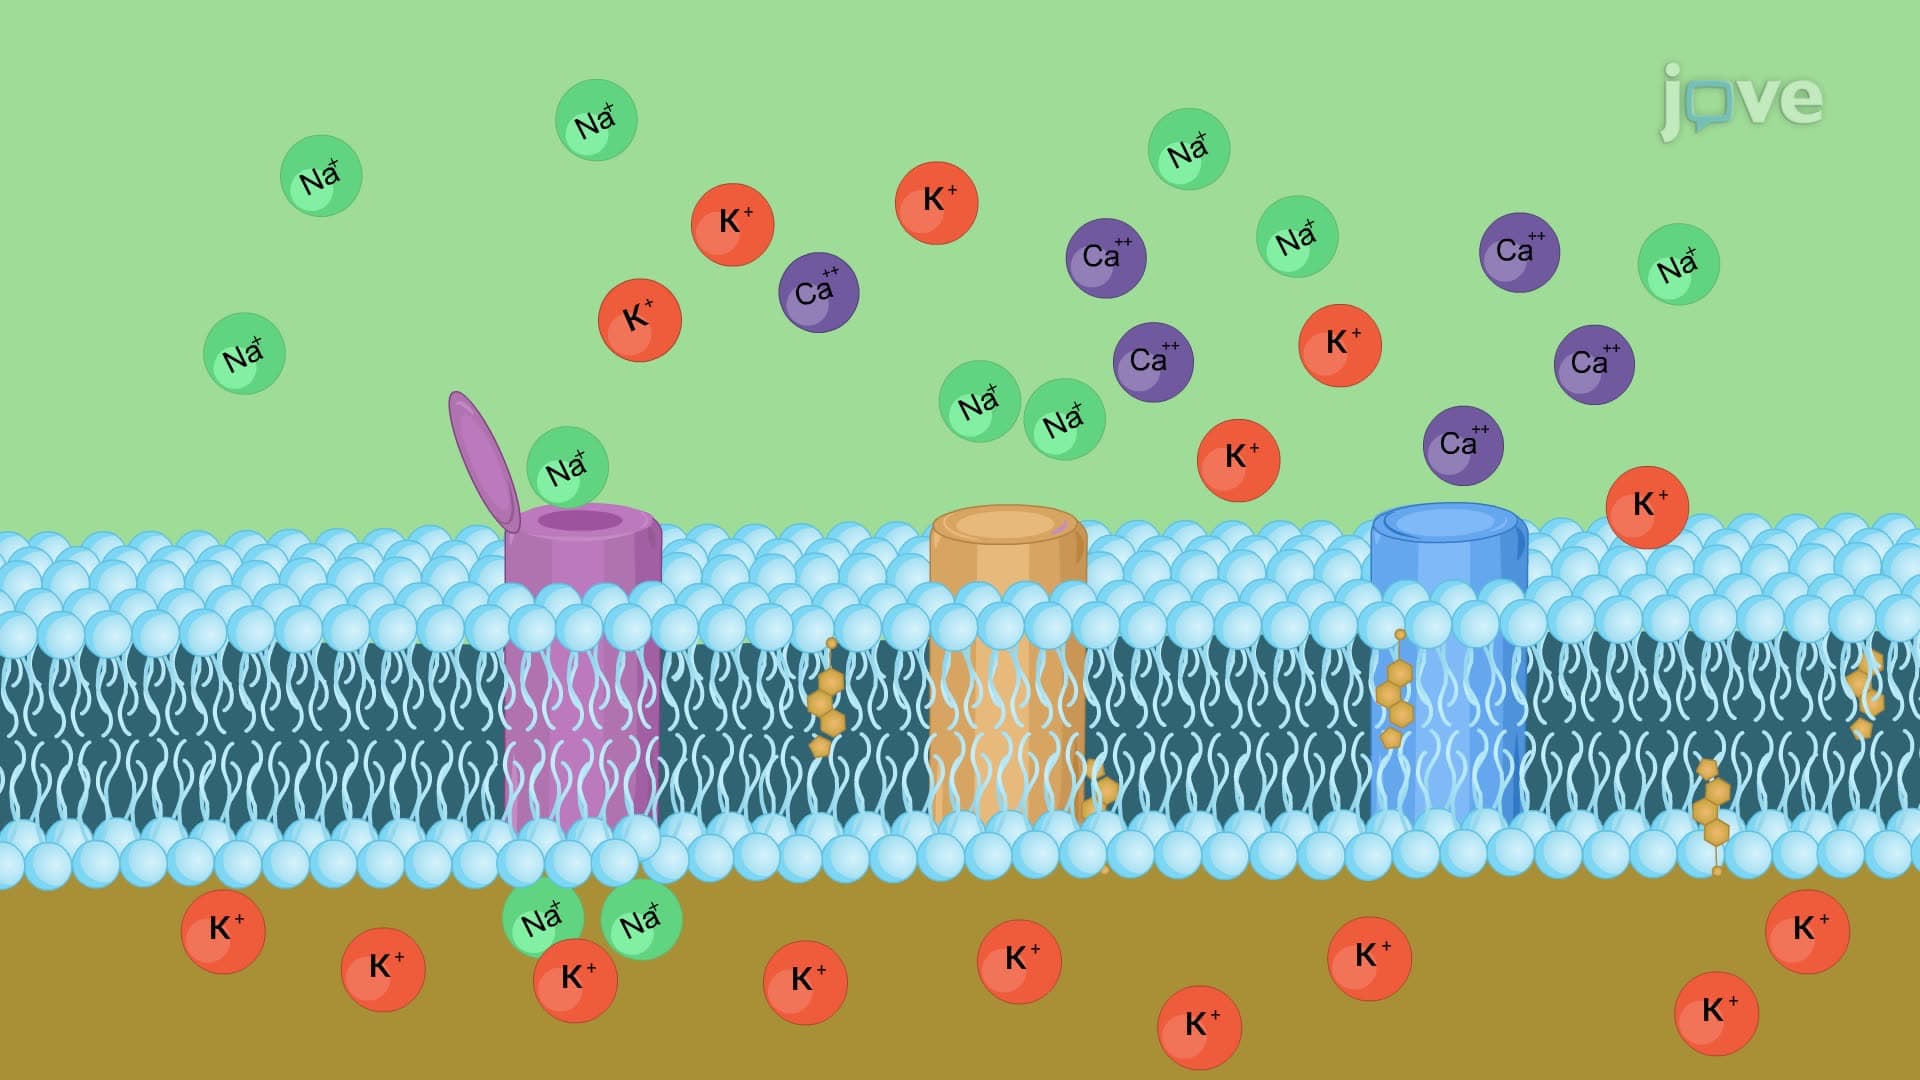
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias