Related Experiment Video
Updated: Feb 2, 2026

Author Spotlight: Development of a Minimally Invasive Large-Animal Model for Reliable and Reproducible Cardiovascular Research
Published on: October 20, 2023
Low-Gradient Aortic Stenosis: Solving the Conundrum Using Multi-Modality Imaging
David Messika-Zeitoun1, Jae K Oh2, Yan Topilsky3
1University of Ottawa Heart Institute, Ottawa, Ontario, Canada.

Insights
Differentiating true severe aortic stenosis (AS) from pseudo-severe AS is crucial for patient management. Combining dobutamine echocardiography with aortic valve calcification (AVC) scoring improves diagnostic accuracy, especially in patients with discordant grading.
Area of Science:
- Cardiology
- Medical Imaging
Background:
- Aortic stenosis (AS) severity assessment can be challenging, particularly in patients with reduced or preserved left ventricular ejection fraction (LVEF) and discordant echocardiographic findings (e.g., mean pressure gradient <40 mm Hg with aortic valve area <1 cm²).
- Distinguishing true severe AS from pseudo-severe AS (moderate AS with secondary left ventricular dysfunction) is critical for appropriate treatment decisions.
Purpose of the Study:
- To evaluate the utility of dobutamine stress echocardiography and computed tomography-based aortic valve calcification (AVC) scoring in accurately assessing AS severity.
- To differentiate between true severe AS and pseudo-severe AS in patients with ambiguous echocardiographic results.
Main Methods:
- Low-dose dobutamine echocardiography was used to assess contractile reserve in patients with reduced LVEF, identifying "true-severe AS" (PV ≥4 m/s or MPG >30-40 mm Hg) versus "pseudo-severe AS" (AVA peak ≥1 cm² with MPG <30-40 mm Hg).
- Aortic valve calcification (AVC) scoring via computed tomography (CT) was employed as a flow-independent method (thresholds: >1250 AU in women, >2000 AU in men for severe AS).
- The combination of dobutamine echocardiography and AVC scoring was analyzed for its effectiveness in AS severity assessment, including in patients with preserved LVEF and discordant grading.
Main Results:
- Dobutamine stress echocardiography helps distinguish true severe AS from pseudo-severe AS in reduced LVEF patients, though interpretation can be challenging and contractile reserve is absent in 20-30%.
- AVC scoring is an accurate, flow-independent method for AS severity assessment, with specific thresholds indicating severe AS.
- Combining dobutamine echocardiography and AVC scoring enhances confidence in AS severity assessment, particularly in heterogeneous patient groups with preserved LVEF and discordant findings.
Conclusions:
- Aortic valve calcification scoring is a reliable method for assessing AS severity, especially in cases with ambiguous echocardiographic results.
- The combination of dobutamine stress echocardiography and AVC scoring provides high confidence in differentiating true severe AS from pseudo-severe AS.
- Further research is needed to determine optimal management strategies for patients with pseudo-severe AS.
Abstract:
Up to 1/3 of patients with both reduced or preserved left ventricular ejection fraction (LVEF), harbor a mean pressure gradient (MPG) < 40 mm Hg (peak velocity (PV) < 4 m/s), suggesting moderate aortic stenosis (AS) and an aortic valve area (AVA) < 1 cm2 suggesting severe AS raising uncertainties regarding AS severity and appropriate management. In patients with reduced LVEF, increased transvalvular flow and stroke volume ≥ 20% (i.e. contractile reserve) during low-dose dobutamine echocardiography enables distinguishing patients with "true-severe AS" (severe AS with secondary LV dysfunction, PV ≥ 4 m/s or MPG > 30-40 mm Hg at peak while AVA remains <1 cm2) from patients with "pseudo-severe AS" (moderate AS with associated LV dysfunction due to ischemic or dilated cardiomyopathy, AVA at peak ≥1 cm2 with a MPG < 30-40 mm Hg). However, interpretation of dobutamine stress echocardiography is often challenging, and absence of contractile reserve is observed in 20 to 30% of patients. Measurement of the degree of calcification (AVC) using computed tomography is an accurate and flow-independent method for the assessment of AS severity. A score > 1250 AU in women and >2000 UA in men strongly suggest severe AS. Combination of dobutamine echocardiography and AVC scoring enables assessment of AS severity with high confidence. The subset of patients with discordant grading and preserved LVEF is heterogenous and encompasses various conditions. A minority harbor a low flow state related to a reduced myocardial performance, an increased arterial afterload or combination of both. A low flow state is an important prognostic factor but does not provide any information regarding AS severity. Similarly to patients with reduced LVEF, assessment of the degree of AVC seems the best method to differentiate patients with pseudo-severe AS from patients with true severe AS. The latter should be referred for an intervention if symptomatic whereas the optimal management of the former subset remains uncertain.
Related Concept Videos
 01:26
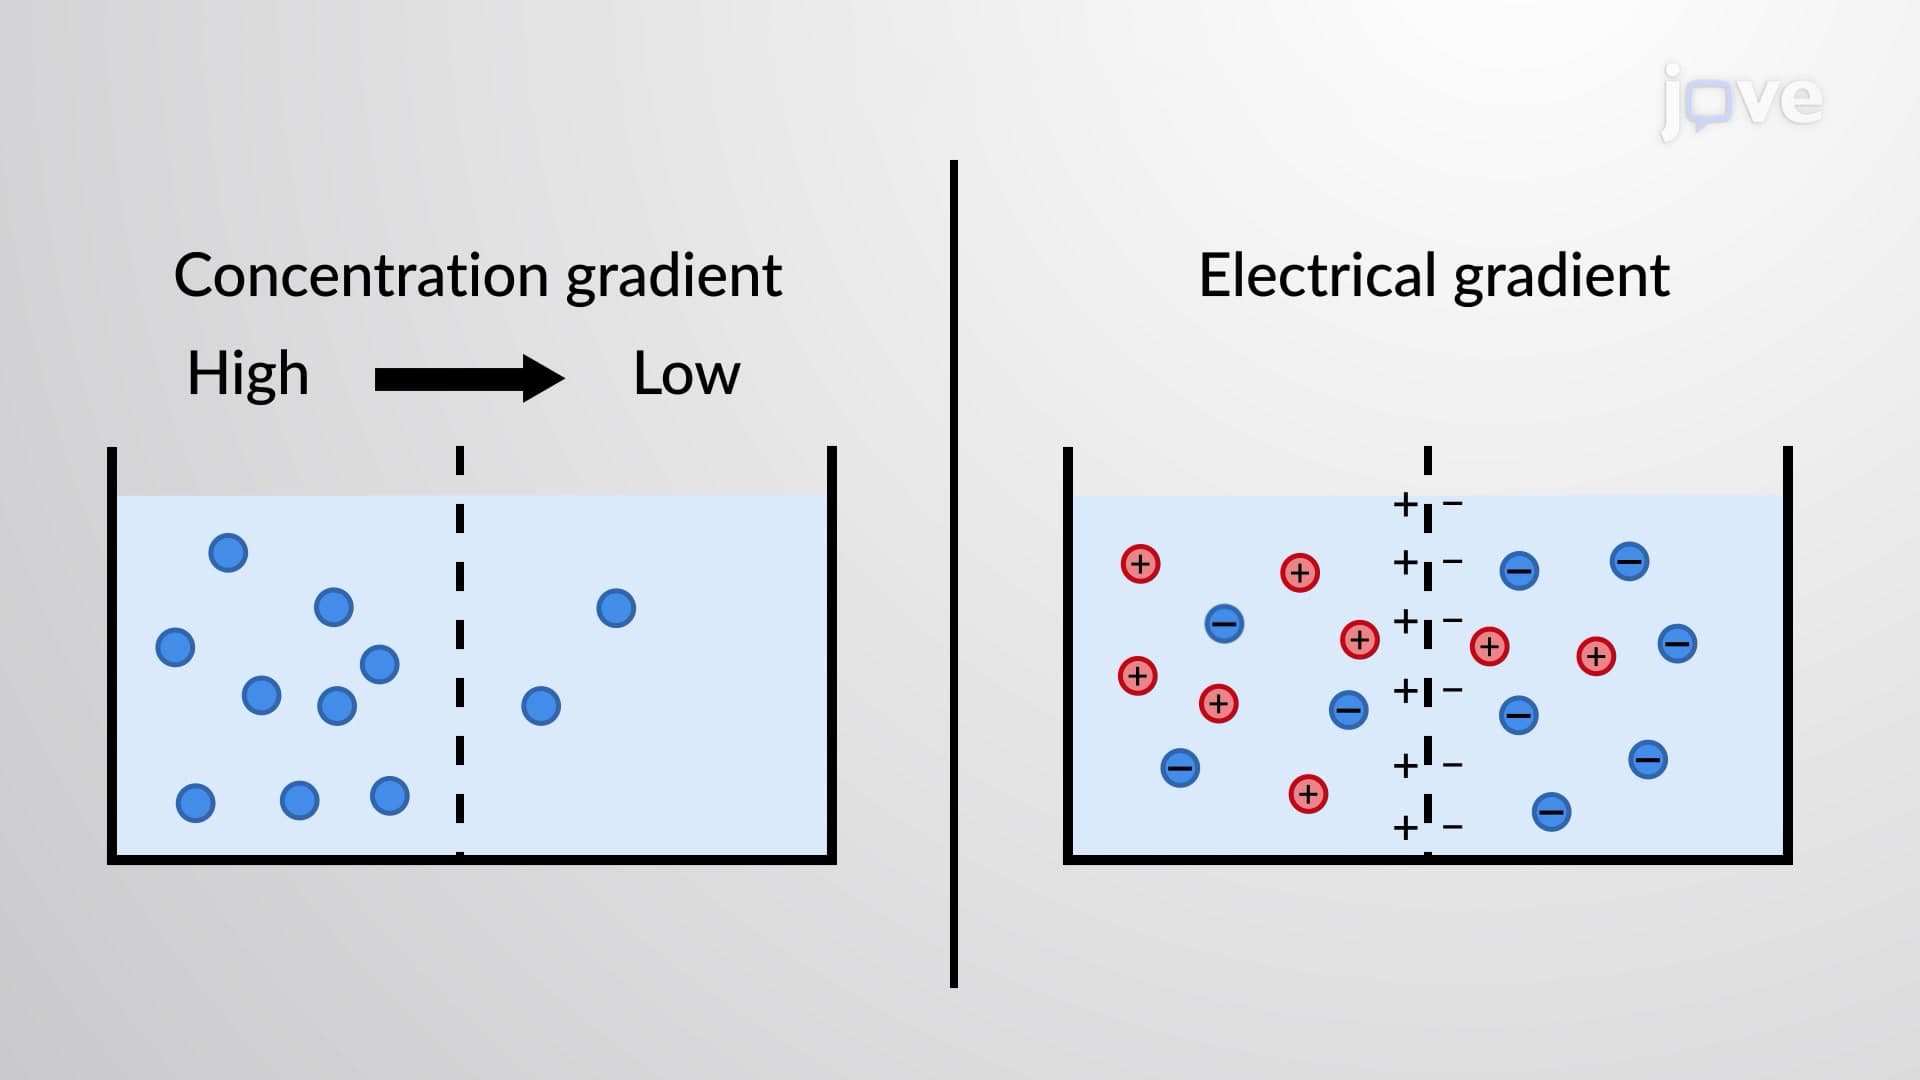
What is an Electrochemical Gradient?
The chemical gradient relies on differences in the abundance of a substance on the outside versus the inside of a cell and flows from areas of high to low ion concentration. In contrast, the electrical gradient revolves around an...
 01:15
Sensory Modalities
General senses refer to the broad category of sensory information detected by receptors in the body and can be further grouped into somatic and visceral senses. Somatic sensations include touch, pressure, temperature, and pain and are essential for navigating our environment and...
 01:22
Mitral Stenosis I: Introduction
 01:27
Energy Line and Hydraulic Gradient Line
 01:26
Mitral Stenosis III: Medical Management
 01:29
Problem-Solving