Related Experiment Video
Updated: Feb 2, 2026
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Laparoscopic Ventral Rectopexy Versus Stapled Transanal Rectal Resection for Treatment of Obstructed Defecation in
Khaled M Madbouly1, Ahmed D Mohii
1Department of Surgery, Section of Colon and Rectal Surgery, University of Alexandria, Alexandria, Egypt.

Background:
Obstructed defecation is a common complaint in coloproctology. Many anal, abdominal, and laparoscopic procedures are adopted to correct the underlying condition.
Objective:
The purpose of this study was to compare long-term functional outcome, recurrence rate, and quality of life between laparoscopic ventral rectopexy and stapled transanal rectal resection in the treatment of obstructed defecation.
Design:
This was a prospective randomized study.
Setting:
This study was performed at academic medical centers.
Patients:
Patients were included if they had obstructed defecation attributed to pelvic structural abnormalities that did not to respond to conservative measures. Exclusion criteria included nonrelaxing puborectalis, previous abdominal surgery, other anal pathology, and pudendal neuropathy.
Intervention:
Patients were randomly allocated to either laparoscopic ventral rectopexy (group 1) or stapled transanal rectal resection (group 2).
Main Outcome Measures:
The primary outcome measures were improvement of modified obstructed defecation score and recurrences after ≥3 years of follow-up. Secondary outcomes were postoperative complications, continence status using Wexner incontinence score, and quality of life using Patient Assessment of Constipation-Quality of Life Questionnaire.
Results:
The study included 112 patients (56 in each arm). ASA score II was reported in 32 patients (18 in group 1 and 14 in group 2; p = 0.12), whereas 3 patients in each group had ASA score III. Minor postoperative complications were seen in 11 patients (20%) of group 1 and 14 patients of group 2 (25%; p = 0.65). During follow-up, 3 patients had fecal urgency after stapled transanal rectal resection but no sexual dysfunction in either procedure. After 6 months, modified obstructed defecation score improvement >50% was reported in 73% versus 82% in groups 1 and 2 (p = 0.36). After a mean follow-up of 41 months, recurrences of symptoms were reported in 7% in group 1 versus 24% in group 2 (p = 0.04). Six months postoperation, perineal descent improved >50% in defecogram in 80% of group 1 versus no improvement in group 2. Quality of life significantly improved in both groups after 6 months; however a significant long-term drop (>36 months) was seen only in group 2.
Limitations:
Possible limitations of this study are the presence of a single operator and the absence of blindness of the technique for both patient and assessor.
Conclusions:
In elderly patients even with comorbidities, both laparoscopic ventral rectopexy and stapled transanal rectal resection are safe and can improve function of the anorectum in patients with obstructed defecation attributed to structural abnormalities. Laparoscopic ventral rectopexy has better long-term functional outcome, less complications, and less recurrences compared with stapled transanal rectal resection. Perineal descent only improves after laparoscopic ventral rectopexy. Stapled transanal rectal resection was shown not to be the first choice in elderly patients with obstructed defecation unless they had a medical contraindication to laparoscopic procedures. See Video Abstract at http://links.lww.com/DCR/A788.
More Related Videos
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
 04:41
Application of the En Bloc Concept Combined with Anatomic Resection in Laparoscopic Hepatectomy
Published on: March 10, 2023
Related Concept Videos
 01:26
Feces Formation and Defecation
The mass peristalsis then pushes the feces into the rectum, which stretches the rectal walls to activate...
 01:20
Bioequivalence Experimental Study Designs: Completely Randomized and Randomized Block Designs
 01:27
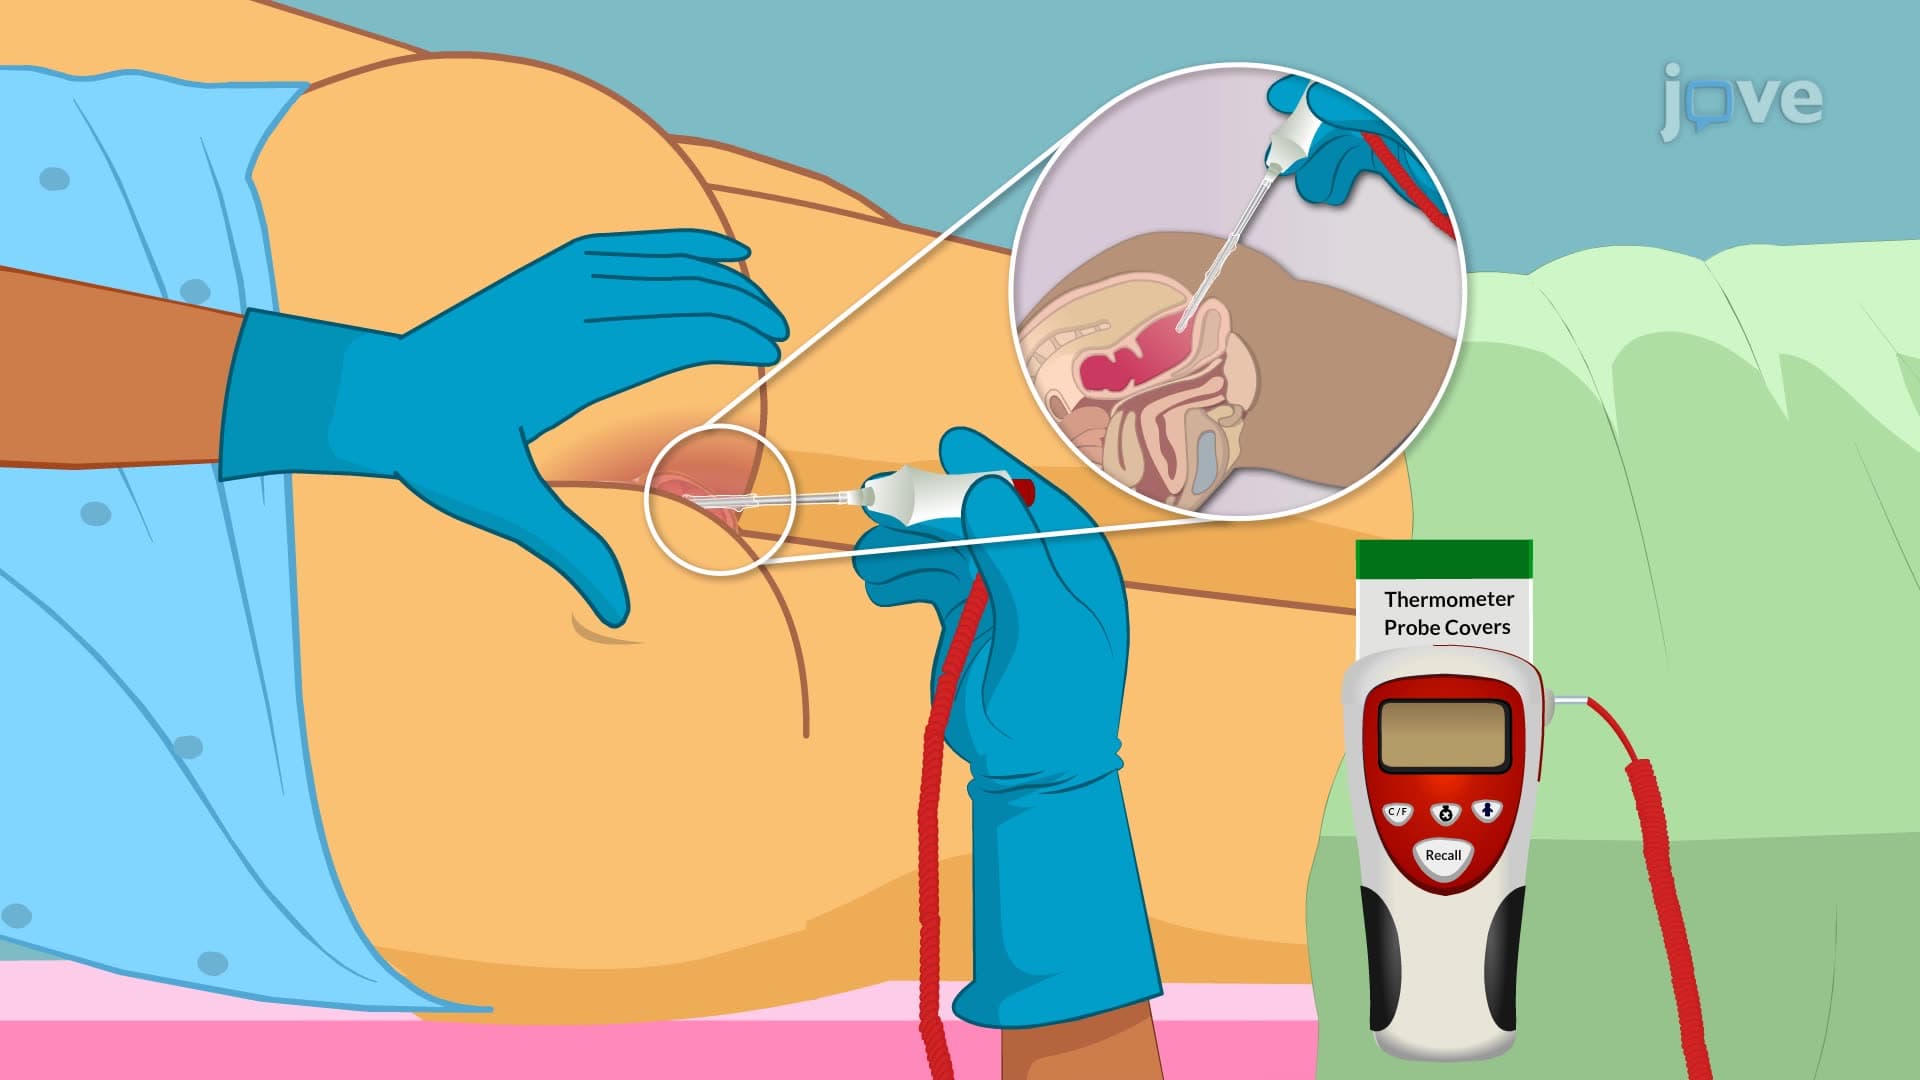
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:04
Random Error
 01:09
Random Variables
Uppercase letters such as X or Y denote a random variable. Lowercase letters like x or y denote the value of a random variable. If X is a random variable, then X is written in words, and x is given as a number.
For example, let X = the...
 01:13
Randomized Experiments
Simple randomization
Simple...