Related Experiment Video
Updated: Feb 2, 2026


A Structured Approach to Extubation in Mechanically Ventilated Rats
Published on: July 18, 2025
Hospital Costs Related to Early Extubation After Infant Cardiac Surgery
Kimberly E McHugh1, William T Mahle2, Matthew A Hall3
1Department of Pediatrics, Medical University of South Carolina, Charleston, South Carolina.

Insights
Implementing a clinical practice guideline (CPG) for early extubation significantly reduced hospital costs for infant tetralogy of Fallot (TOF) repair. The CPG did not impact costs for coarctation of the aorta (CoA) repair.
Area of Science:
- Pediatric Cardiology
- Health Services Research
- Clinical Economics
Background:
- The Pediatric Heart Network Collaborative Learning Study (PHN CLS) implemented a clinical practice guideline (CPG) to increase early extubation rates in infants undergoing repair for tetralogy of Fallot (TOF) and coarctation of the aorta (CoA).
- The economic impact of this CPG on hospital costs remained unstudied prior to this research.
Purpose of the Study:
- To evaluate the effect of the PHN CLS CPG on hospital costs associated with infant TOF and CoA repair.
- To determine if the observed cost changes at active sites exceeded secular trends seen in control sites.
Main Methods:
- Clinical data from 410 patients (96% of eligible) across four active and four control sites were linked with hospital cost data.
- Generalized linear mixed-effects models and a difference-in-difference approach were used to compare costs in pre- and post-CPG periods between active and control sites.
Main Results:
- Mean adjusted costs for TOF repair decreased by 27% at active sites post-CPG ($42,833 vs $56,304), while remaining unchanged at control sites ($47,007 vs $46,476).
- Significant cost reductions in the TOF cohort at active sites were observed in clinical, pharmacy, lab, and imaging categories.
- No significant changes in hospital costs were found for CoA repair at either active or control sites.
Conclusions:
- The early extubation CPG successfully reduced hospital costs for infant TOF repair, demonstrating a dual benefit of improved clinical outcomes and cost savings.
- The CPG did not yield similar cost reductions for infant CoA repair.
- This CPG offers a valuable strategy for optimizing both clinical results and healthcare expenditures in specific infant cardiac surgical procedures.
Background:
The Pediatric Heart Network Collaborative Learning Study (PHN CLS) increased early extubation rates after infant tetralogy of Fallot (TOF) and coarctation of the aorta (CoA) repair across participating sites by implementing a clinical practice guideline (CPG). The impact of the CPG on hospital costs has not been studied.
Methods:
PHN CLS clinical data were linked to cost data from Children's Hospital Association by matching on indirect identifiers. Hospital costs were evaluated across active and control sites in the pre- and post-CPG periods using generalized linear mixed-effects models. A difference-in-difference approach was used to assess whether changes in cost observed in active sites were beyond secular trends in control sites.
Results:
Data were successfully linked on 410 of 428 eligible patients (96%) from four active and four control sites. Mean adjusted cost per case for TOF repair was significantly reduced in the post-CPG period at active sites ($42,833 vs $56,304, p < 0.01) and unchanged at control sites ($47,007 vs $46,476, p = 0.91), with an overall cost reduction of 27% in active versus control sites (p = 0.03). Specific categories of cost reduced in the TOF cohort included clinical (-66%, p < 0.01), pharmacy (-46%, p = 0.04), lab (-44%, p < 0.01), and imaging (-32%, p < 0.01). There was no change in costs for CoA repair at active or control sites.
Conclusions:
The early extubation CPG was associated with a reduction in hospital costs for infants undergoing repair of TOF but not CoA. This CPG represents an opportunity to both optimize clinical outcome and reduce costs for certain infant cardiac surgeries.
More Related Videos


Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:29
Drug Dosing: Infants and Children
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
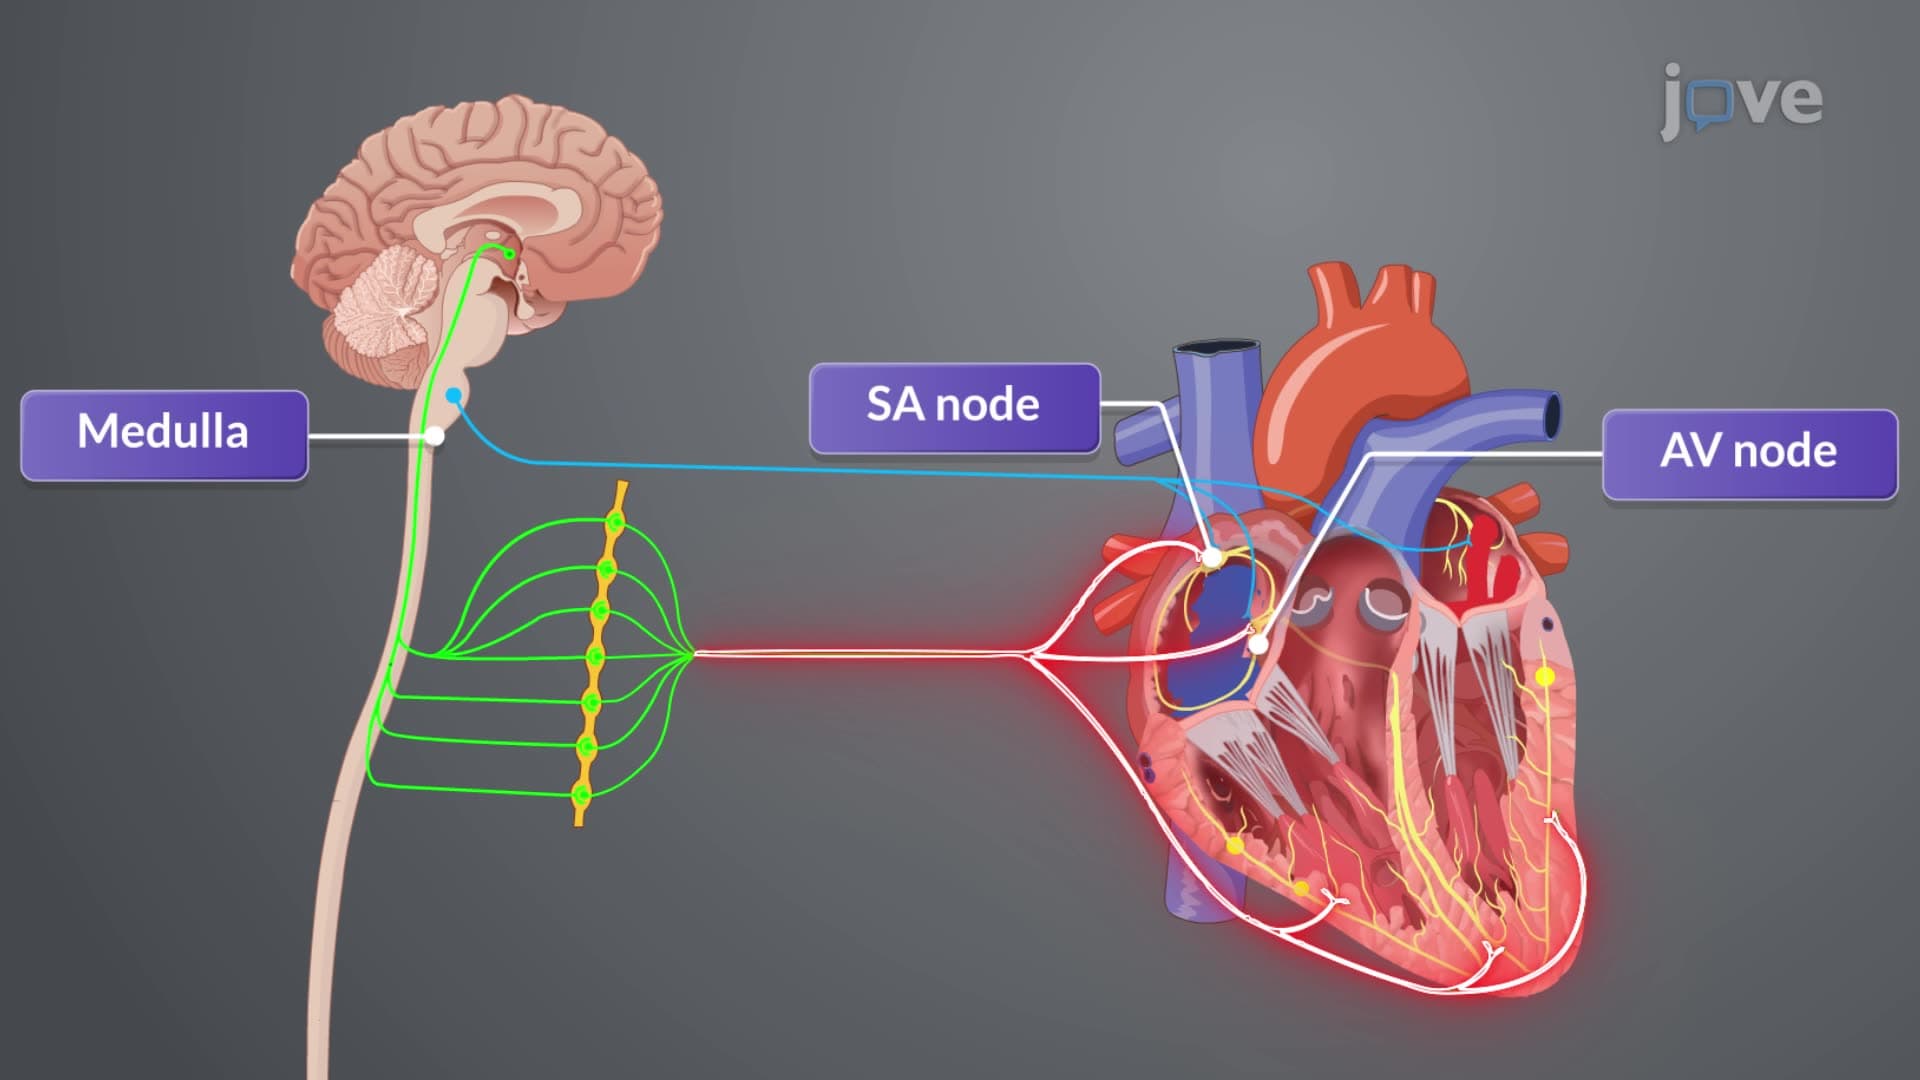
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...