Related Experiment Video
Updated: Feb 2, 2026
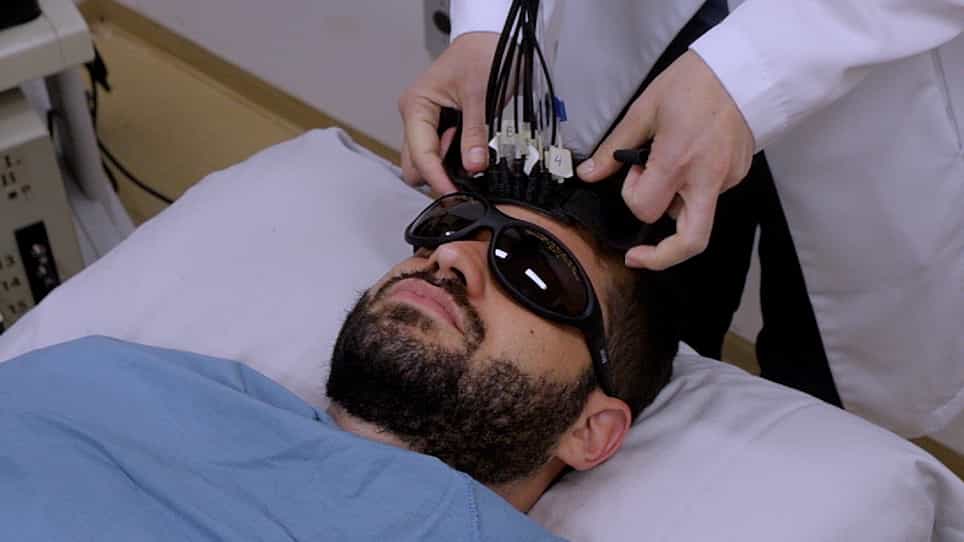

Real-Time Monitoring of Neurocritical Patients with Diffuse Optical Spectroscopies
Published on: November 19, 2020
Low Risk Monitoring in Neurocritical Care
Christian D Becker1,2,3, Christian Bowers4,5, Dipak Chandy2,3
1eHealth Center, Westchester Medical Center Health Network, Valhalla, NY, United States.

Abstract:
Background/Rationale: Patients are admitted to Intensive care units (ICUs) either because they need close monitoring despite a low risk of hospital mortality (LRM group) or to receive ICU specific active treatments (AT group). The characteristics and differential outcomes of LRM patients vs. AT patients in Neurocritical Care Units are poorly understood. Methods: We classified 1,702 patients admitted to our tertiary and quaternary care center Neuroscience-ICU in 2016 and 2017 into LRM vs. AT groups. We compared demographics, admission diagnosis, goal of care status, readmission rates and managing attending specialty extracted from the medical record between groups. Acute Physiology, Age and Chronic Health Evaluation (APACHE) IVa risk predictive modeling was used to assess comparative risks for ICU and hospital mortality and length of stay between groups. Results: 56.9% of patients admitted to our Neuroscience-ICU in 2016 and 2017 were classified as LRM, whereas 43.1% of patients were classified as AT. While demographically similar, the groups differed significantly in all risk predictive outcome measures [APACHE IVa scores, actual and predicted ICU and hospital mortality (p < 0.0001 for all metrics)]. The most common admitting diagnosis overall, cerebrovascular accident/stroke, was represented in the LRM and AT groups with similar frequency [24.3 vs. 21.3%, respectively (p = 0.15)], illustrating that further differentiating factors like symptom duration, neurologic status and its dynamic changes and neuro-imaging characteristics determine the indication for active treatment vs. observation. Patients with intracranial hemorrhage/hematoma were significantly more likely to receive active treatments as opposed to having a primary focus on monitoring [13.6 vs. 9.8%, respectively (p = 0.017)]. Conclusion: The majority of patients admitted to our Neuroscience ICU (56.9%) had <10% hospital mortality risk and a focus on monitoring, whereas the remaining 43.1% of patients received active treatments in their first ICU day. LRM Patients exhibited significantly lower APACHE IVa scores, ICU and hospital mortality rates compared to AT patients. Observed-over-expected ICU and hospital mortality ratios were better than predicted by APACHE IVa for low risk monitored patients and close to prediction for actively treated patients, suggesting that at least a subset of LRM patients may safely and more cost effectively be cared for in intermediate level care settings.


Related Concept Videos
 01:12
Relative Risk
 01:21
Interdisciplinary Care: The Health Care Team-I
Physicians
The physician's primary responsibility is to diagnose illness and direct the medical or surgical treatment of the condition. The authority to admit patients to a healthcare agency or institution and practice care within that setting is granted to physicians by the healthcare agency or institution...
 01:18
Interdisciplinary Care: The Health Care Team-II
Physical Therapist
A physical therapist (PT) aims to restore function or prevent additional impairment in a patient following an injury or disease. Massage, heat, cold, water, sonar waves, exercises, and electrical stimulation are some treatments used by PTs to treat...
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:25
Continuing Care
 01:22
Standards of Care I