Related Experiment Video
Updated: Feb 2, 2026
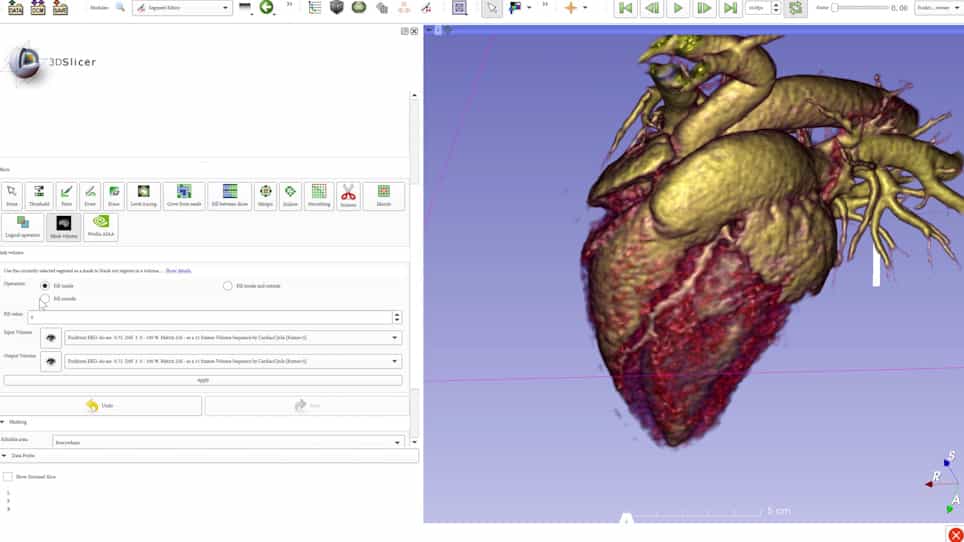
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Transcatheter aortic valve replacement (TAVR) leads to an increase in the subendocardial viability ratio assessed by
Claudia Müller1, Georg Goliasch1, Stefan Schachinger1
1Department of Internal Medicine II, Division of Cardiology, Medical University of Vienna, Vienna, Austria.

Background:
Pulse wave analysis (PWA) is a useful tool for non-invasive assessment of central cardiac measures as subendocardial perfusion (Subendocardial Viability Ratio, SEVR) or contractility (dP/dtmax). The immediate influence of transcatheter aortic valve replacement (TAVR) on these indices has not been investigated yet.
Methods:
We prospectively enrolled 40 patients presenting with severe aortic stenosis receiving TAVR. Central pressure curves were derived from radial and carotid sites using PWA up to 2 days before and 7 days after TAVR. Parameters were compared between peripheral measurement sites. Changes in SEVR, dP/dtmax and in indices of vascular stiffness were assessed. Additionally, association of these variables with clinical outcome was evaluated during a 12-month follow-up.
Results:
Central waveform parameters were comparable between measurement sites. SEVR, but not dP/dtmax, augmentation Index (AIx) or augmentation pressure height (AGPH) correlated significantly with disease severity reflected by peak transvalvular velocity and mean transvalvular pressure gradient over the aortic valve (Vmax, ΔPm) [r = -0.372,p = 0.029 for Vmax and r = -0.371,p = 0.021 for ΔPm]. Vmax decreased from 4.5m/s (IQR:4.1-5.0) to 2.2m/s (IQR:1.9-2.7), (p<0.001). This resulted in a significant increase in SEVR [135.3%(IQR:115.5-150.8) vs. 140.3%(IQR:123.0-172.5),p = 0.039] and dP/dtmax [666mmHg(IQR:489-891) vs. 927mmHg(IQR:693-1092),p<0.001], and a reduction in AIx [154.8%(IQR:138.3-171.0) vs. 133.5%(IQR:128.3-151.8),p<0.001] and AGPH [34.1%(IQR:26.8-39.0) vs. 25.0%(IQR 21.8-33.7),p = 0.002], confirming the beneficial effects of replacing the stenotic valve. No association of these parameters could be revealed with outcome.
Conclusions:
PWA is suitable for assessing coronary microcirculation and contractility mirrored by SEVR and maxdP/dt in the setting of aortic stenosis. PWA parameters attributed to vascular properties should be interpreted with caution.
More Related Videos


Related Concept Videos
 01:17
Increased pulse rate
Many factors can elevate the risk of developing tachycardia. These include advanced age, a family history of arrhythmias, and an...
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for:
 01:11
Pulse Assessment Sites
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:22
Mitral Valve Prolapse II: Assessment and Management