

Percutaneous Vertebral Augmentation for Osteoporotic Vertebral Compression Fracture in the Midthoracic Vertebrae
Jin Liu1, Jing Tang2, Yu Zhang1
1Department of Orthopaedics, Chengdu First People's Hospital, Chengdu, China.

Objective:
Data reporting percutaneous vertebroplasty (PVP) or percutaneous balloon kyphoplasty (PKP) application to the midthoracic vertebrae remain limited. This study aimed to summarize our experiences and explore the efficacy and safety of PVP or PKP in dealing with osteoporotic vertebral compression fracture (OVCF) in the midthoracic vertebrae.
Methods:
Patients receiving PVP or PKP for midthoracic OVCF in our institution from January 2015 to January 2018 were retrospectively enrolled. All patients were grouped according to cement augmentation procedure types, surgical approaches, and puncture routes. All patients underwent a postoperative follow-up of 2-36 months. Visual analog scale (VAS) and ECOG Scale of Performance Status scores were evaluated pre- and postoperatively. Cement distribution and rate of cement leakage were assessed by radiographs. Associations of these variables and clinical scores and radiographic indices were analyzed.
Results:
A total of 101 consecutive patients with 111 fractured centrums were enrolled. Both VAS and ECOG Scale of Performance Status scores of all patients decreased significantly after the operation, and progressively decreased at the final follow-up. The cement distribution of the bipedicular group was significantly better than the unipedicular group, but the total leakage rate of the former (71.7%) was significantly higher than the latter (43.1%). The rate of epidural cement leakage in the PKP group (5.4%) was significantly lower than that of the PVP group (20.3%), whereas the left puncture group (28.6%) was significantly higher than that of the right puncture group (2.7%).
Conclusions:
PKP and a bipedicular approach can help improve cement distribution and reduce the epidural cement leakage rate and therefore should be preferred over PVP or a unipedicular approach in OVCF of the midthoracic vertebrae.
More Related Videos

Related Concept Videos
 01:27
Muscles of the Vertebral Column
Superficial Layer:
The superficial layer consists primarily of the splenius muscles, which include the splenius capitis and splenius cervicis. These muscles are mainly responsible for the head and cervical spine movements, including extension, rotation, and lateral bending. The splenius capitis...
 01:28
Articulations of the Vertebral Column
 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:30
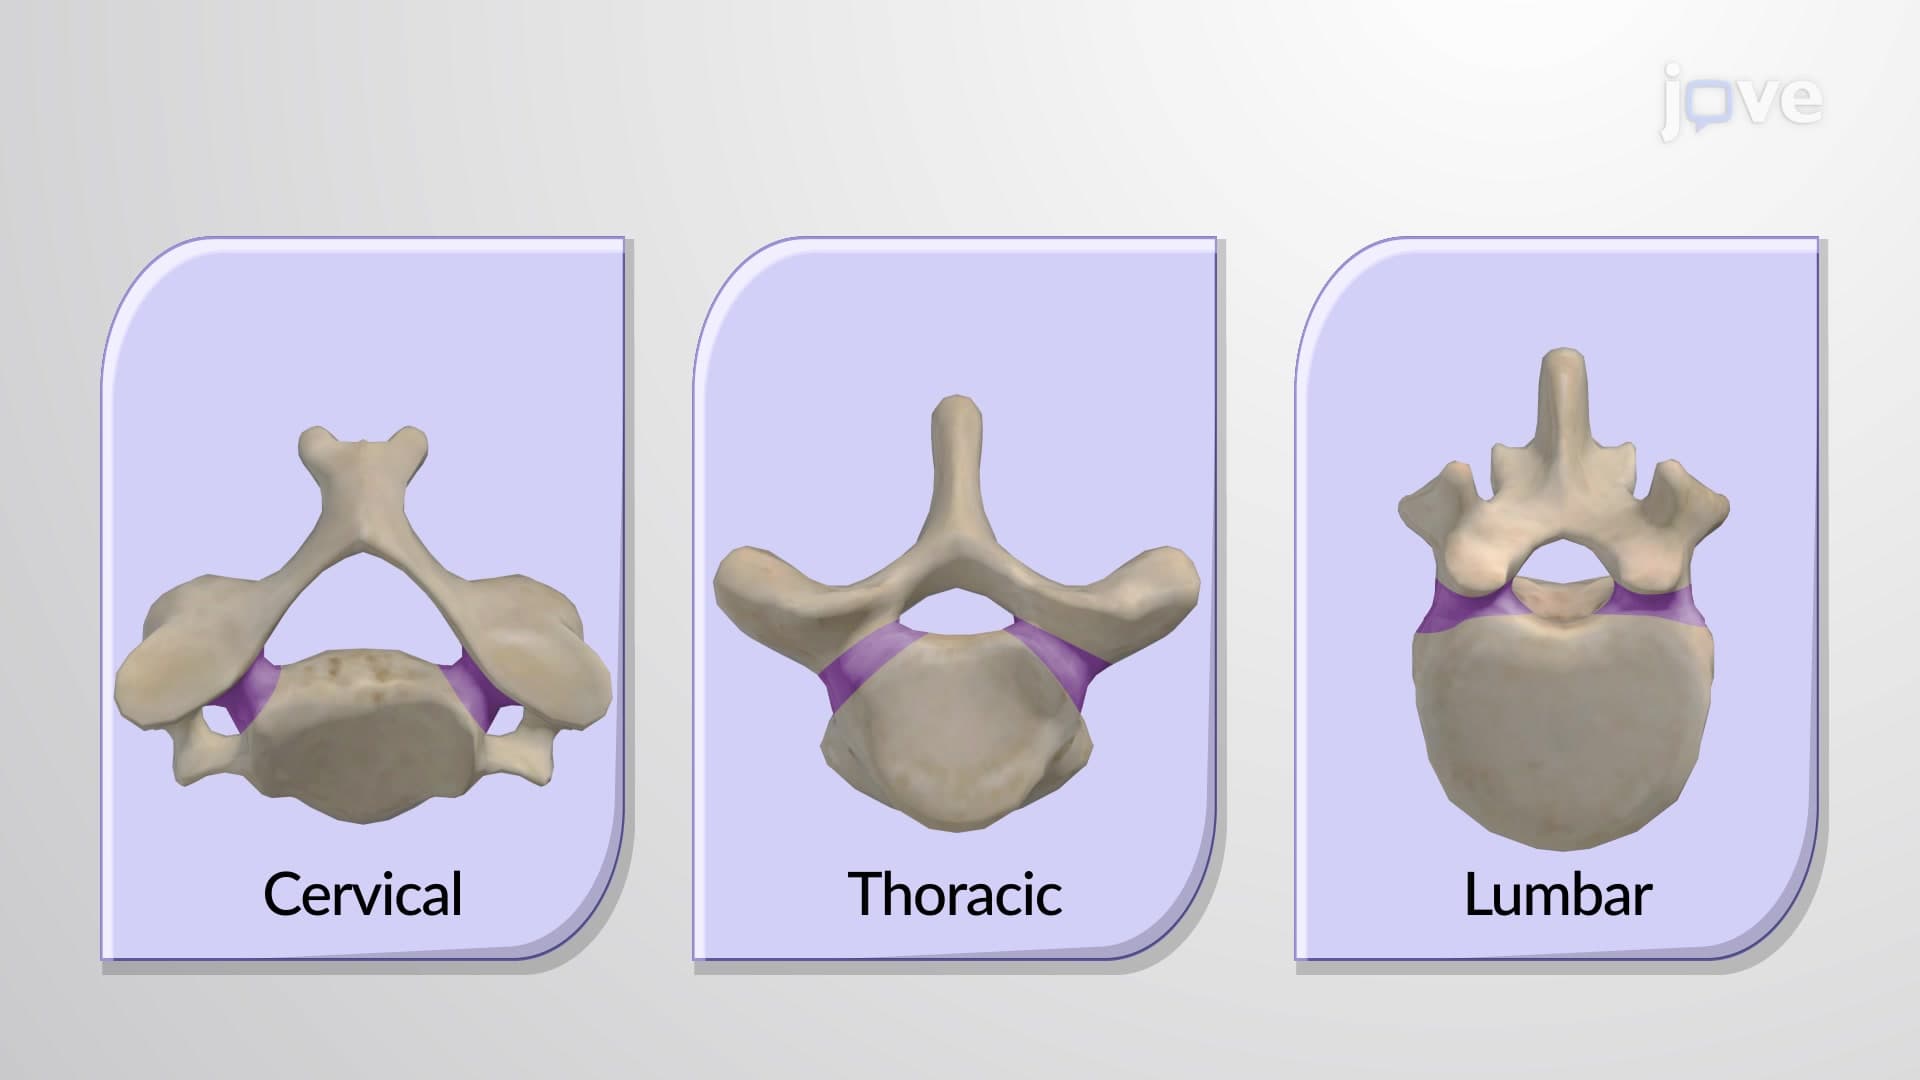
General Structure of a Vertebra
 01:23
Behavior of Concrete Under Compressive Load
As the concrete specimen fractures under...