Related Experiment Video
Updated: Feb 2, 2026
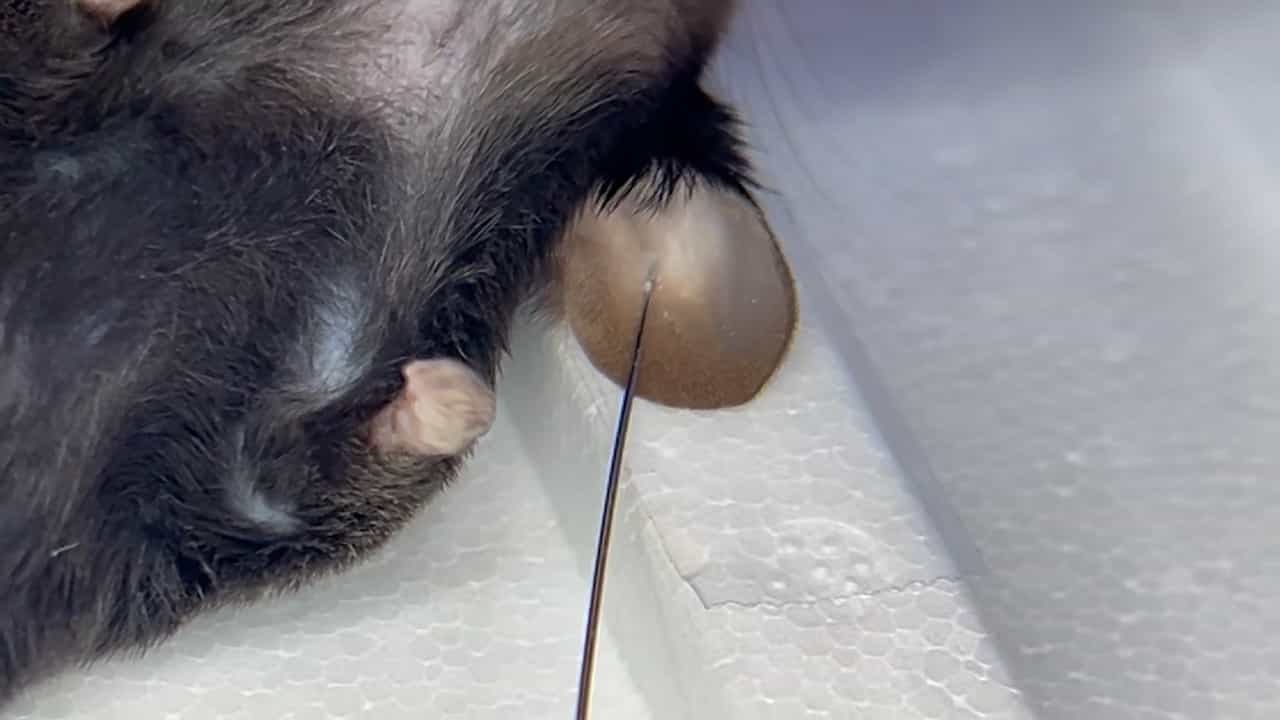

Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
Small-Cell Lung Cancer Comorbid with Pulmonary Mycobacterium avium Infection: A Case Report
Masahiro Yamasaki1, Kunihiko Funaishi2, Naomi Saito3
1Department of Respiratory Disease, Hiroshima Red Cross Hospital and Atomic-Bomb Survivors Hospital, Hiroshima, Japan, myamasanjp@yahoo.co.jp.

Background:
Small-cell lung cancer (SCLC) rarely coexists with pulmonary Mycobacterium avium intracellular complex (MAC) infection. The key drug for SCLC treatment is etoposide, which is metabolized by cytochrome P-450 (CYP) 3A4. Meanwhile, the key drugs for pulmonary MAC infection are clarithromycin (CAM) and rifampicin (RFP), and their metabolism influences CYP3A4. Therefore, treatment of concurrent SCLC and pulmonary MAC infection is difficult, and to the best of our knowledge, no report of treatments for concurrent SCLC and pulmonary MAC infection has been published. Patient Concerns and Diagnoses: A 65-year-old man presented to our hospital with abnormal findings of chest computed tomography: (1) a hilar region nodule in the left lung and mediastinal lymphadenopathy and (2) a thick-walled cavity lesion in the right upper lobe of the lung. After further examinations, the former lesions were diagnosed as SCLC, cT4N3M0, stage IIIC and the latter as pulmonary MAC infection, fibrocavitary disease.
Interventions And Outcomes:
Concurrent treatment was conducted with discontinuation of CAM and RFP before and after etoposide administration. Specifically, intravenous cisplatin and etoposide were administered on day 1 and days 1-3, respectively, and CAM, RFP, and ethambutol (EB) were administered orally on days 6-22 every 4 weeks. Concurrent radiotherapy was added to the drug administration on days 1-27 of the first cycle. The chemotherapy was continued for 4 cycles, followed by continuation of CAM and RFP administration. EB was discontinued because of optic nerve disorder. The treatments were conducted completely and safely, and both of the SCLC lesions and the MAC lesion were improved.
Conclusions:
Treatments for concurrent SCLC and pulmonary MAC infection may be successfully conducted with discontinuation of CAM and RFP before and after etoposide administration.
Related Concept Videos
 01:47
Lung Capacity
 01:24
Data Reporting and Recording
 01:25
Types of Reports I: Hands-off Report
Following are the key components and categories of hand-off reports:
Purpose and Process:
 01:21
Types of Reports II: Incident or Occurrence Report
Purposes:
In the healthcare industry, reports play a crucial role in documenting incidents within an agency. The primary objective of these reports is to ensure patient safety, uphold the...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...