Related Experiment Video
Updated: Feb 2, 2026


MRI-guided dmPFC-rTMS as a Treatment for Treatment-resistant Major Depressive Disorder
Published on: August 11, 2015
Combining mirtazapine with SSRIs or SNRIs for treatment-resistant depression: the MIR RCT
David Kessler1, Alison Burns1, Debbie Tallon1
1Centre for Academic Mental Health, School of Social and Community Medicine, University of Bristol, Bristol, UK.

Background:
Depression is usually managed in primary care and antidepressants are often the first-line treatment, but only half of those treated respond to a single antidepressant.
Objectives:
To investigate whether or not combining mirtazapine with serotonin-noradrenaline reuptake inhibitor (SNRI) or selective serotonin reuptake inhibitor (SSRI) antidepressants results in better patient outcomes and more efficient NHS care than SNRI or SSRI therapy alone in treatment-resistant depression (TRD).
Design:
The MIR trial was a two-parallel-group, multicentre, pragmatic, placebo-controlled randomised trial with allocation at the level of the individual.
Setting:
Participants were recruited from primary care in Bristol, Exeter, Hull/York and Manchester/Keele.
Participants:
Eligible participants were aged ≥ 18 years; were taking a SSRI or a SNRI antidepressant for at least 6 weeks at an adequate dose; scored ≥ 14 points on the Beck Depression Inventory-II (BDI-II); were adherent to medication; and met the International Statistical Classification of Diseases and Related Health Problems, Tenth Revision, criteria for depression.
Interventions:
Participants were randomised using a computer-generated code to either oral mirtazapine or a matched placebo, starting at a dose of 15 mg daily for 2 weeks and increasing to 30 mg daily for up to 12 months, in addition to their usual antidepressant. Participants, their general practitioners (GPs) and the research team were blind to the allocation.
Main Outcome Measures:
The primary outcome was depression symptoms at 12 weeks post randomisation compared with baseline, measured as a continuous variable using the BDI-II. Secondary outcomes (at 12, 24 and 52 weeks) included response, remission of depression, change in anxiety symptoms, adverse events (AEs), quality of life, adherence to medication, health and social care use and cost-effectiveness. Outcomes were analysed on an intention-to-treat basis. A qualitative study explored patients' views and experiences of managing depression and GPs' views on prescribing a second antidepressant.
Results:
There were 480 patients randomised to the trial (mirtazapine and usual care, n = 241; placebo and usual care, n = 239), of whom 431 patients (89.8%) were followed up at 12 weeks. BDI-II scores at 12 weeks were lower in the mirtazapine group than the placebo group after adjustment for baseline BDI-II score and minimisation and stratification variables [difference -1.83 points, 95% confidence interval (CI) -3.92 to 0.27 points; p = 0.087]. This was smaller than the minimum clinically important difference and the CI included the null. The difference became smaller at subsequent time points (24 weeks: -0.85 points, 95% CI -3.12 to 1.43 points; 12 months: 0.17 points, 95% CI -2.13 to 2.46 points). More participants in the mirtazapine group withdrew from the trial medication, citing mild AEs (46 vs. 9 participants).
Conclusions:
This study did not find convincing evidence of a clinically important benefit for mirtazapine in addition to a SSRI or a SNRI antidepressant over placebo in primary care patients with TRD. There was no evidence that the addition of mirtazapine was a cost-effective use of NHS resources. GPs and patients were concerned about adding an additional antidepressant.
Limitations:
Voluntary unblinding for participants after the primary outcome at 12 weeks made interpretation of longer-term outcomes more difficult.
Future Work:
Treatment-resistant depression remains an area of important, unmet need, with limited evidence of effective treatments. Promising interventions include augmentation with atypical antipsychotics and treatment using transcranial magnetic stimulation.
Trial Registration:
Current Controlled Trials ISRCTN06653773; EudraCT number 2012-000090-23.
Funding:
This project was funded by the NIHR Health Technology Assessment programme and will be published in full in Health Technology Assessment; Vol. 22, No. 63. See the NIHR Journals Library website for further project information.

Related Concept Videos
 01:28
Antidepressant Drugs: Tricyclics, SSRIs, and SNRIs
 02:56
Treatment Resistant Cancers
 01:05
Long-term Depression
 01:03
Long-term Depression
Calcium Ion Concentration Mechanism
If over...
 03:12
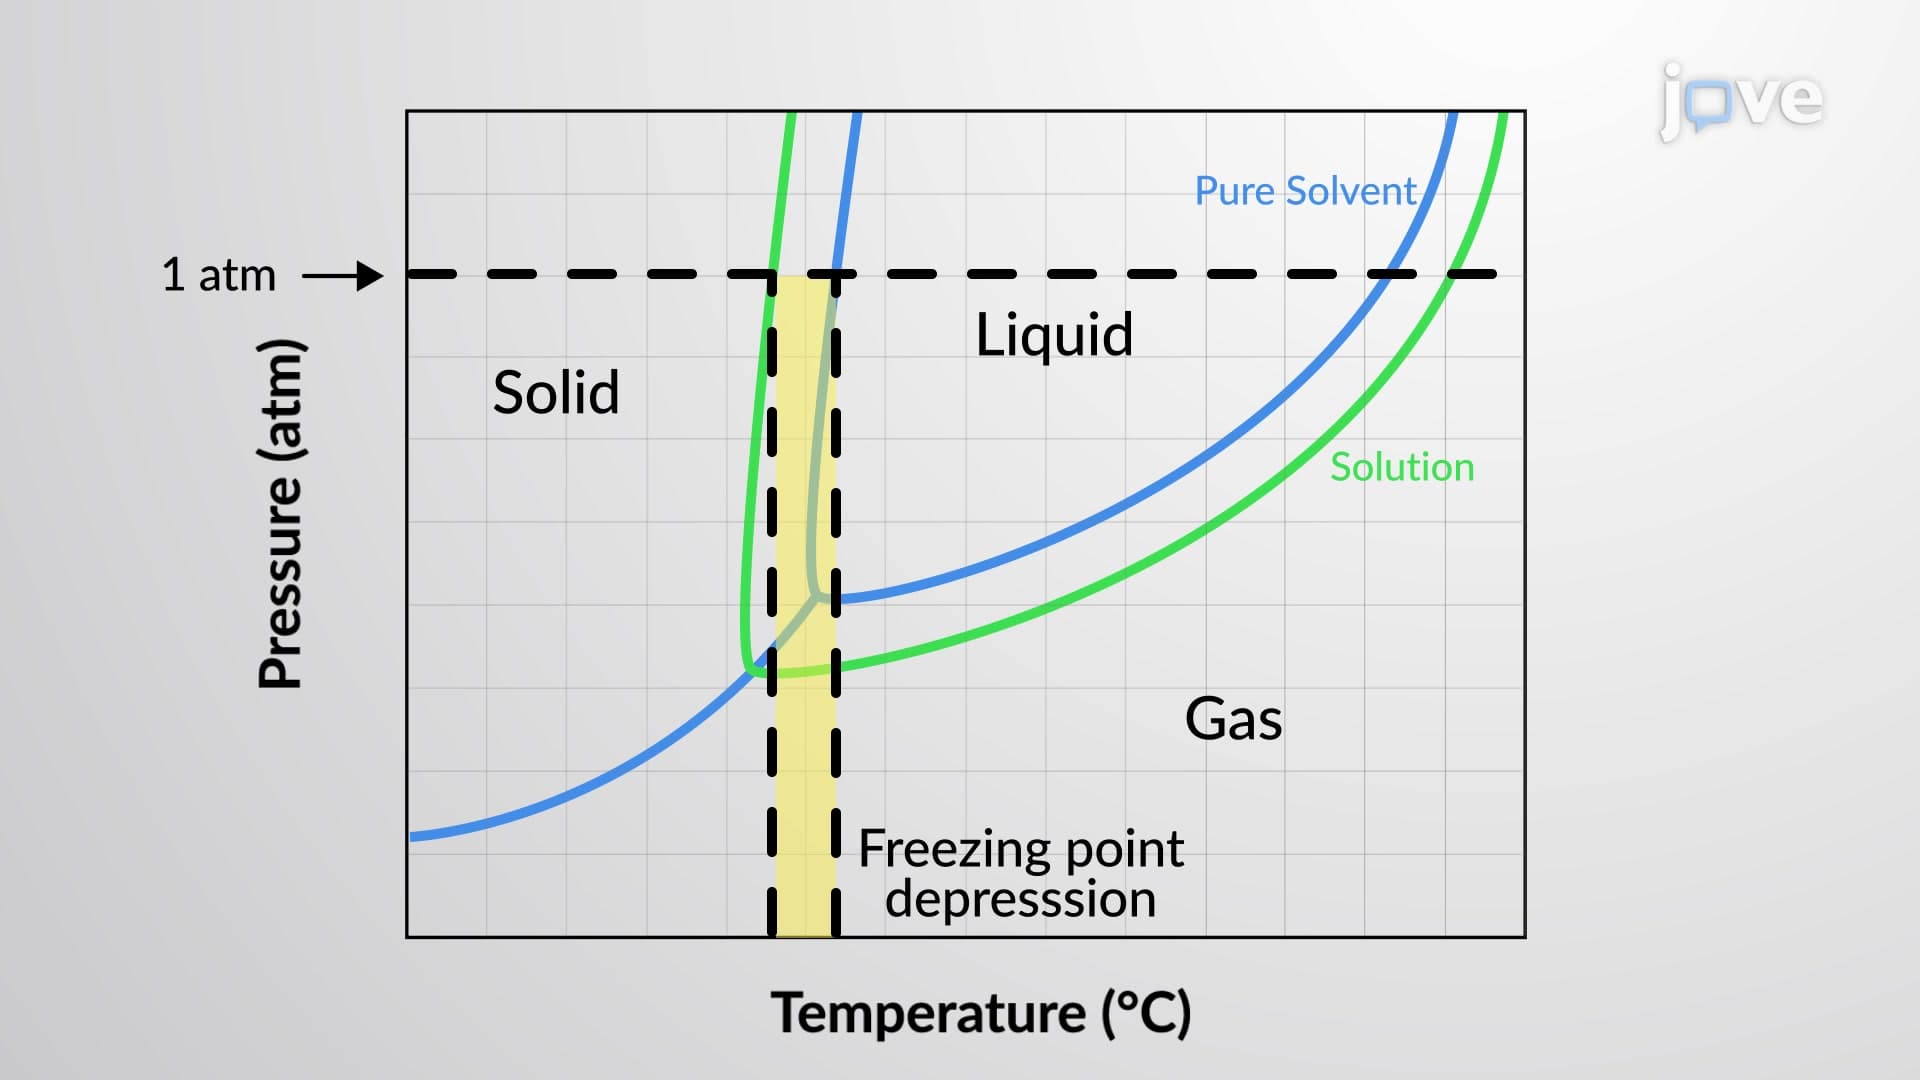
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:28
Depressants
Alcohol is a common depressant that can induce a sense of relaxation and reduced inhibition at low doses. Contrary to its occasional...