Related Experiment Video
Updated: Feb 2, 2026
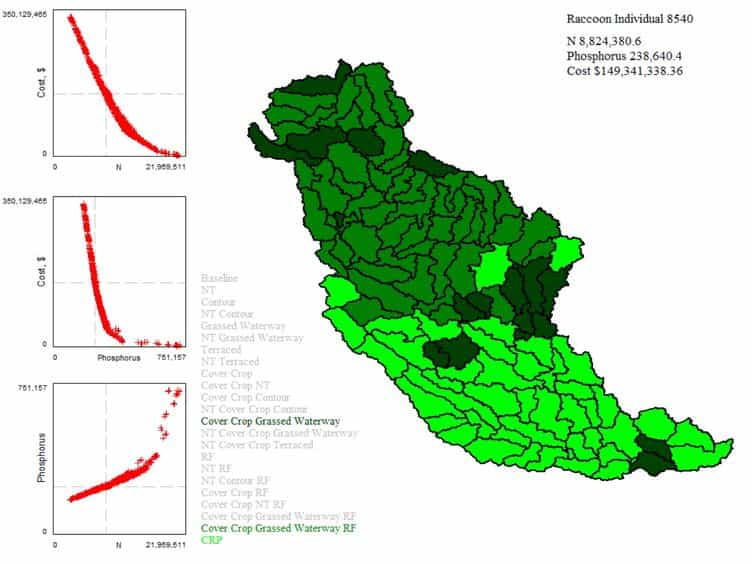

Spatial Multiobjective Optimization of Agricultural Conservation Practices using a SWAT Model and an Evolutionary Algorithm
Published on: December 9, 2012
Practical utility of general practice data capture and spatial analysis for understanding COPD and asthma
T Niyonsenga1,2, N T Coffee3,4, P Del Fante5,4
1Centre for Research and Action in Public Health, Health Research Institute, Faculty of Health, University of Canberra, Canberra, Australian Capital Territory, Australia. theo.niyonsenga@canberra.edu.au.

Background:
General practice-based (GP) healthcare data have promise, when systematically collected, to support estimating local rates of chronic obstructive pulmonary disease (COPD) and asthma, variations in burden of disease, risk factors and comorbid conditions, and disease management and quality of care. The use of GP information systems for health improvement has been limited, however, in the scope and quality of data. This study assessed the practical utility of de-identified clinical databases for estimating local rates of COPD and asthma. We compared COPD and asthma rates to national benchmarks, examined health related risk factors and co-morbidities as correlates of COPD and asthma, and assessed spatial patterns in prevalence estimates at the small-area level.
Methods:
Data were extracted from five GP databases in western Adelaide, South Australia, for active patients residing in the region between 2012 and 2014. Prevalence estimates were computed at the statistical area 1 (SA1) spatial unit level using the empirical Bayes estimation approach. Descriptive analyses included summary statistics, spatial indices and mapping of geographic patterns. Bivariate associations were assessed, and disease profiles investigated to ascertain multi-morbidities. Multilevel logistic regression models were fitted, accounting for individual covariates including the number of comorbid conditions to assess the influence of area-level socio-economic status (SES).
Results:
For 33,725 active patients, prevalence estimates were 3.4% for COPD and 10.3% for asthma, 0.8% higher and 0.5% lower for COPD and asthma, respectively, against 2014-15 National Health Survey (NHS) benchmarks. Age-specific comparisons showed discrepancies for COPD in the '64 years or less' and 'age 65 and up' age groups, and for asthma in the '15-25 years' and '75 years and up' age groups. Analyses confirmed associations with individual-level factors, co-morbid conditions, and area-level SES. Geographic aggregation was seen for COPD and asthma, with clustering around GP clinics and health care centres. Spatial patterns were inversely related to area-level SES.
Conclusion:
GP-based data capture and analysis has a clear potential to support research for improved patient outcomes for COPD and asthma via knowledge of geographic variability and its correlates, and how local prevalence estimates differ from NHS benchmarks for vulnerable age-groups.


Related Concept Videos
 01:16
Characteristics of Practical Op Amps
The ratio of differential gain to the common-mode gain is defined as the common-mode rejection ratio (CMRR). This ratio quantifies the ability of operational amplifiers (op-amps) to reject common-mode...
 01:30
Theoretical Foundations of Nursing Practice
Theories provide a perspective to assess patients' conditions and organize data and methods. They also assist in analyzing and interpreting information. They represent a...
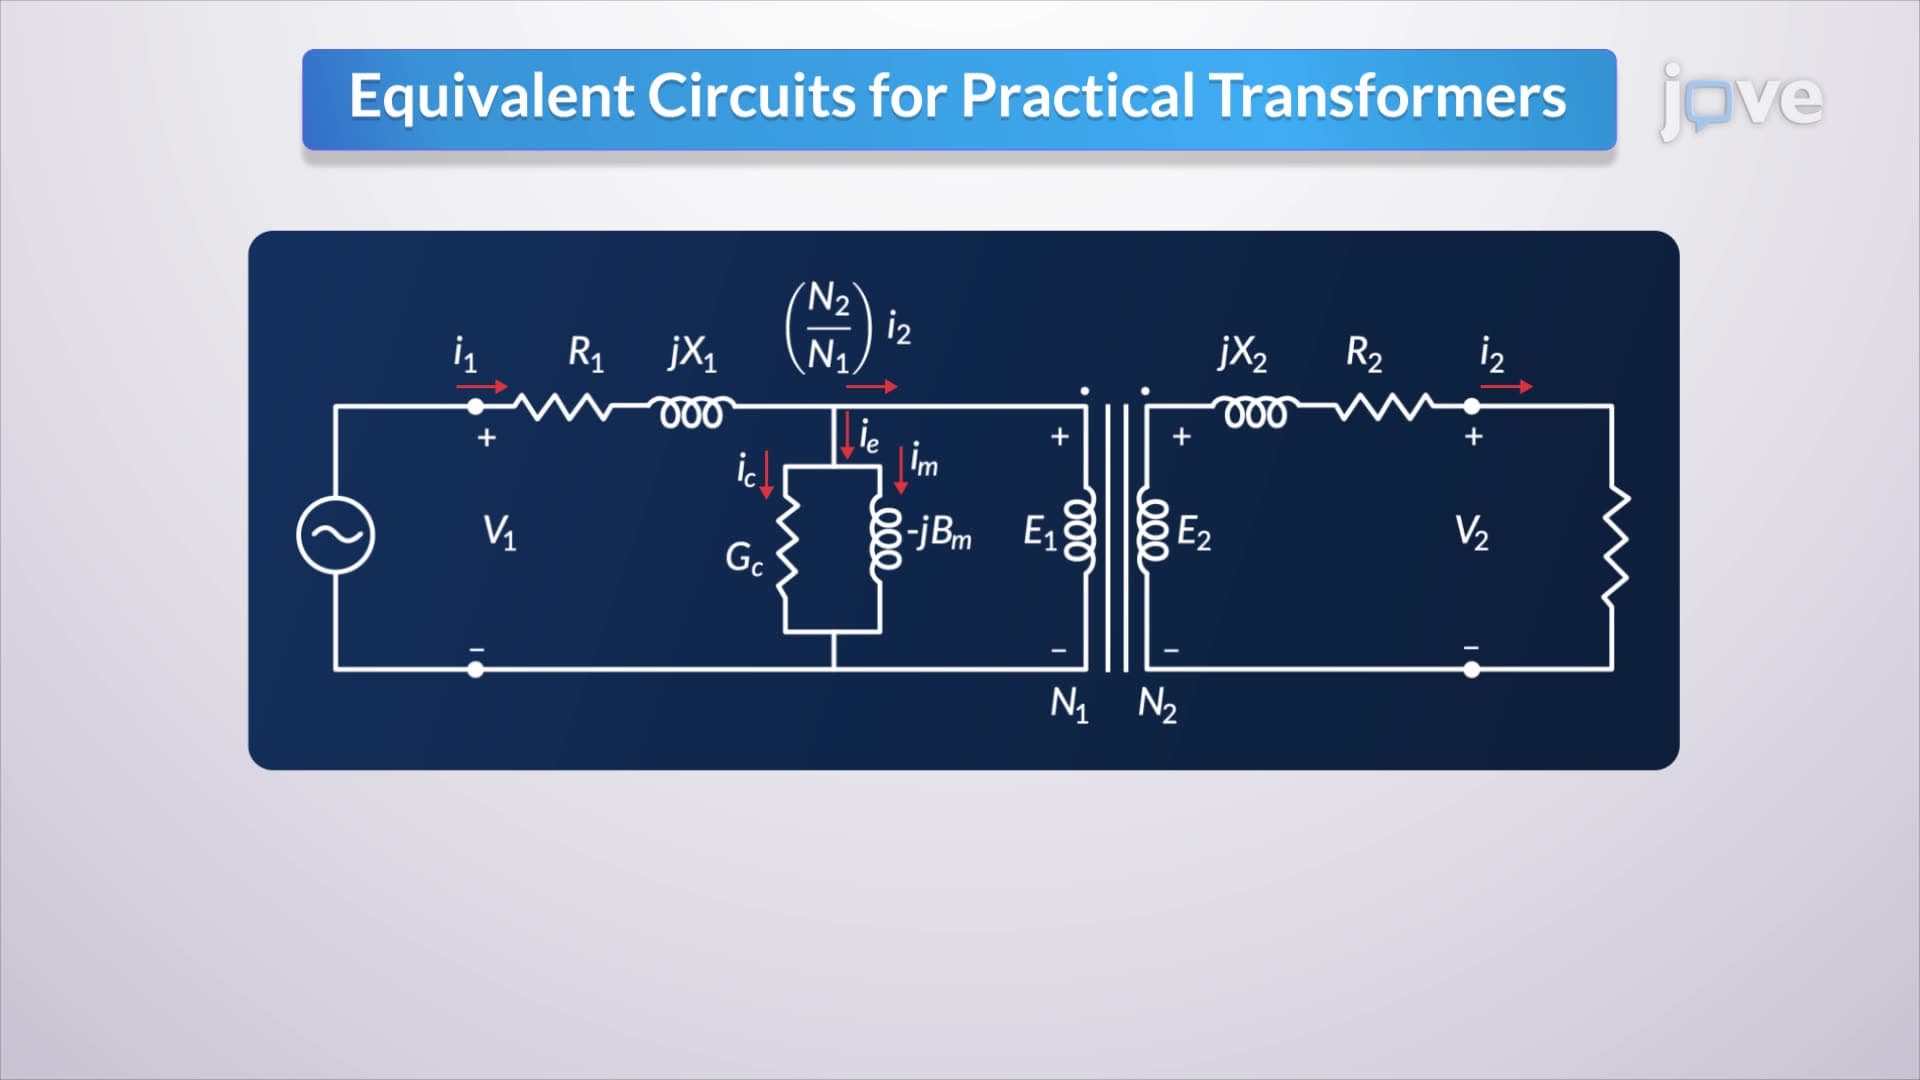 01:28
Equivalent Circuits for Practical Transformers
In a practical transformer, each winding exhibits resistance and leakage reactance. The...
 01:29
Asthma-I: Introduction
 01:28
Understanding the Self
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...