Related Experiment Video
Updated: Feb 2, 2026
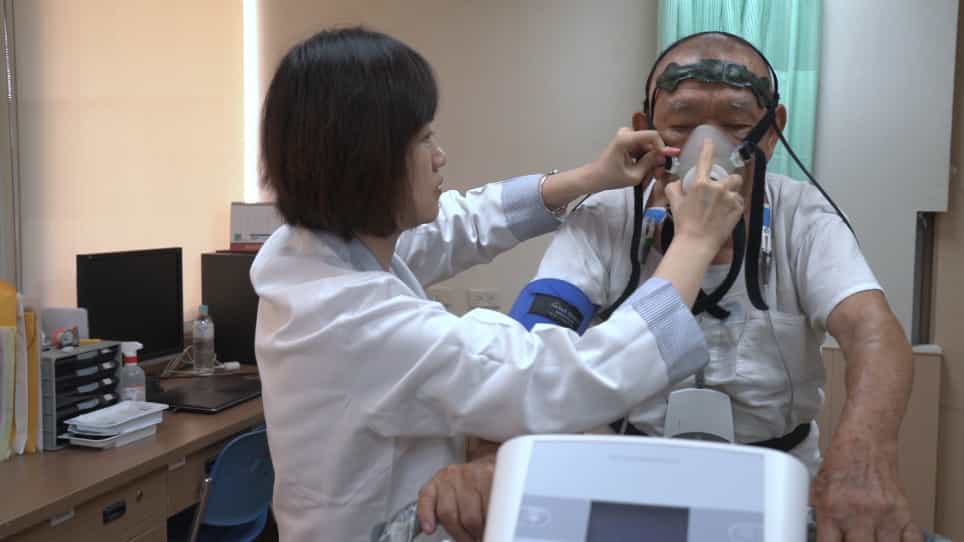

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Applying the Optimized CO Rebreathing Method for Measuring Blood Volumes and Hemoglobin Mass in Heart Failure
Christoph Ahlgrim1,2, Philipp Birkner3, Florian Seiler3
1Center for Medicine, Institute for Exercise and Occupational Medicine, Medical Center - University of Freiburg, Freiburg, Germany.

Insights
The optimized carbon monoxide (CO)-rebreathing method (oCORM) is safe for heart failure patients to measure blood and hemoglobin mass. A slight underestimation of about 1% in hemoglobin mass should be considered due to reduced ejection fraction.
Area of Science:
- Cardiology
- Exercise Physiology
- Medical Diagnostics
Background:
- Blood volume and hemoglobin mass are crucial for understanding heart failure pathophysiology, particularly anemia and volume overload.
- The optimized carbon monoxide (CO)-rebreathing method (oCORM) is established for determining these parameters in healthy individuals.
- Its applicability in heart failure patients with reduced ejection fraction (EF) is uncertain due to altered CO kinetics.
Purpose of the Study:
- To assess the applicability of oCORM in heart failure patients with severely reduced EF (<30%).
- To determine the systematic error in intravascular volume and hemoglobin mass (Hbmass) measurements using oCORM in this population.
- To evaluate the safety and side effects of oCORM in heart failure patients.
Main Methods:
- Performed oCORM in 21 heart failure patients (EF < 30%) and 25 controls.
- Analyzed CO kinetics in capillary blood 3-15 minutes post-rebreathing.
- Utilized Monte Carlo simulations to quantify systematic error in Hbmass determination.
Main Results:
- Significantly different CO kinetics were observed between heart failure patients and controls.
- COHb levels reached 6.0 ± 1.0% at 3 minutes in both groups without adverse effects.
- Monte Carlo simulations estimated a systematic error of -0.88% for Hbmass in reduced EF patients.
Conclusions:
- Severely reduced EF impairs CO vascular mixing.
- oCORM can be safely used in heart failure patients with reduced EF.
- A systematic underestimation of approximately 1% for Hbmass should be considered, but is clinically negligible.
Abstract:
Introduction: Determination of blood volume, red cell volume, and plasma volume contributes to the understanding of the pathophysiology in heart failure, especially concerning anemia and volume load. The optimized carbon monoxide (CO)-rebreathing method (oCORM) is used to determine these parameters and hemoglobin mass (Hbmass) in exercise physiology. The applicability of oCORM to determine the intravascular volumes and Hbmass in heart failure patients is currently undetermined because assumptions concerning CO kinetics with oCORM rely on healthy subjects with a normal ejection fraction. Therefore, the aim of the present study is to determine the applicability and the systematic error of oCORM arising from a reduced EF when oCORM is used for measurement of intravascular volumes and Hbmass in heart failure patients. Methods: oCORM was performed in 21 patients with heart failure and a reduced ejection fraction (EF) of < 30% (EFsev) and 25 controls (CONT). CO kinetics in capillary blood was studied 3-15 min after commencement of CO rebreathing. Differences in CO kinetics between the groups were assessed using a generalized linear model. The systematic error for determination of Hbmass with oCORM arising from differences in CO kinetics was assessed using the Monte Carlo method. Results: The CO kinetics was significantly different between EFsev and CONT. In both groups, exposure to CO led to a COHb increase to 6.0 ± 1.0% 3 min after CO rebreathing. There were no CO related side effects or any clinical symptoms. Monte Carlo simulation quantifies the systematic error for determination of Hbmass arising from an impaired ejection fraction to be -0.88%. Conclusion: Our results indicate an impaired vascular mixing of CO when EF is severely reduced. When Hbmass is determined using the original oCORM protocol in heart failure patients with a reduced EF, the systematic underestimation of about 1% should be considered. However, the error arising from this impaired vascular mixing appears small and clinically negligible. Furthermore, application of oCORM was safe and not related to any side effects resulting from CO exposure. In conclusion, oCORM can be used for assessing intravascular volumes and Hbmass in patients with a reduced EF.
More Related Videos
 03:47
Author Spotlight: Workflow for Integrating POCUS Data into EHR for Managing Heart Failure Patients
Published on: July 12, 2024
 05:16
Cutoff Value of Phase Angle by Bioelectrical Impedance Analysis at Admission as a Prognostic Factor in Patients with Acute Heart Failure
Published on: June 10, 2025
Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:27
Heart Failure I: Introduction
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Heart Failure Drugs: Diuretics
 01:30
Heart Failure V: Medical Management