Related Experiment Video
Updated: Feb 1, 2026


Functional Neuroimaging Using Ultrasonic Blood-brain Barrier Disruption and Manganese-enhanced MRI
Published on: July 12, 2012
Manganese-Enhanced T1 Mapping in the Myocardium of Normal and Infarcted Hearts
N B Spath1, D M L Lilburn2, G A Gray1
1British Heart Foundation Centre of Cardiovascular Science, University of Edinburgh, Edinburgh, UK.

Background:
Manganese-enhanced MRI (MEMRI) has the potential to identify viable myocardium and quantify calcium influx and handling. Two distinct manganese contrast media have been developed for clinical application, mangafodipir and EVP1001-1, employing different strategies to mitigate against adverse effects resulting from calcium-channel agonism. Mangafodipir delivers manganese ions as a chelate, and EVP1001-1 coadministers calcium gluconate. Using myocardial T1 mapping, we aimed to explore chelated and nonchelated manganese contrast agents, their mechanism of myocardial uptake, and their application to infarcted hearts.
Methods:
T1 mapping was performed in healthy adult male Sprague-Dawley rats using a 7T MRI scanner before and after nonchelated (EVP1001-1 or MnCl2 (22 micromol/kg)) or chelated (mangafodipir (22-44 micromol/kg)) manganese-based contrast media in the presence of calcium channel blockade (diltiazem (100-200 micromol/kg/min)) or sodium chloride (0.9%). A second cohort of rats underwent surgery to induce anterior myocardial infarction by permanent coronary artery ligation or sham surgery. Infarcted rats were imaged with standard gadolinium delayed enhancement MRI (DEMRI) with inversion recovery techniques (DEMRI inversion recovery) as well as DEMRI T1 mapping. A subsequent MEMRI scan was performed 48 h later using either nonchelated or chelated manganese and T1 mapping. Finally, animals were culled at 12 weeks, and infarct size was quantified histologically with Masson's trichrome (MTC).
Results:
Both manganese agents induced concentration-dependent shortening of myocardial T1 values. This was greatest with nonchelated manganese, and could be inhibited by 30-43% with calcium-channel blockade. Manganese imaging successfully delineated the area of myocardial infarction. Indeed, irrespective of the manganese agent, there was good agreement between infarct size on MEMRI T1 mapping and histology (bias 1.4%, 95% CI -14.8 to 17.1 P>0.05). In contrast, DEMRI inversion recovery overestimated infarct size (bias 11.4%, 95% CI -9.1 to 31.8 P=0.002), as did DEMRI T1 mapping (bias 8.2%, 95% CI -10.7 to 27.2 P=0.008). Increased manganese uptake was also observed in the remote myocardium, with remote myocardial ∆T1 inversely correlating with left ventricular ejection fraction after myocardial infarction (r=-0.61, P=0.022).
Conclusions:
MEMRI causes concentration and calcium channel-dependent myocardial T1 shortening. MEMRI with T1 mapping provides an accurate assessment of infarct size and can also identify changes in calcium handling in the remote myocardium. This technique has potential applications for the assessment of myocardial viability, remodelling, and regeneration.

Related Concept Videos
 01:27
Anatomy of the Heart
 01:19
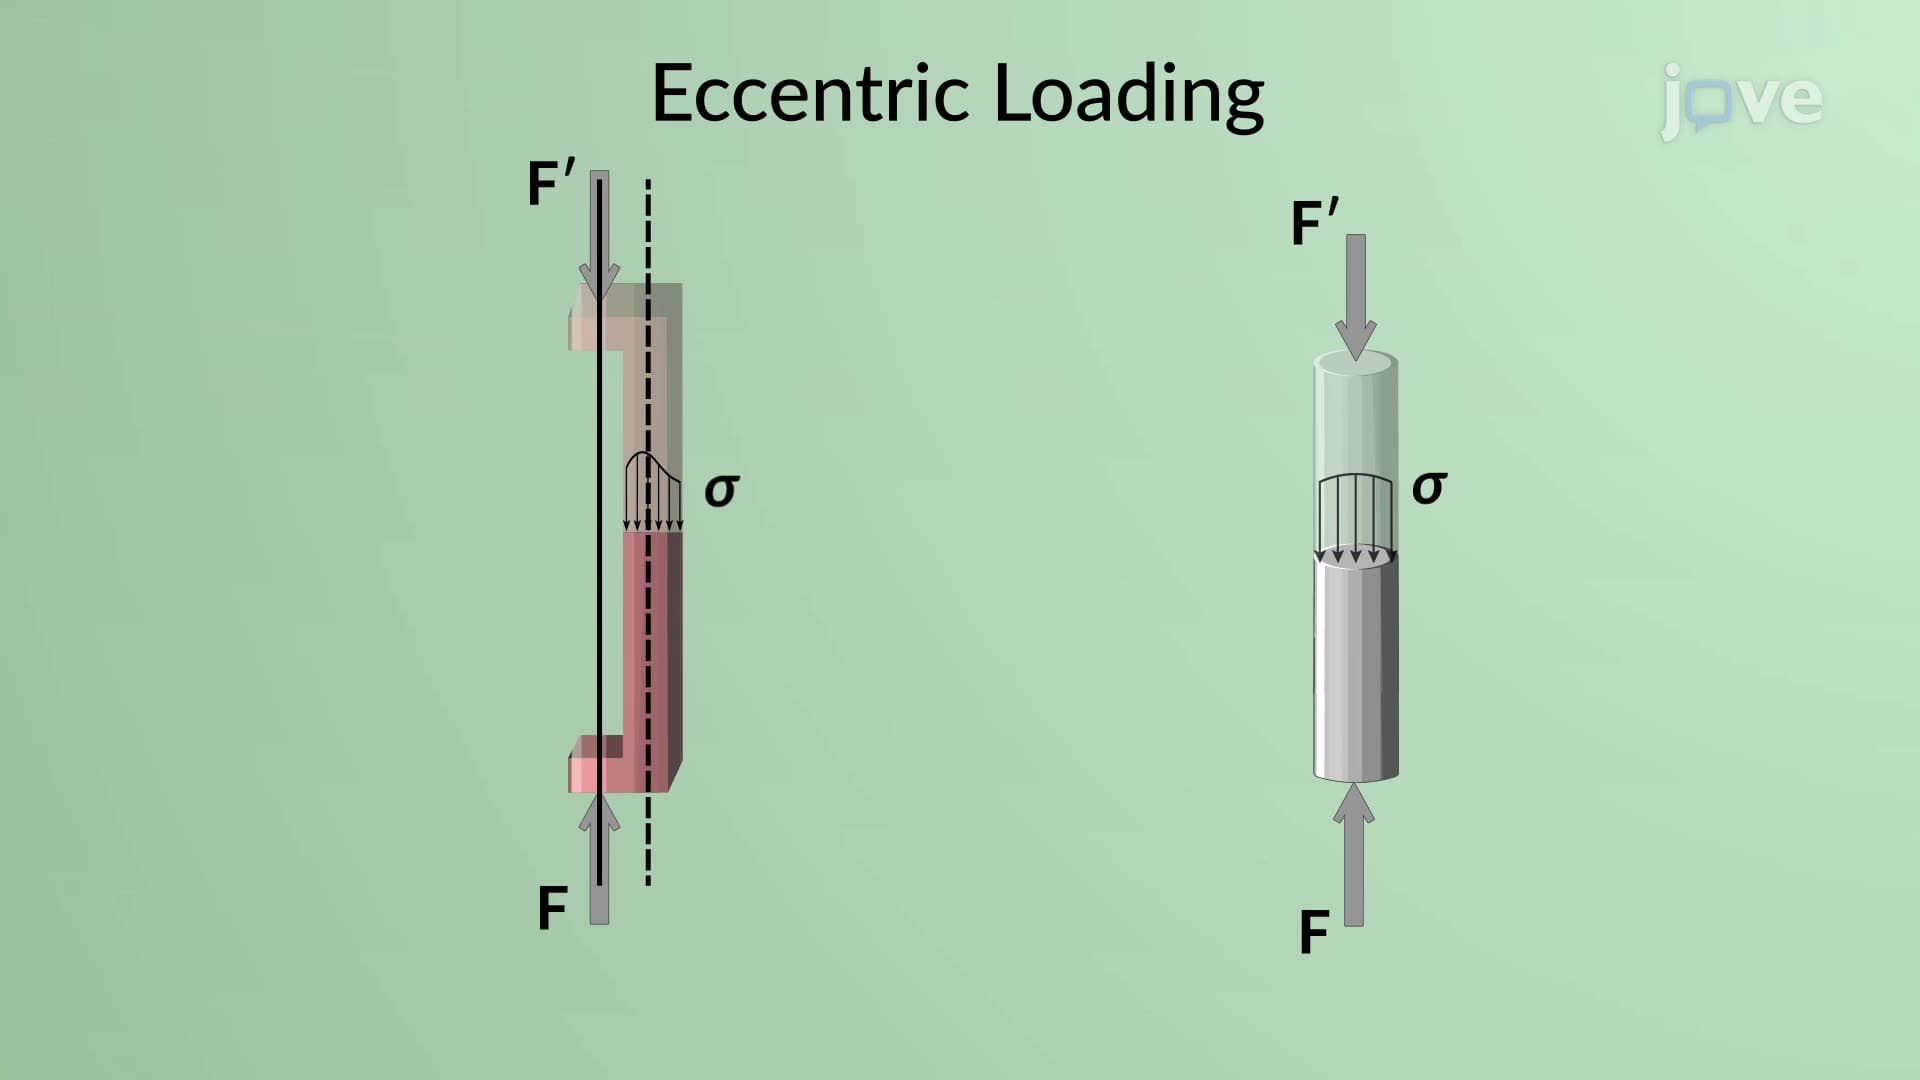
Normal Stress
When a rod is under axial loading, the internal forces and corresponding stress are normal to the plane of the section, so it is termed normal stress. It's important to...
 01:11
Normal Distribution
 01:14
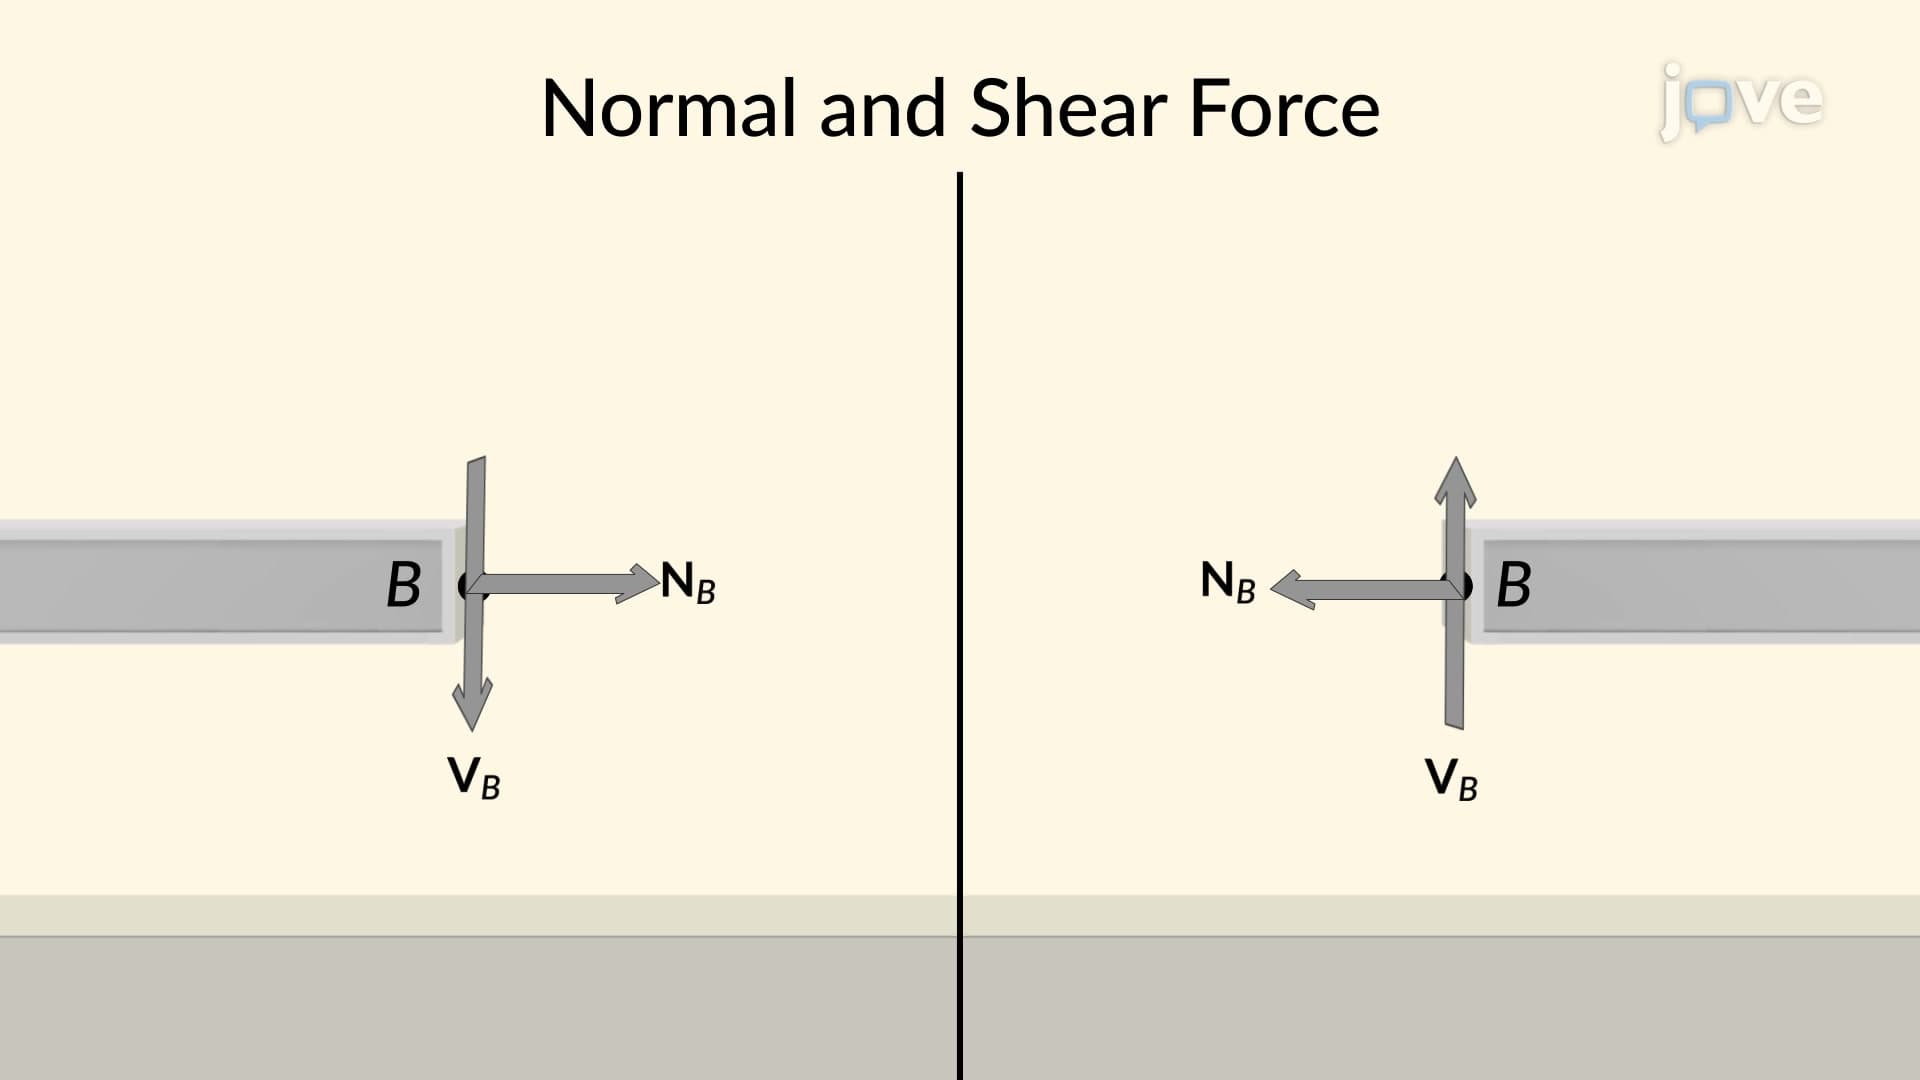
Normal and Shear Force
 01:22
Applications of Normal Distribution
The heights of 15 to 18-year-old males from Chile from 1984 to 1985 followed a normal distribution. The mean height is 172.36...
 01:29
Introduction to Normal Distributions