Related Experiment Video
Updated: Feb 1, 2026


Author Spotlight: Repetitive Transcranial Magnetic Stimulation Combined with Movement Observation in Cerebral Palsy
Published on: August 9, 2024
Children with cerebral palsy have larger Achilles tendon moment arms than typically developing children
C F Alexander1, S Reid1, K Stannage2
1School of Human Sciences, University of Western Australia, Perth, Australia.

Insights
Children with cerebral palsy (CP) have larger Achilles tendon moment arms (ATMA), impacting plantarflexion function. This finding is crucial for understanding gait mechanics and improving interventions for CP.
Area of Science:
- Biomechanics
- Orthopedics
- Pediatric Rehabilitation
Background:
- The effectiveness of plantarflexor muscles in generating plantarflexion moments is influenced by Achilles tendon moment arm (ATMA) geometry.
- Reduced plantarflexion function in children with cerebral palsy (CP) is often attributed to muscle impairments, with less focus on ATMA geometry.
- Accurate ATMA estimation is vital for reliable musculoskeletal modeling in gait analysis.
Purpose of the Study:
- To compare 3D in-vivo ATMA estimates across adults, children with CP, and typically developing (TD) children.
- To evaluate the accuracy of ATMA estimates derived from linearly scaled musculoskeletal models against in-vivo measurements.
- To investigate the potential role of ATMA geometry in the reduced plantarflexion function observed in children with CP.
Main Methods:
- Utilized MRI scans from 8 children with CP, 11 TD children, and 9 healthy adults.
- Estimated 3D in-vivo ATMA using a validated method.
- Generated linearly scaled ATMA estimates from a lower limb musculoskeletal model scaled to individual tibia length.
Main Results:
- Normalized in-vivo 3D ATMA was significantly larger in children with CP (17.2% ± 2.0 tibia length) compared to TD children (15.2% ± 1.2) and adults (12.5% ± 0.8).
- Linear scaling of musculoskeletal models significantly underestimated in-vivo ATMA estimates across all groups, with discrepancies up to 34.7%.
- These findings highlight significant differences in ATMA geometry between children with CP and their typically developing peers.
Conclusions:
- Children with CP exhibit larger normalized 3D ATMA compared to TD children.
- This larger ATMA may contribute to the reduced plantarflexor function observed in CP.
- The study suggests that ATMA geometry should be considered in understanding CP-related gait impairments and in planning surgical interventions.
Abstract:
The effectiveness of the plantarflexor muscle group to generate desired plantarflexion moments is modulated by the geometry of the Achilles tendon moment arm (ATMA). Children with cerebral palsy (CP) frequently have reduced plantarflexion function, which is commonly attributed to impaired muscle structure and function, however little attention has been paid to the potential contribution of ATMA geometry. The use of musculoskeletal modelling for the simulation of gait and understanding of gait mechanics, rely on accuracy of ATMA estimates. This study aimed to compare 3D in-vivo estimates of ATMA of adults, children with CP and typically developing (TD) children, as well as compare 3D in-vivo estimates to linearly scaled musculoskeletal model estimates. MRI scans for eight children with CP, 11 TD children and nine healthy adults were used to estimate in-vivo 3D ATMA using a validated method. A lower limb musculoskeletal model was linearly scaled to individual tibia length to provide a scaled ATMA estimate. Normalised in-vivo 3D ATMA for children with CP was 17.2% ± 2.0 tibia length, which was significantly larger than for TD children (15.2% ± 1.2, p = 0.013) and adults (12.5% ± 0.8, p < 0.001). Scaled ATMA estimates from musculoskeletal models significantly underestimated in-vivo estimates for all groups, by up to 34.7%. The results of this study show children with CP have larger normalised 3D ATMA compared to their TD counterparts, which may have implications in understanding reduced plantarflexor function and the efficacy of surgical interventions whose aim is to modify the musculoskeletal geometry of this muscle group.
More Related Videos
 10:11
Portable Intermodal Preferential Looking IPL: Investigating Language Comprehension in Typically Developing Toddlers and Young Children with Autism
Published on: December 14, 2012
 08:26
Event-related Potentials During Target-response Tasks to Study Cognitive Processes of Upper Limb Use in Children with Unilateral Cerebral Palsy
Published on: January 11, 2016
Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:30
Typical Model Studies
 02:48
Bond Polarity, Dipole Moment, and Percent Ionic Character
 01:27
Ethnic Identity within a Larger Culture
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:14
Moment of Inertia
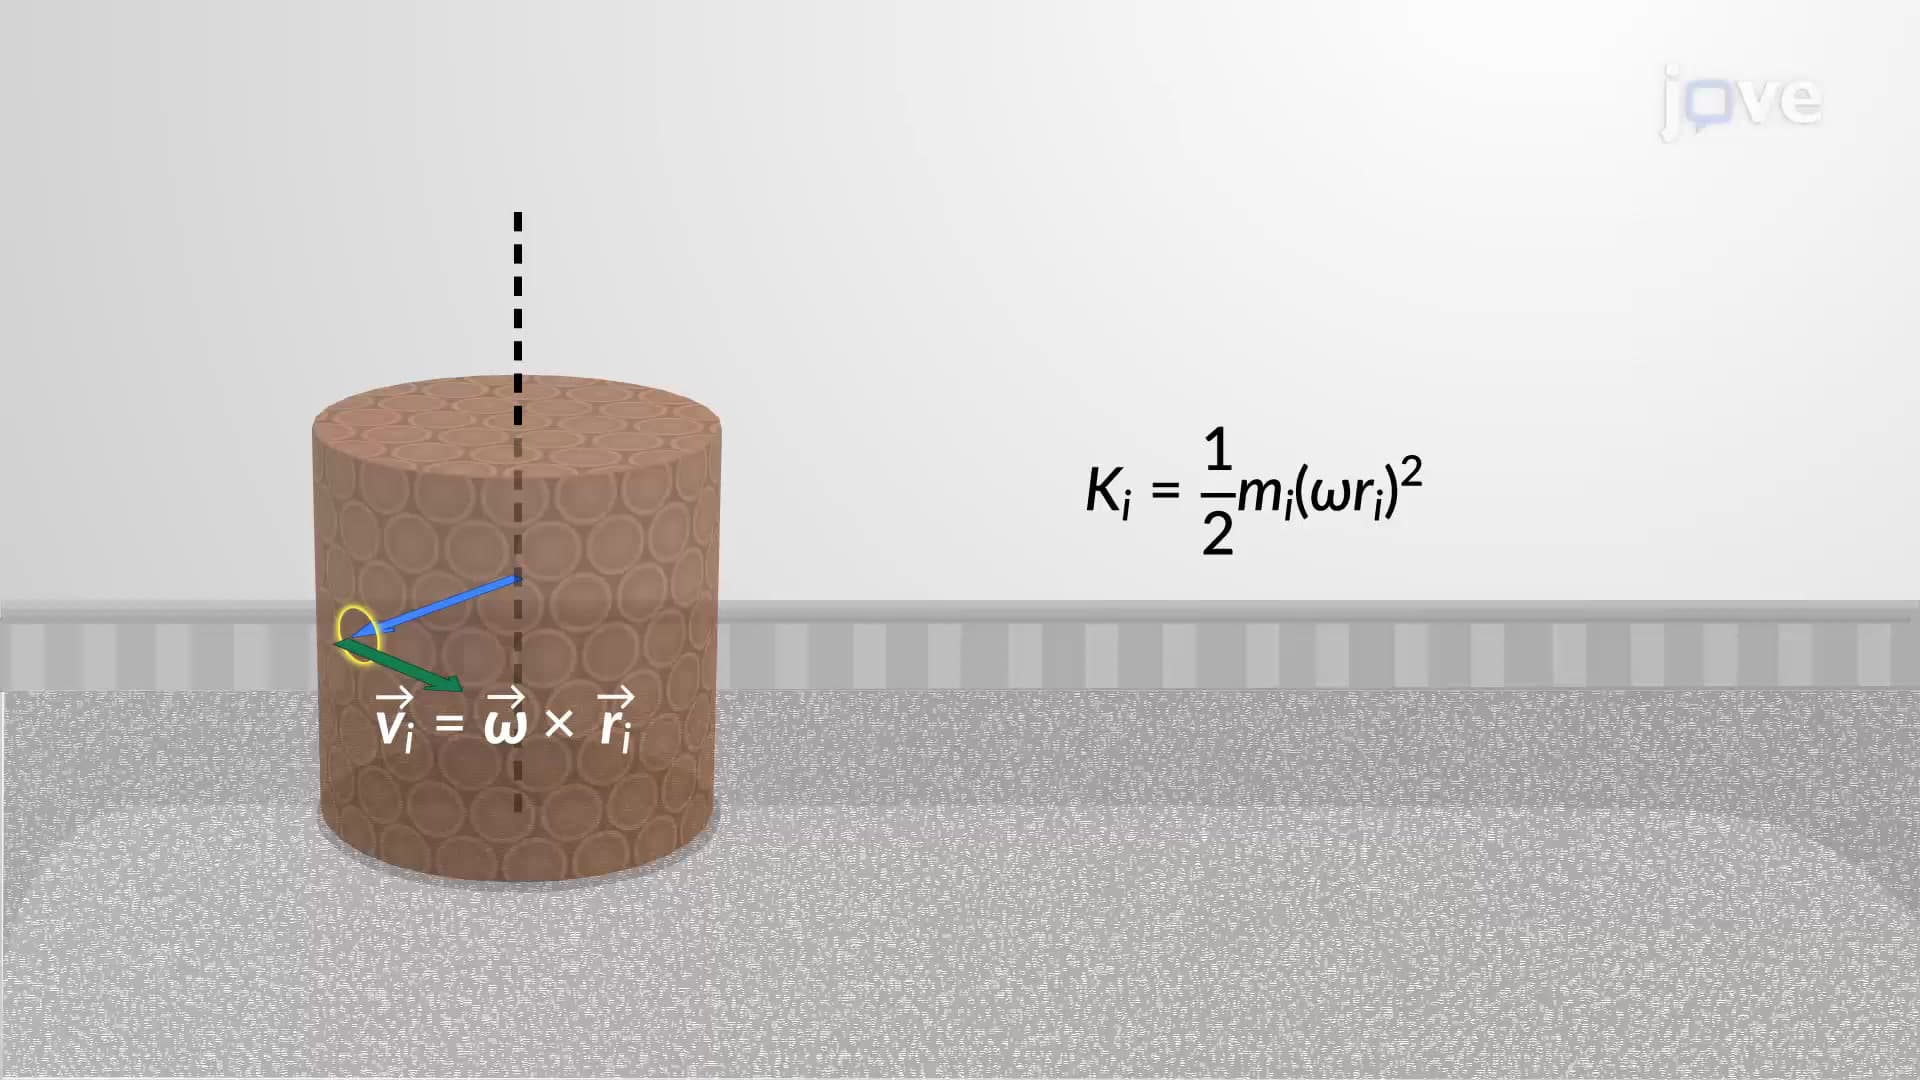
If a rigid body is rotating about an axis but is not in translational motion, its translational kinetic energy is zero. However, since each particle undergoes rotational motion, it possesses non-zero velocity and kinetic energy. Thus, the kinetic energy of the rigid body, which is the sum of the...