Related Experiment Video
Updated: Feb 1, 2026


Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Cutaneous Metastasis via Surgical Planes After Lumbar Spinal Reconstruction for Spinal Metastatic Disease
David G Deckey1, Daniel B C Reid2, Scott Mallozzi3
1Tufts University School of Medicine, Boston, Massachusetts, USA.

Background:
Cervical squamous cell carcinoma is the second most common cancer in women worldwide and the third most common cause of female cancer mortality. It frequently metastasizes to the osseous spine and has been rarely reported to cause cutaneous metastases at gynecologic surgical scars.
Case Description:
A 63-year-old woman with known metastatic cervical squamous cell carcinoma presented with a pathologic fracture of the L2 vertebra, unrelenting back pain, bilateral lower extremity weakness, and inability to ambulate. The patient elected to undergo an L2 corpectomy with intervertebral cage placement via the right-sided retroperitoneal approach followed by percutaneous L1-L4 pedicle screw instrumentation in the same operative setting. Her immediate postoperative course was uneventful. Eight weeks after surgery, both her flank and posterior incisions became painful and swollen. She underwent irrigation and debridement of the right flank incision due to elevated inflammatory markers and concern for surgical site infection. Multiple intraoperative cultures were obtained and were ultimately negative for bacterial or fungal growth. Several weeks later, the patient presented with worsening painful growths of her incisions. Excisional biopsy and debulking of the masses in the operating room revealed squamous cell carcinoma with areas of cystic change and tumor necrosis consistent with progression of the patient's metastatic cervical cancer.
Conclusions:
Cervical squamous cell carcinoma can metastasize regionally via surgical planes and manifest as cutaneous lesions. Local metastasis should be included in the differential in cases of postoperative wound complications.

Related Concept Videos
 01:26
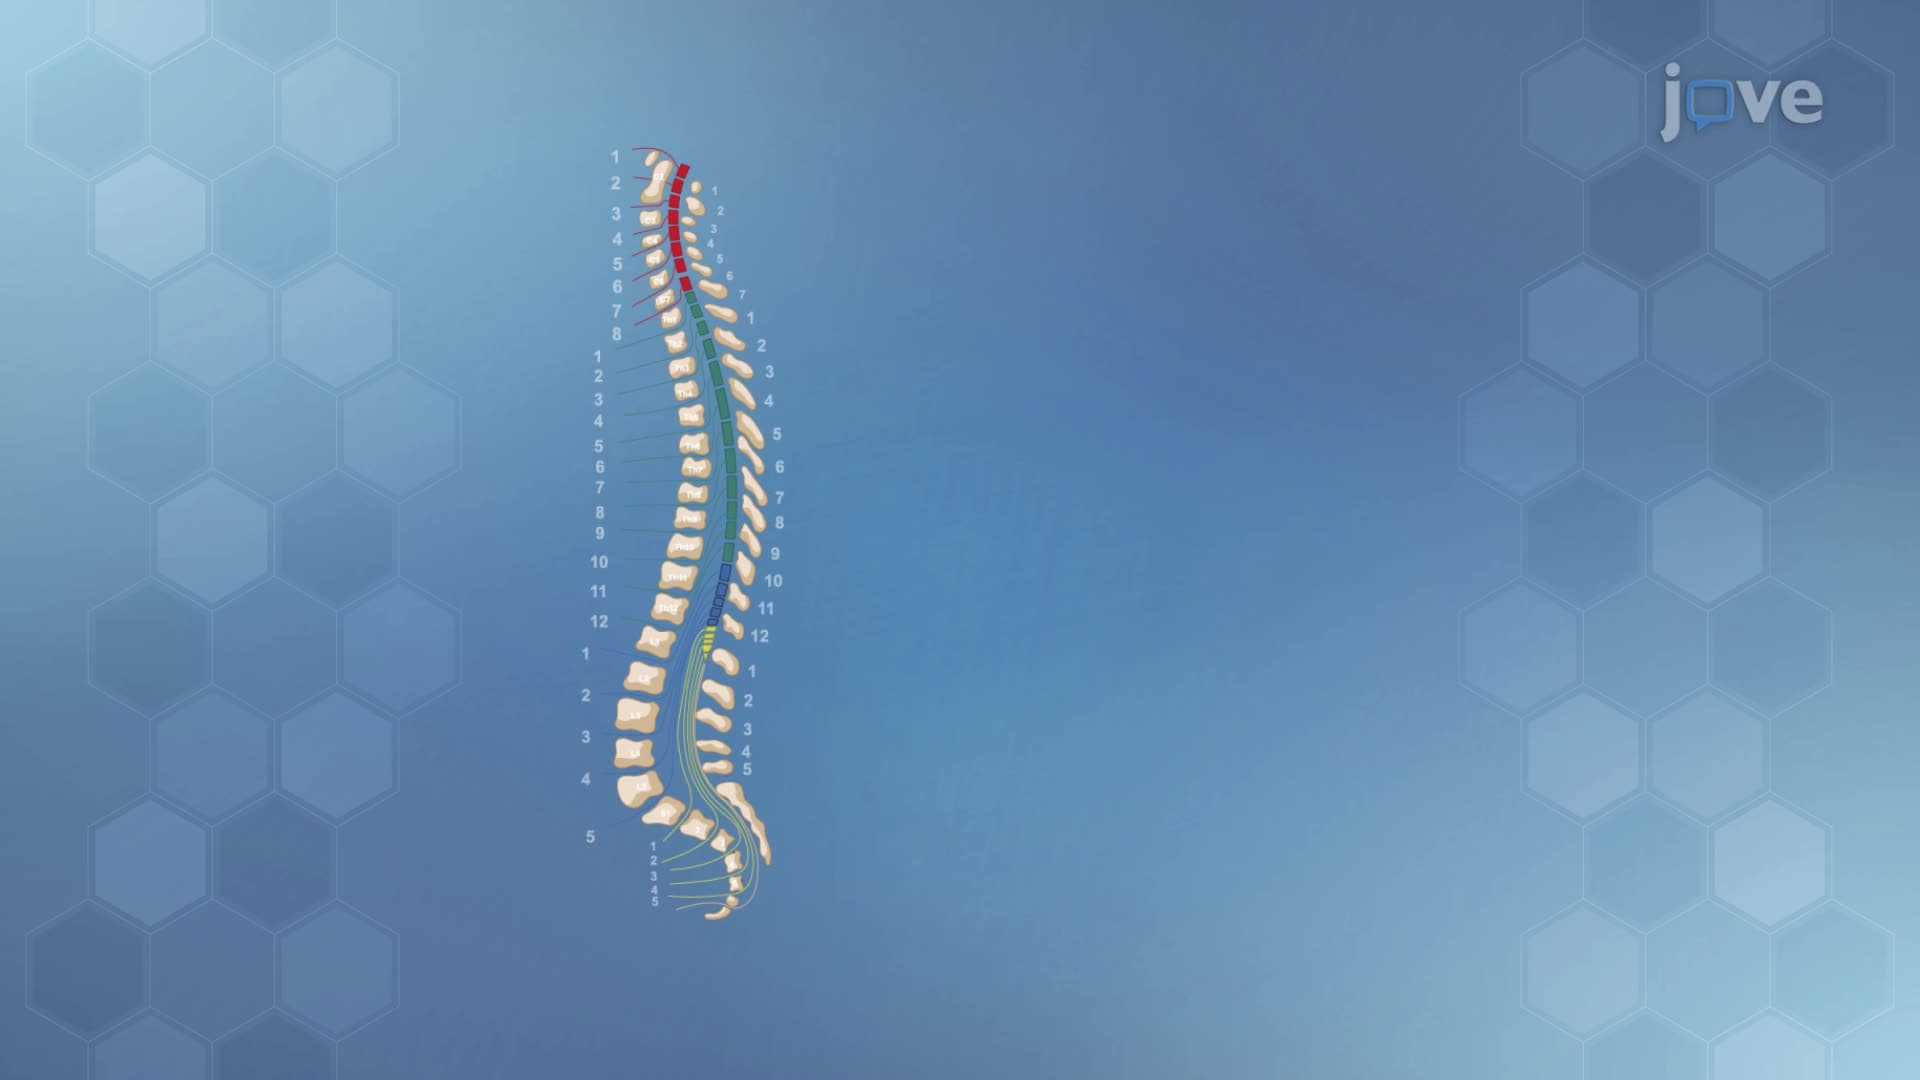
Spinal Cord
 01:54
The Spinal Cord
 01:10
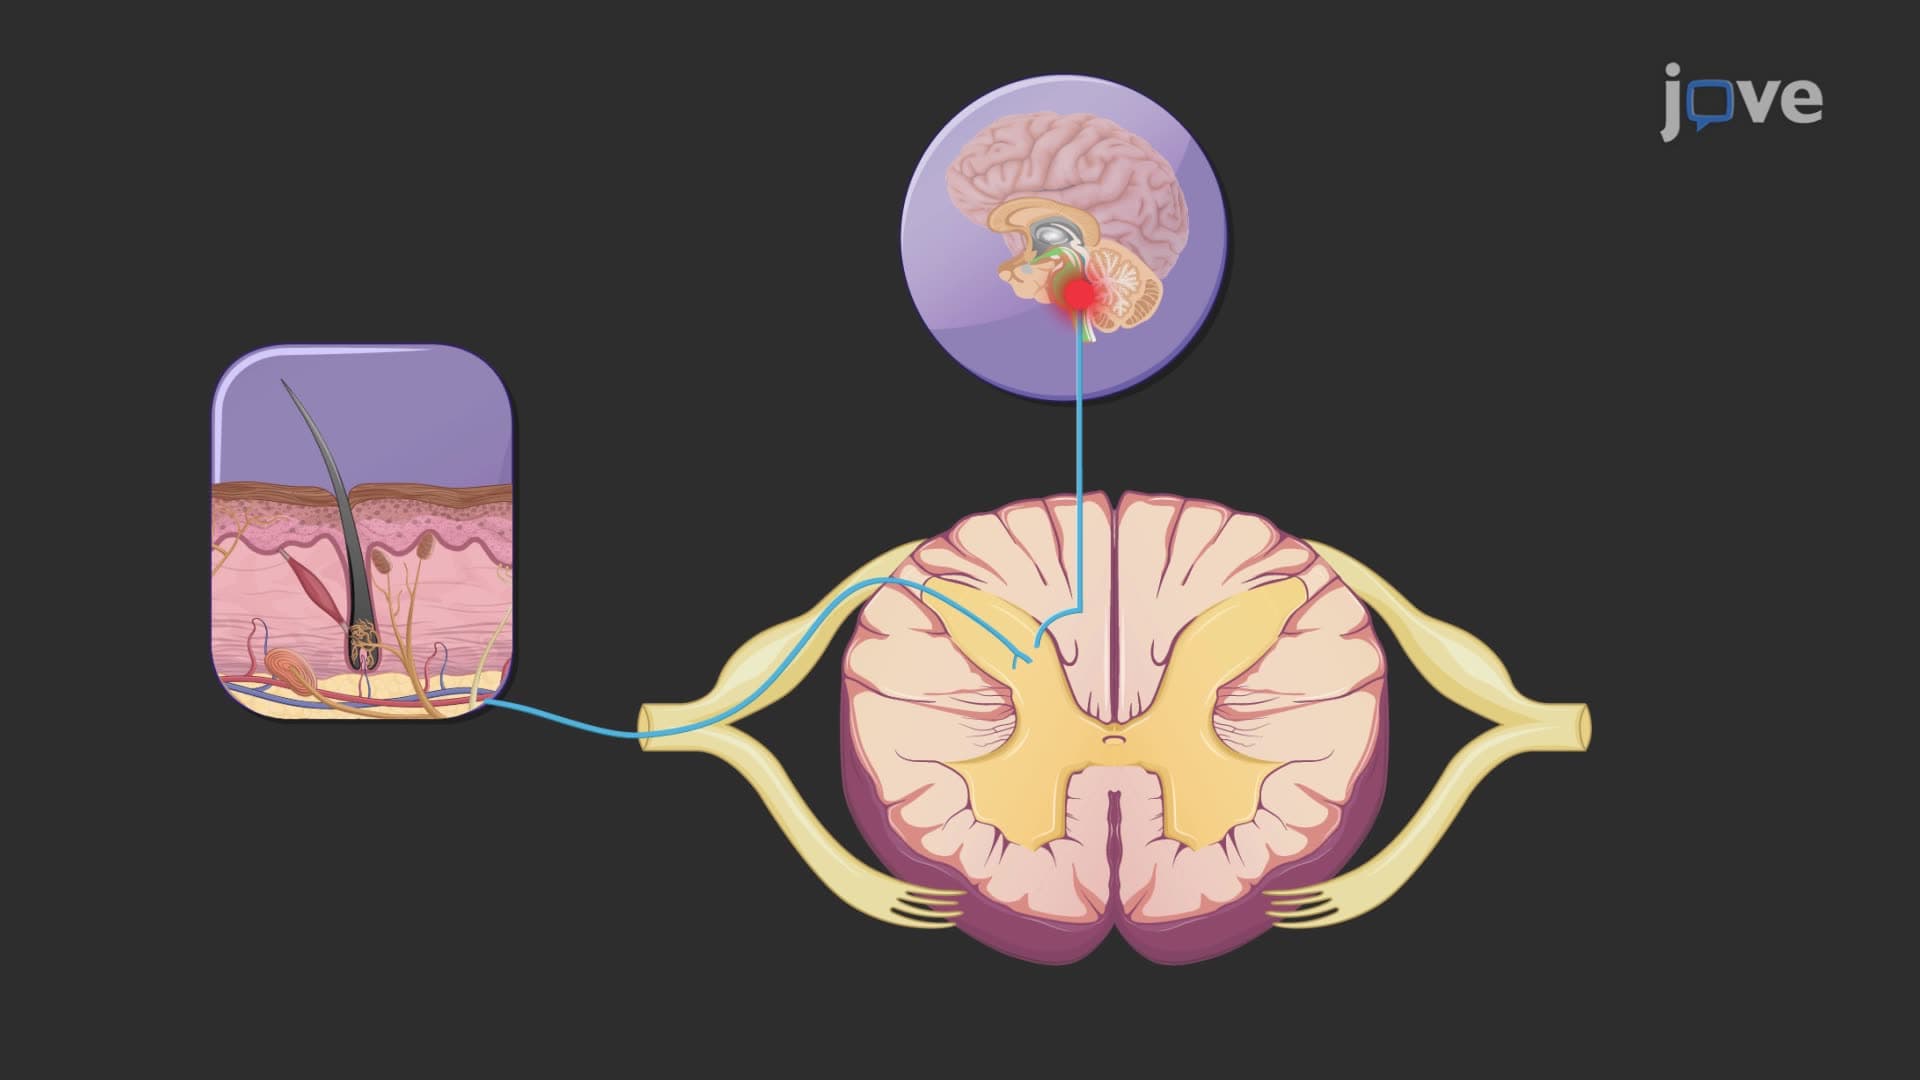
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:21
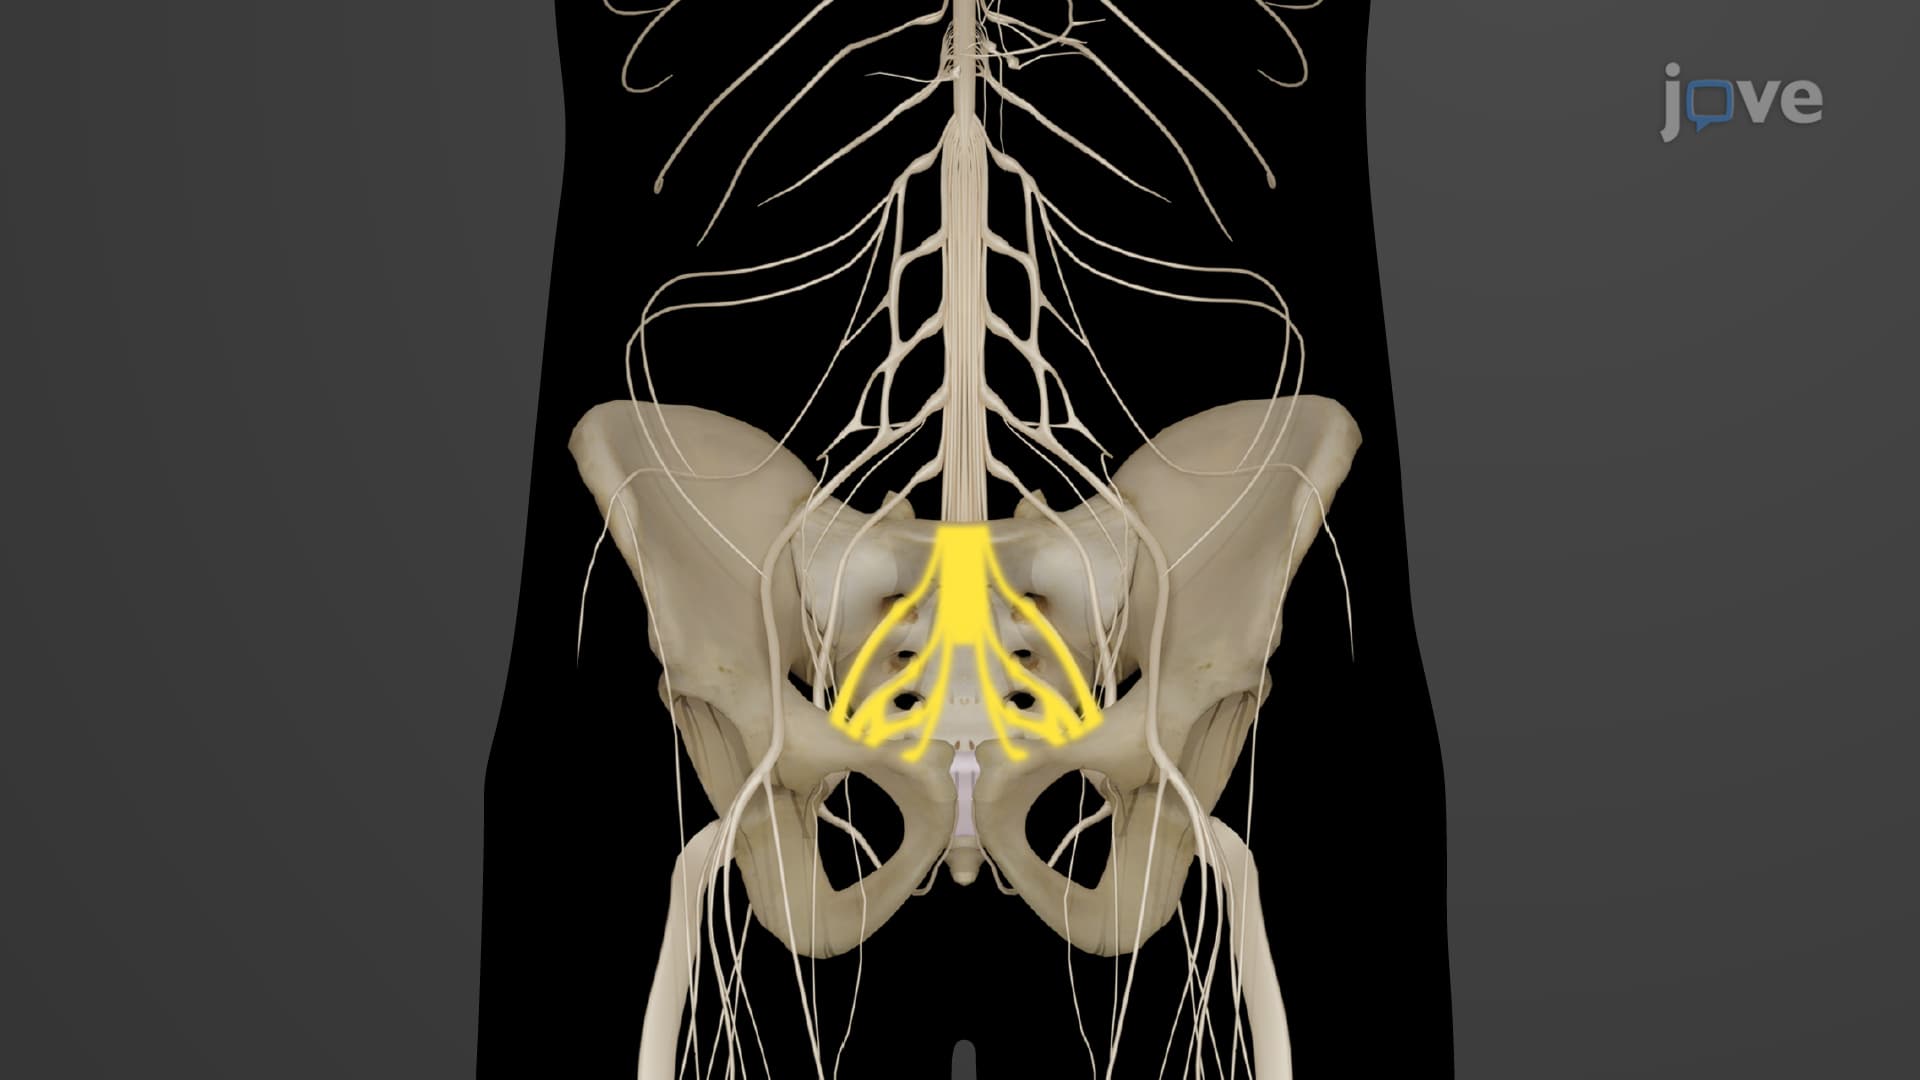
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:19
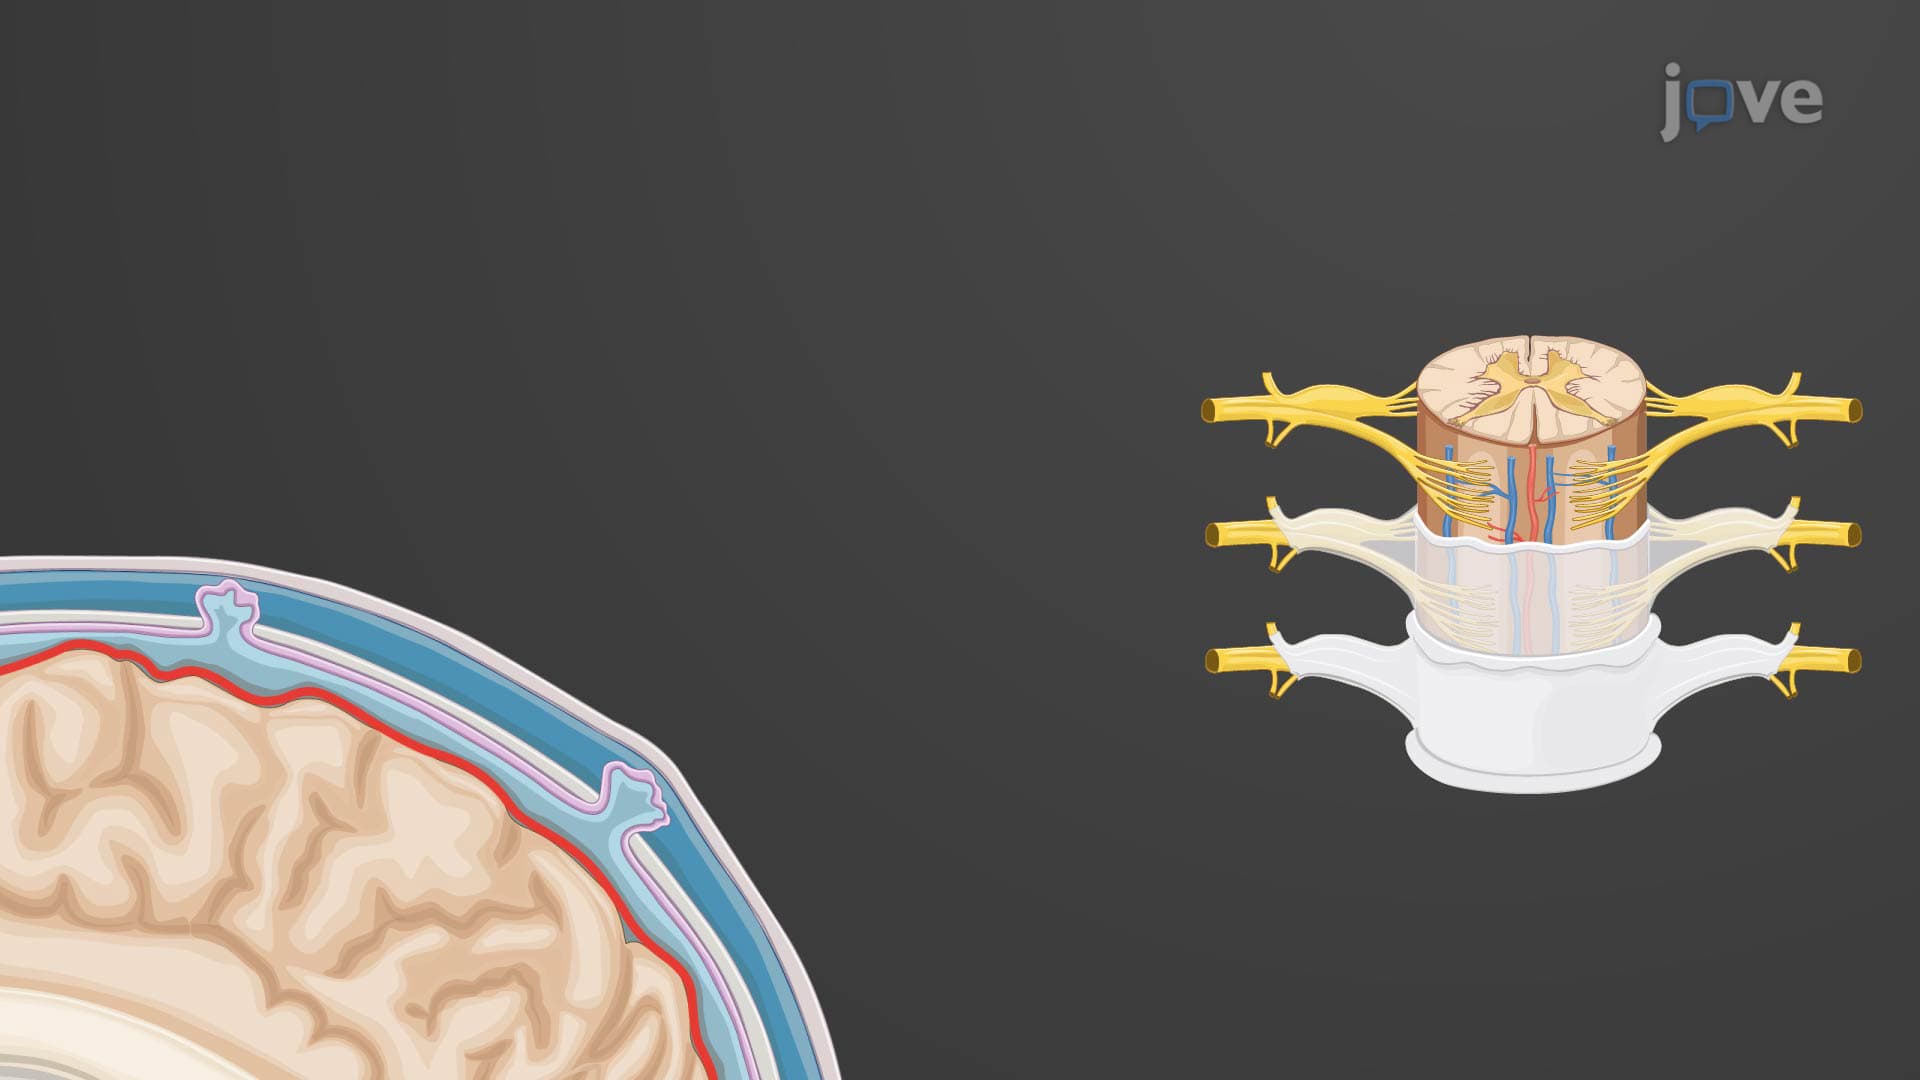
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:23
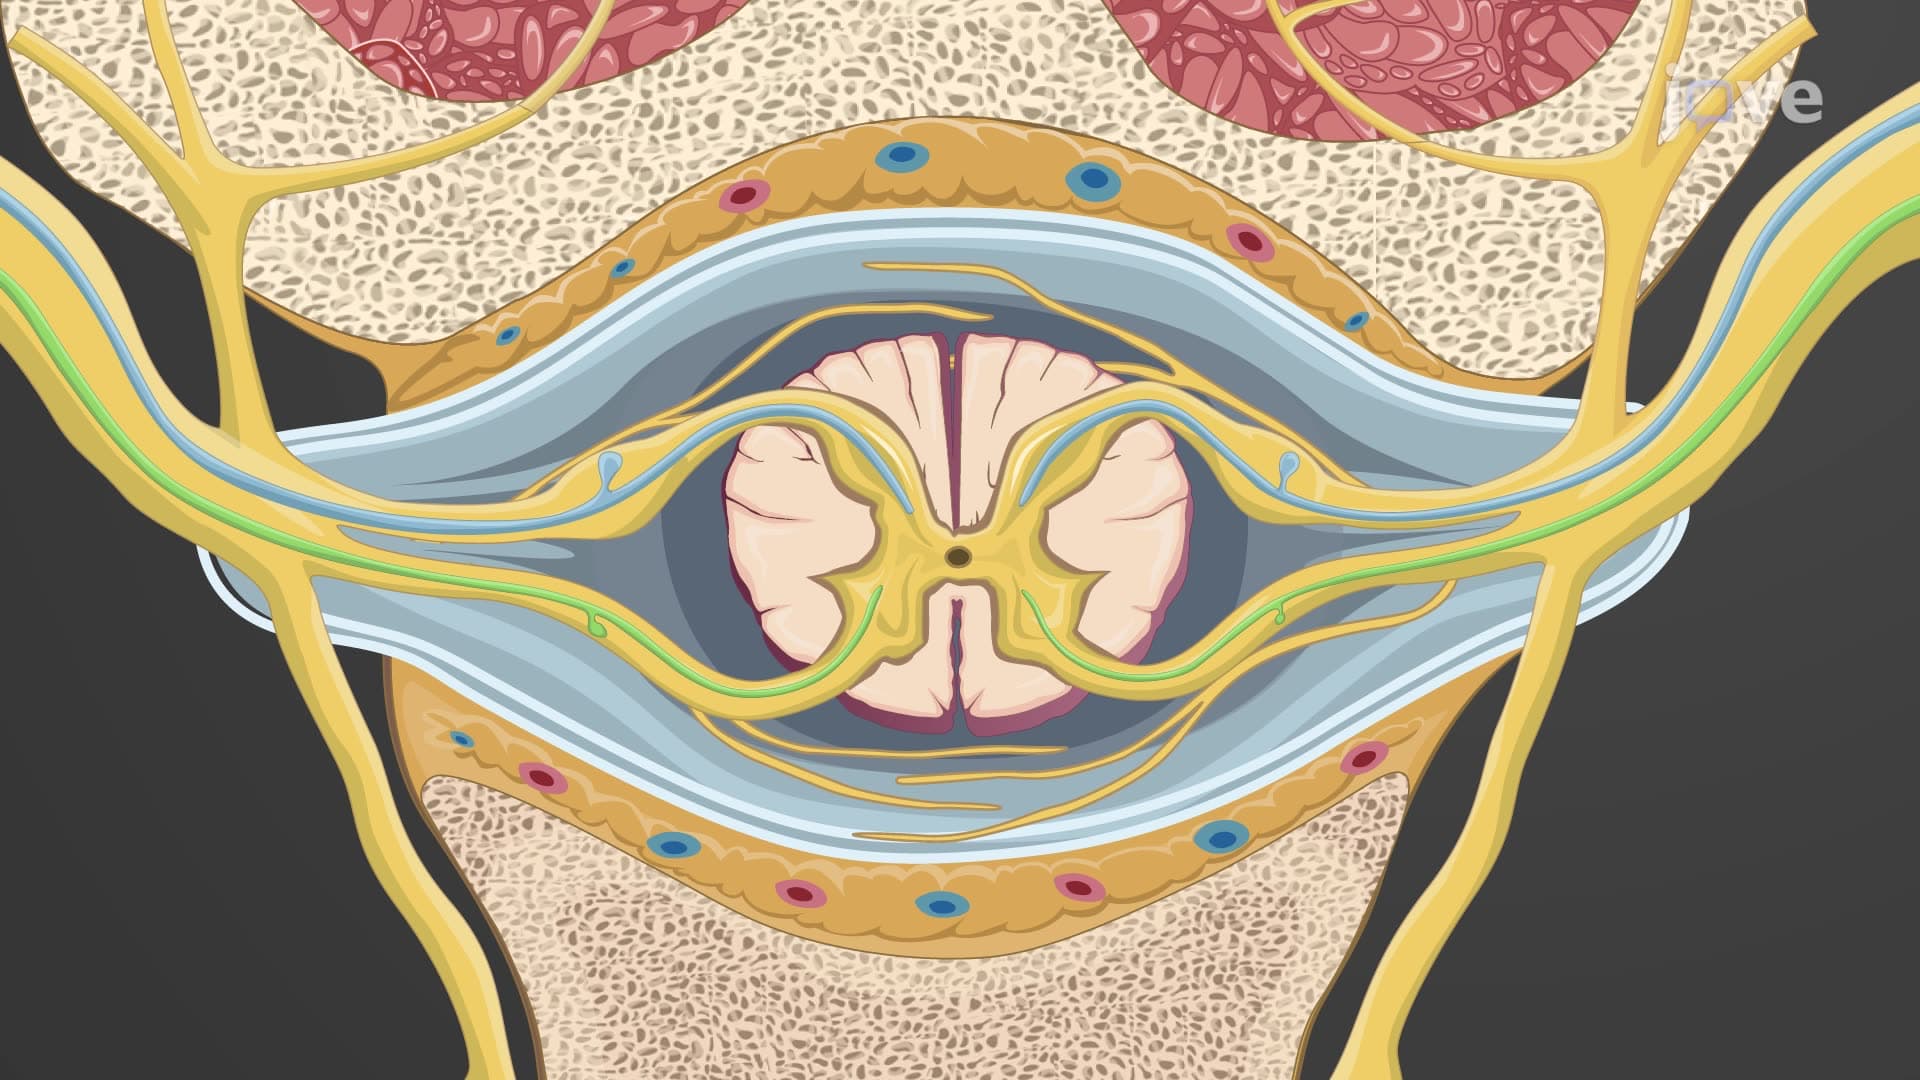
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...