
Interhospital variability in time to discharge to rehabilitation among insured trauma patients
Lisa M Knowlton1, Alex H S Harris, Lakshika Tennakoon
1From the Department of Surgery (L.M.K., L.T., M.T.H., D.A.S., K.L.S.), Stanford University School of Medicine; and Stanford-Surgery Policy Improvement Research and Education (A.H.S.H.) Center (S-SPIRE), Stanford, California.

Background:
Hospital costs are partly a function of length of stay (LOS), which can be impacted by the local availability of postacute care (PAC) resources (inpatient rehabilitation and skilled nursing facilities), particularly for injured patients. We hypothesized that LOS for trauma patients destined for PAC would be variable based on insurance type and hospitals from which they are discharged.
Methods:
We used the 2014 to 2015 National Inpatient Sample from the Healthcare Cost and Utilization Project. We included all adult admissions with a primary diagnosis of trauma (International Classification of Diseases, 9th Revision, Clinical Modification codes), who were insured and discharged to PAC. We then ranked hospitals based upon mean LOS and divided them into quartiles to determine differences. The primary outcome was inpatient LOS; secondary outcome was cost.
Results:
There are 958,005 trauma patients that met the inclusion criteria. Mean LOS varied based upon insurance type (Medicaid vs. Private vs. Medicare: 12.7 days vs. 8.8 days and 5.7 days; p < 0.001). Shortest LOS hospitals had a marginal variation in LOS (Medicaid vs. Private vs. Medicare: 5.5 days vs. 4.8 days vs. 4.2 days; p < 0.001). Longest LOS hospitals had mean LOS that varied substantially (16.4 days vs. 11.0 days vs. 6.7 days; p < 0.001). Multivariate regression controlling for patient and hospital characteristics revealed that Medicaid patients spent Medicaid patients spent an additional 0.4 days in shortest LOS hospitals and an additional 2.6 days in longest LOS hospitals (p < 0.001). The average daily cost of inpatient care was US $3,500 (SD, US $132). Even with conservative estimates, Medicaid patients at hospitals without easy access to rehabilitation incur significant additional inpatient costs over $10,000 in some hospitals.
Conclusion:
Prolonged LOS is likely a function of access to postacute facilities, which is largely out of the hands of trauma centers. Efficiencies in care are magnified by access to postacute beds, suggesting that increased availability of rehabilitation facilities, particularly for Medicaid patients, might help to reduce LOS.
Level Of Evidence:
Epidemiologic, level III; care management, level IV.
More Related Videos
 09:14
Surface Electromyographic Biofeedback as a Rehabilitation Tool for Patients with Global Brachial Plexus Injury Receiving Bionic Reconstruction
Published on: September 28, 2019
 04:49
Author Spotlight: Enhancing Post-Stroke Upper Limb Rehabilitation with Robotic Technologies for Improved Motor Recovery and Functional Outcomes
Published on: September 6, 2024
Related Concept Videos
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:27
RC Circuits: Discharging A Capacitor
 01:11
Variability: Analysis
The range is a simple measure of variability, indicating the difference between the highest and...
 01:09
Random Variables
Uppercase letters such as X or Y denote a random variable. Lowercase letters like x or y denote the value of a random variable. If X is a random variable, then X is written in words, and x is given as a number.
For example, let X = the...
 01:30
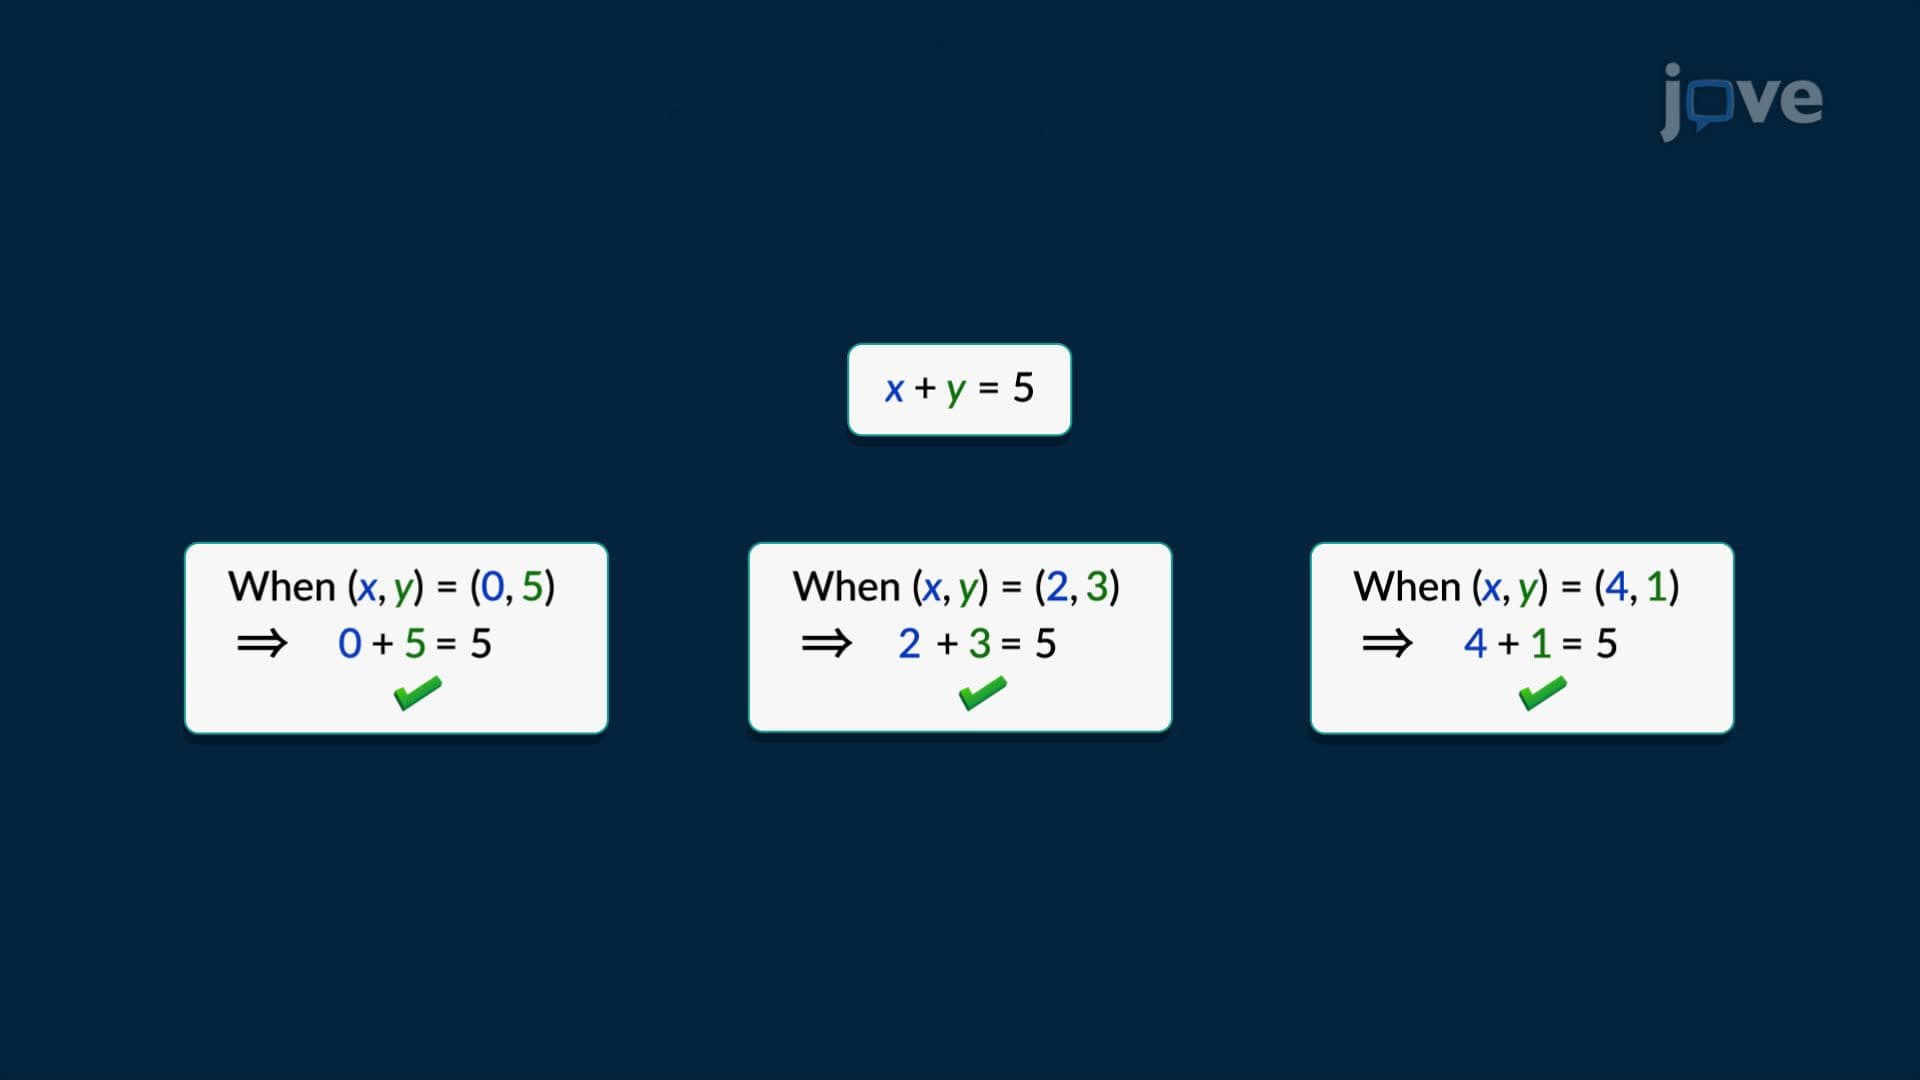
Graphs of Equations in Two Variables
 01:26
Variables Affecting Phosphorescence and Fluorescence