Related Experiment Video
Updated: Feb 1, 2026


Evaluating the Impact of Hydraulic Fracturing on Streams using Microbial Molecular Signatures
Published on: April 4, 2021
Impact of a simplified management algorithm on outcome following exsanguinating pelvic fractures: A 10-year
Richard H Lewis1, John P Sharpe, Bennett Berning
1From the Department of Surgery, University of Tennessee Health Science Center Memphis, Tennessee.

Background:
Optimal management of exsanguinating pelvic fractures remains controversial. Our previous experience suggested that management decisions based on a defined algorithm were associated with a significant reduction in transfusion requirements and mortality. Based on these outcomes, a clinical pathway (PW) for the management of exsanguinating pelvic fractures was developed. The purpose of this study was to evaluate the impact of this PW on outcomes.
Methods:
Consecutive patients over 10 years with blunt pelvic fractures subsequent to the implementation of the clinical PW were identified. Patients with hemodynamically unstable pelvic fractures are managed initially with a pelvic orthotic device. For those with continued hemodynamic instability and no extrapelvic source of hemorrhage, pelvic angiography was performed followed by elective pelvic fixation. Patients managed according to the PW were compared with those patients whose management deviated (DEV) from the PW.
Results:
There were 3,467 patients identified. Three hundred twelve (9%) met entry criteria: 246 (79%) comprised the PW group and 66 (21%) the DEV group. Injury severity, as measured by Injury Severity Score (35 vs. 36; p = 0.55), admission Glasgow Coma Scale (10 vs. 10; p = 0.58), admission BE (-7.4 vs. -6.4, p = 0.38), admission SBP (107 vs. 104, p = 0.53), and PRBC requirements during initial resuscitation (6.1 units vs. 6.6 units, p = 0.22) were similar between the groups. Pelvic orthotic device use was 48% in the DEV group (p < 0.001). Twenty-four percent of the PW group required angiography compared with 74% of the DEV group (p < 0.001). Forty-eight-hour transfusions (11 vs. 16, p = 0.01) and mortality (35% vs. 48%, p = 0.04) were reduced in the PW group compared with the DEV group. Pathway adherence was identified as an independent predictor of both decreased transfusions (β = -5.8, p = 0.002) via multiple linear regression and decreased mortality (hazard ratio, 0.74; 95% confidence interval, 0.42-0.98) via multivariable cox proportional hazards analysis.
Conclusion:
Adherence to a defined clinical PW simplified the management of exsanguinating pelvic fractures and contributed to a reduction in both transfusion requirements and mortality.
Level Of Evidence:
Prognostic, level III.

Related Concept Videos
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 02:24
Predicting Reaction Outcomes
 01:12
Trial and Error and Algorithm
 01:19
Impact of Groups on Groups
 01:26
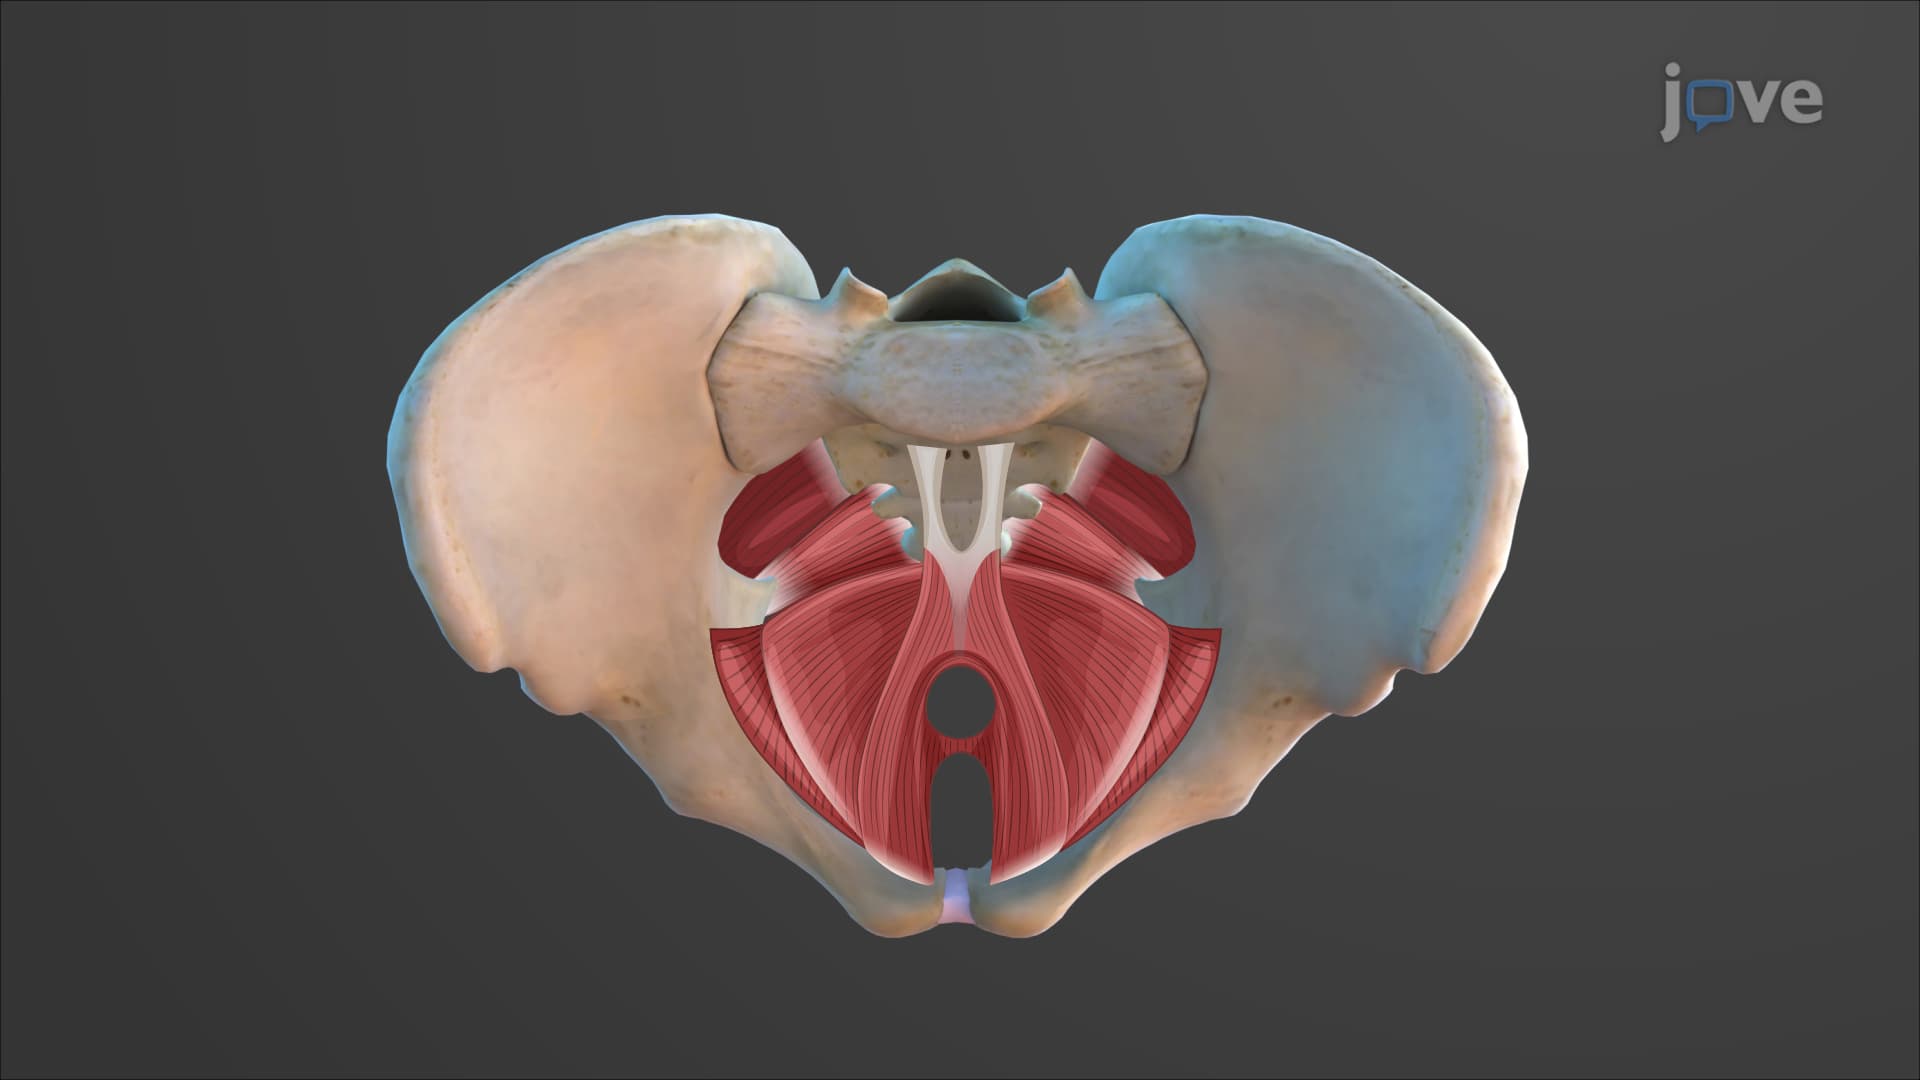
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...