Related Experiment Video
Updated: Feb 1, 2026

Computed Tomography (CT) Guided Implantation of a Totally Implantable Venous Access Port (TIVAP) through Subclavian Vein
Published on: January 13, 2026
Triple lead cephalic versus subclavian vein approach in cardiac resynchronization therapy device implantation
Julia Vogler1, Anne Geisler1, Nils Gosau1
1Department of Electrophysiology, University Heart Center Hamburg, University Hospital Eppendorf, Hamburg, Germany.

Insights
The sole cephalic vein (sCV) approach for cardiac resynchronization therapy (CRT) device implantation is feasible and shows similar complication rates to the subclavian vein (SV) approach. While sCV avoids pneumothorax, it involves higher radiation exposure.
Area of Science:
- Cardiology
- Medical Devices
- Interventional Cardiology
Background:
- Cardiac resynchronization therapy (CRT) device implantation carries risks of severe complications like pneumothorax and hemothorax.
- Limited data exists on the sole cephalic vein (sCV) approach as a potentially safer alternative.
Purpose of the Study:
- To compare the feasibility and safety of a sole cephalic vein (sCV) approach versus the traditional subclavian vein (SV) approach for de novo CRT implantations.
Main Methods:
- A prospective cohort study enrolled 24 patients undergoing de novo CRT implantation via sCV (Group A).
- Fifty-four age-matched patients implanted via SV served as the reference group (Group B).
- Procedural success, complication rates, procedure duration, fluoroscopy time, and radiation dosage were recorded over a 4-week follow-up.
Main Results:
- Successful CRT implantation was achieved in all sCV patients (91.7% using cephalic access alone) and 96.3% of SV patients.
- No pneumothorax occurred in the sCV group, versus two cases in the SV group.
- Overall complication rates were similar (13.0% for sCV vs. 12.5% for SV), but radiation dosage was significantly higher in the sCV group (p=0.001).
Conclusions:
- De novo CRT implantation using a sole cephalic vein approach is feasible in clinical practice.
- The sCV approach demonstrates similar procedural success and complication rates compared to the SV approach.
- Higher radiation exposure with the sCV approach necessitates further investigation into lead longevity and long-term benefits in controlled studies.
Abstract:
Cardiac resynchronization therapy (CRT) device implantation is associated with severe complications including pneumo- and hemothorax. Data on a sole cephalic vein approach (sCV), potentially preventing these complications, are limited. The aim of our study was to compare a sole cSV with a subclavian vein approach (SV) in CRT implantations with respect to feasibility and safety. We performed a prospective cohort study enrolling twenty-four consecutive de-novo CRT implantations (group A) using a sCV at two centers. Fifty-four age-matched CRT patients implanted via the SV served (group B) as reference. Procedural success rate and complications were recorded during a follow-up of 4 weeks. All CRTs could be implanted in group A, with 91.7% using cephalic access alone. In group B, CRT implantation was successfully performed in 96.3%. Procedure and fluoroscopy duration were similar for both groups (sCV vs. SV: 119 ± 45 vs. 106 ± 31 minutes, 17 ± 9 vs 14 ± 9 minutes). Radiation dosage was higher in sCV group vs. SV (2984 ± 2370 vs. 1580 ± 1316 cGy*cm2; p = 0.001). There was no case of a pneumothorax in group of sCV, while two cases were observed using SV. Overall complication rate was similar (sCV: 13.0% vs. SV: 12.5%). de-novo CRT implantation using a triple cephalic vein approach is feasible. Procedure duration and complication rates were similar, while radiation dosage was higher in the sCV compared to the SV approach. Despite its feasibility in the clinical routine, controlled prospective studies with longer follow-up are required to elucidate a potential benefit with respect to lead longevity.


Related Concept Videos
 01:24
Cephalic Phase of Digestion
 01:06
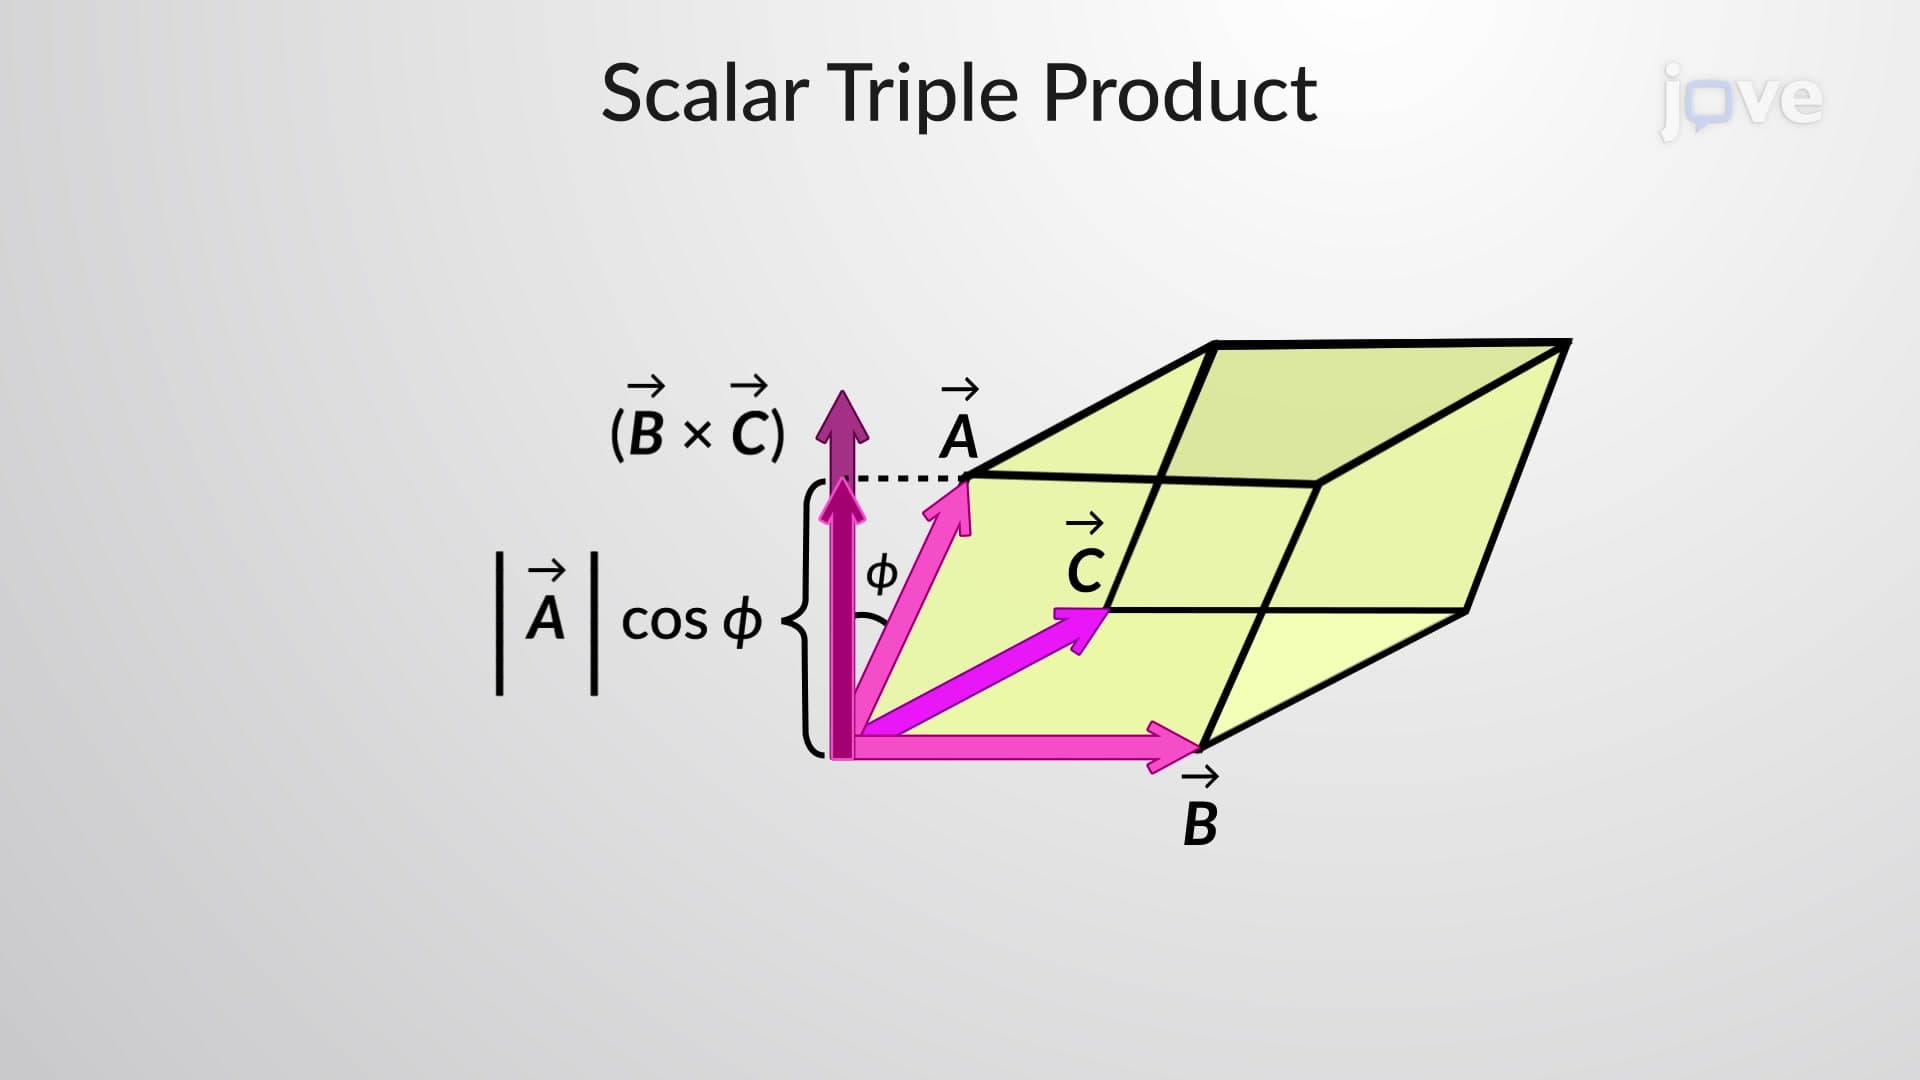
Scalar and Vector Triple Products
The scalar triple product is the dot product of a vector with the cross product of two vectors....
 01:17
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:22
Phase-lead and Phase-lag Controllers
 00:59
Gene Therapy
 01:19
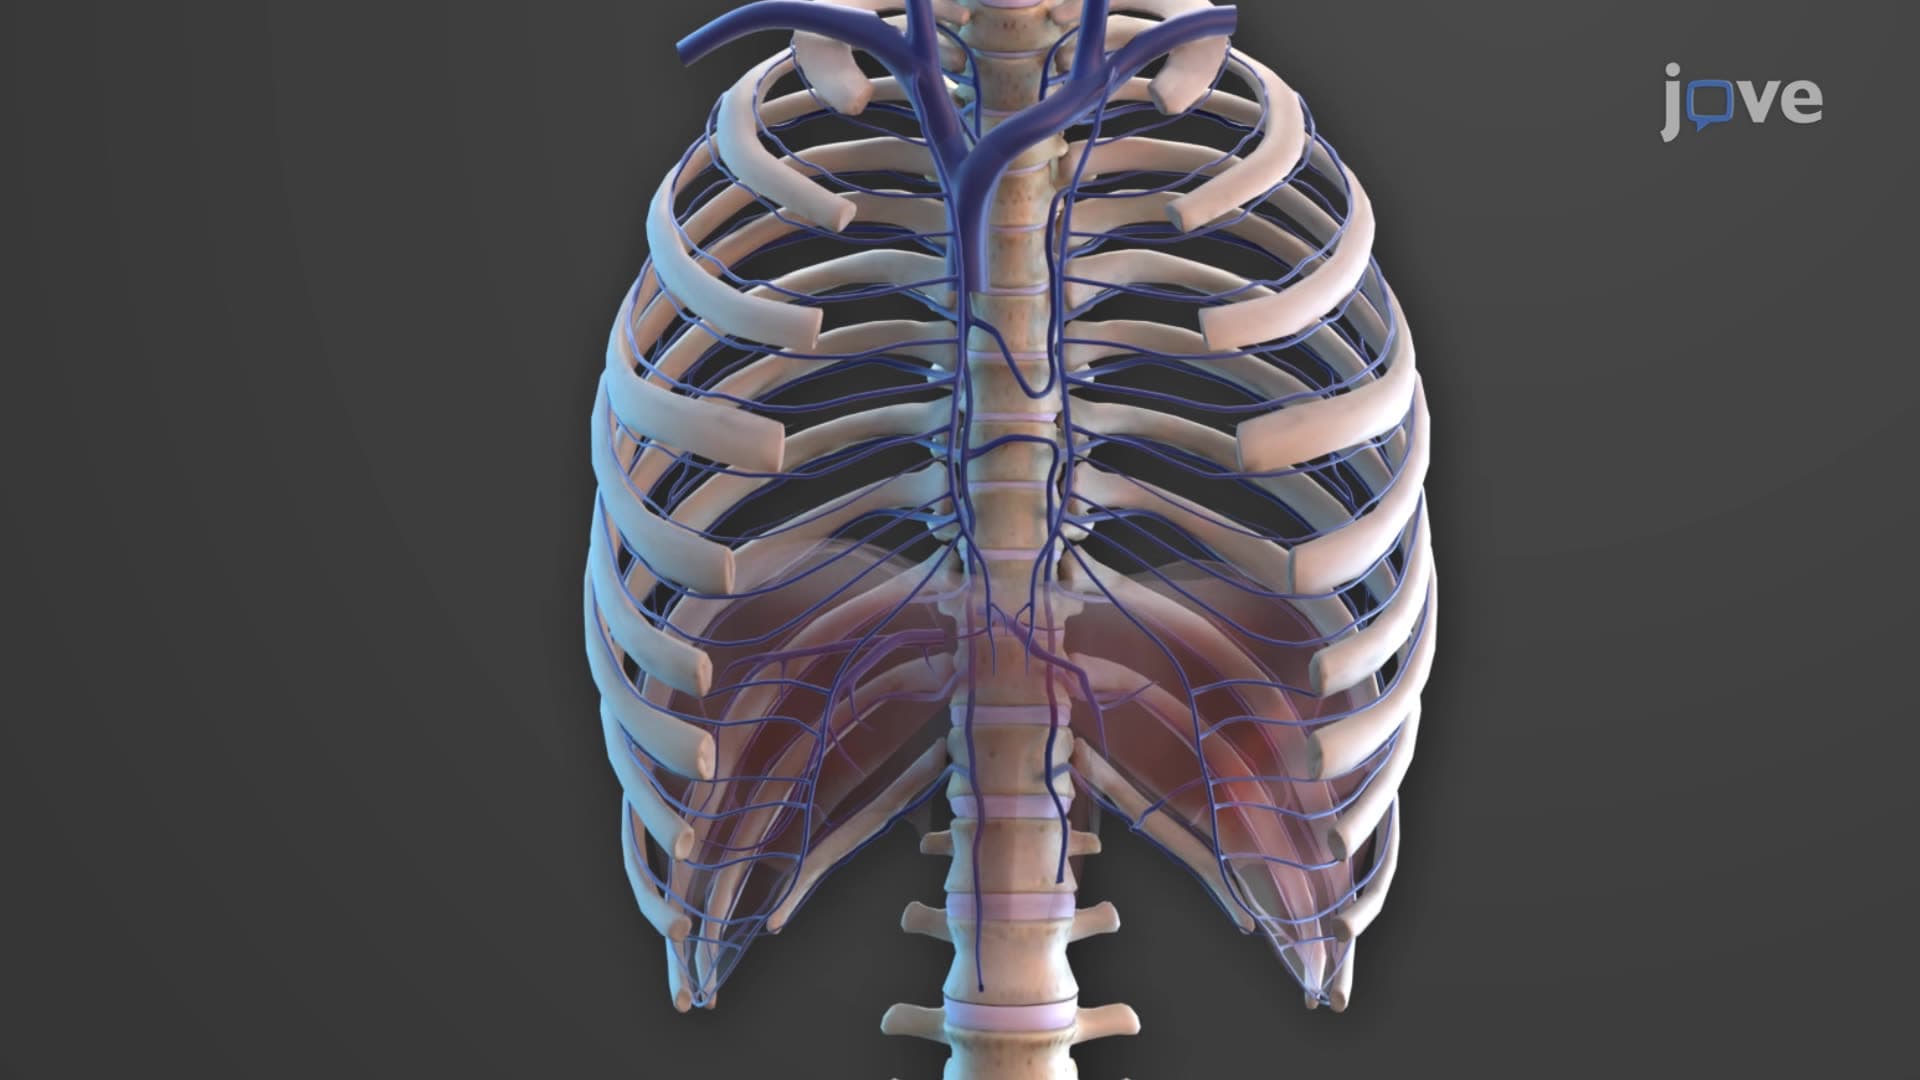
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...