Related Experiment Video
Updated: Feb 1, 2026


Surgical Swine Model of Chronic Cardiac Ischemia Treated by Off-Pump Coronary Artery Bypass Graft Surgery
Published on: March 27, 2018
Steroids in cardiac surgery trial: a substudy of surgical site infections
Graham R McClure1,2, Emilie P Belley-Cote2,3,4,5, John Harlock6
1Michael G. DeGroote School of Medicine, McMaster University, Hamilton, ON, Canada.

Purpose:
Postoperative infection, particularly in cardiac surgery, results in significant morbidity, mortality, and healthcare cost. Identification of novel predictors of postoperative infection can target high-risk populations for prophylactic intervention.
Methods:
Steroids in cardiac surgery (SIRS) was a multi-centre randomized-controlled trial assessing intraoperative administration of methylprednisone during cardiac surgery, which enrolled 7,507 patients across 80 centres in 18 countries. It demonstrated that administration of steroids had no effect on mortality or major morbidity after cardiac surgery. Our primary objective was to identify risk factors for postoperative surgical site infections using SIRS participants as a cohort. We excluded patients who did not undergo surgery, died intraoperatively, or died within 48 hr of the operation. Patients were assessed for development of "surgical site infection" over the first 30 days postoperatively. Using theoretical and previously identified risk factors, we used forward stepwise entry to create a binary logistic regression model.
Results:
Follow-up at 30 days was complete for all patients; 7,406 were included in the cohort. Surgical site infection occurred in 180 (4.8%) and 184 (5.0%) of patients in the placebo and steroid arms respectively. Significant risk factors (P < 0.05 level) included: diabetes managed with insulin (adjusted odds ratio [aOR]: 1.55; 95% confidence interval [CI] 1.13 to 2.12), oral hypoglycemics (aOR 1.60; 95% CI 1.18 to 2.16), or diet (aOR 1.81; 95% CI 1.16 to 2.83), female sex (aOR 1.34; 95% CI 1.05 to 1.71), renal failure with (aOR 2.03; 95% CI 1.06 to 3.91), and without (aOR 1.50; 95% CI 1.04 to 2.14) dialysis, > 96 min cardiopulmonary bypass (CPB) time (aOR 1.84; 95% CI 1.44 to 2.35), body mass index (BMI) < 22.3 (aOR 0.44; 95% CI 0.28 to 0.71) or > 30 (aOR 1.49; 95% CI 1.17 to 1.89), peak intensive care unit blood glucose (aOR 1.02 per mmol·L-1; 95% CI 1.00 to 1.04), and coronary artery bypass grafting (CABG) operation type (aOR 2.59; 95% CI 1.87 to 3.59).
Conclusions:
Patients undergoing CABG, requiring longer CPB, with higher BMI, or with diabetes, are at elevated risk of surgical site infection. Strategies to mitigate this risk warrant further investigation.

Related Concept Videos
 01:11
Clinical Trials: Overview
 01:12
Trial and Error and Algorithm
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:12
Statistical Software for Data Analysis and Clinical Trials
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
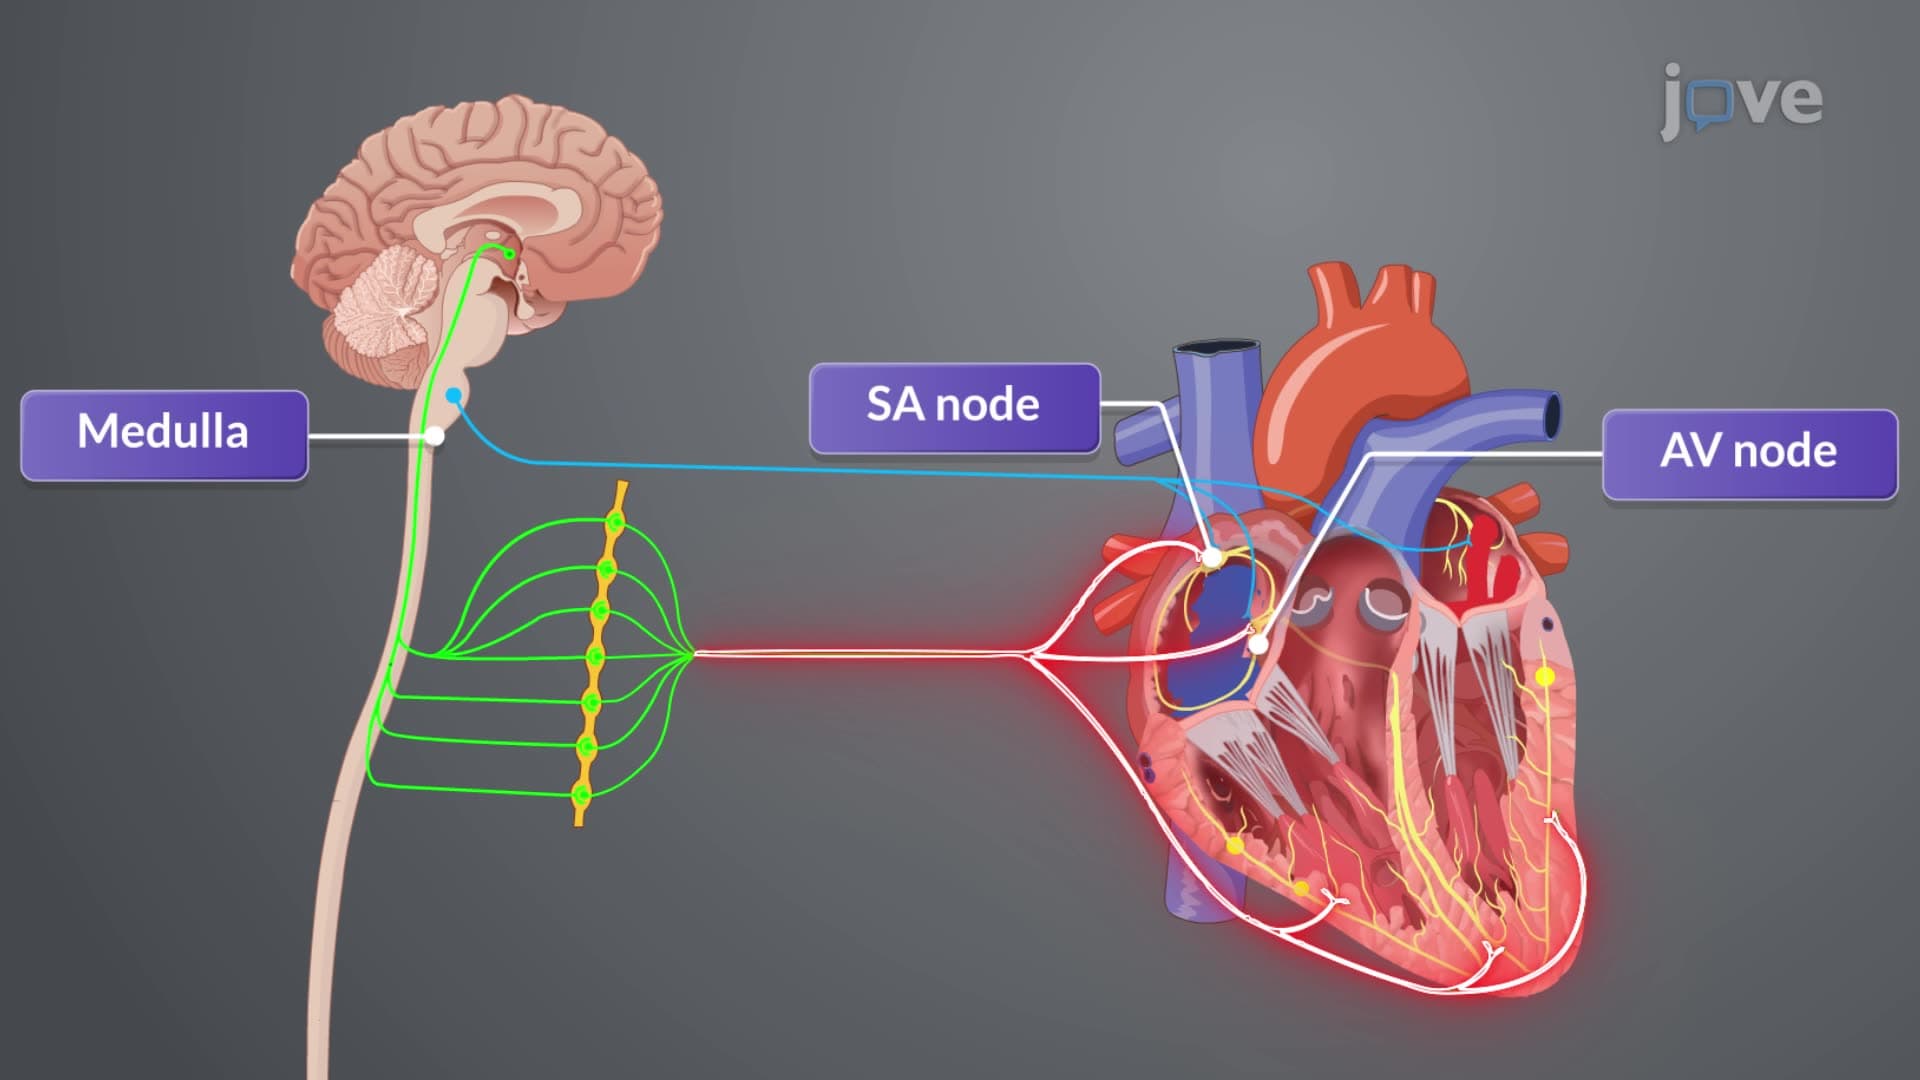
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...