Related Experiment Video
Updated: Feb 1, 2026
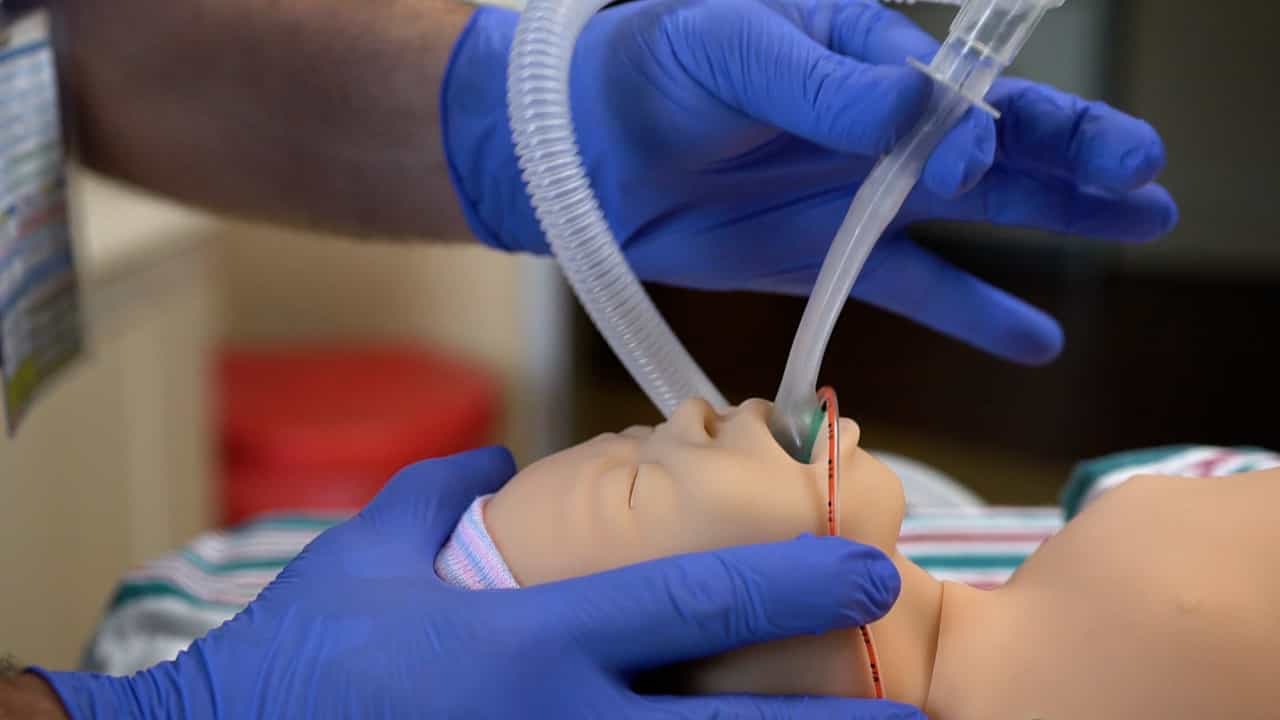
Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
[Feasibility of supraglottic tracheal tube ventilation during painless fiberbronchoscopy]
1Department of Anesthesiology, Affiliated Hangzhou First People's Hospital, Zhejiang University School of Medicine, Hangzhou 310006, China.

Abstract:
Objective: To evaluate the feasibility and safety of supraglottic tracheal tube ventilation by comparing with modified laryngeal mask airway ventilation during painless fiberbronchoscopy. Methods: This was a prospective study. Twenty-eight patients undergoing painless fiberbronchoscopy in Hangzhou First People's Hospital were randomly divided into 2 groups(n=14): supraglottic tracheal tube ventilation(group A) and modified laryngeal mask airway(group B). MAP, HR, SpO(2), P(ET)CO(2) and BIS were recorded after entering the operating room(T(0)), after anesthesia induction(T(1)), immediately after inserting laryngeal mask airway or tracheal tube(T(2)), fiberbronchoscopy inserting(T(3)), at the end of the operation(T(4)), and at the recovery of patients' consciousness(T(5)). The arterial carbon dioxide partial pressure(PaCO(2)), the time spent in successful positioning of the tube, the endoscope indwelling duration, operative time, tube drawing time, patients' awakening time, satisfaction of operators, adverse events during anesthesia, the numbers of bucking or body moving were also recorded.The dose of propofol and remifentanil were also statisticed. Results: P(ET)CO(2) in group A at T(0), T(1), T(2), T(3), T(4), T(5) were (36.9±4.1), (36.3±4.7), (38.1±5.6), (40.4±4.0), (48.8±7.7), (45.3±7.6) mmHg, P(ET)CO(2) in group B were (38.6±4.4), (37.8±5.6), (37.8±5.4), (37.4±6.7), (43.3±12.2), (43.5±8.0) mmHg, at the end of operation, the P(ET)CO(2) at T(4) and T(5) were significantly higher than at T(0) in group A and group B (F=14.582, 12.651, all P<0.05). The PaCO(2) in group A was (62.0±4.7) mmHg , which was significantly higher than group B at the end of operation[(51.9±4.2) mmHg, t=2.432, P<0.05]. The time spent successfully positioning the insertion in group A and group B were (17.6±7.5), (29.8±13.6)s, the endoscope indwelling duration were(0.8±0.1), (1.4±0.3)min, and the operation time were(32.3±4.3), (46.8±4.8)min, there were significantly difference between group A and group B(t=2.670, 2.214, 2.166, all P<0.05). There were no significantly difference of the numbers of bucking or body moving , the satisfaction of operators and patients, and adverse events (all P>0.05). Conclusion: Supraglottic tracheal tube ventilation for painless fiberbronchoscopy is a safe and effective procedure.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:16
Uterine Tubes
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....