

QRS Area Is a Strong Determinant of Outcome in Cardiac Resynchronization Therapy
Antonius M W van Stipdonk1, Iris Ter Horst1,2, Marielle Kloosterman3
1Department of Cardiology, Maastricht University Medical Centre, The Netherlands (A.M.W.v.S., H.J.G.M.C., K.V.).

Background:
The combination of left bundle branch block (LBBB) morphology and QRS duration is currently used to select patients for cardiac resynchronization therapy (CRT). These parameters, however, have limitations. This study evaluates the value of QRS area compared with that of QRS duration and morphology in the association with clinical and echocardiographic outcomes in a large cohort of CRT patients.
Methods:
A retrospective multicentre study was conducted in 1492 CRT patients. LBBB morphology, QRS duration, and QRS area in the baseline 12-lead ECG were evaluated for their association with the occurrence of the combined primary end point of all-cause mortality, cardiac transplantation, and left ventricular assist device implantation. Secondary end points were heart failure hospitalization within the first year after implantation and echocardiographic reduction in left ventricular end-systolic volume.
Results:
During a mean follow-up period of 3.4 years, 32% of patients reached the primary end point. The association of QRS area with all outcomes was stronger than that of LBBB morphology and QRS duration separately and at least as strong as their combination. QRS area identified patients who did not experience the primary end point better than QRS morphology and QRS duration (area under the curve, 0.61 versus 0.55 and 0.51, respectively; P<0.001). Furthermore, QRS area identifies patients with echocardiographic remodeling in response to CRT better than QRS morphology and duration (area under the curve, 0.69 versus 0.58 and 0.58, respectively; P<0.001). QRS area was the only independent electrocardiographic determinant associated with the primary end point; hazard ratio, 0.50 (0.35-0.71). Furthermore, QRS area showed significant association with outcomes in both patients with and without LBBB and QRS ≥150 ms.
Conclusions:
QRS area has a strong association to clinical and echocardiographic response to CRT, at least as strong as current patient selection parameters. QRS area may be particularly useful to predict CRT response in patients without a wide LBBB.


Related Concept Videos
 02:28
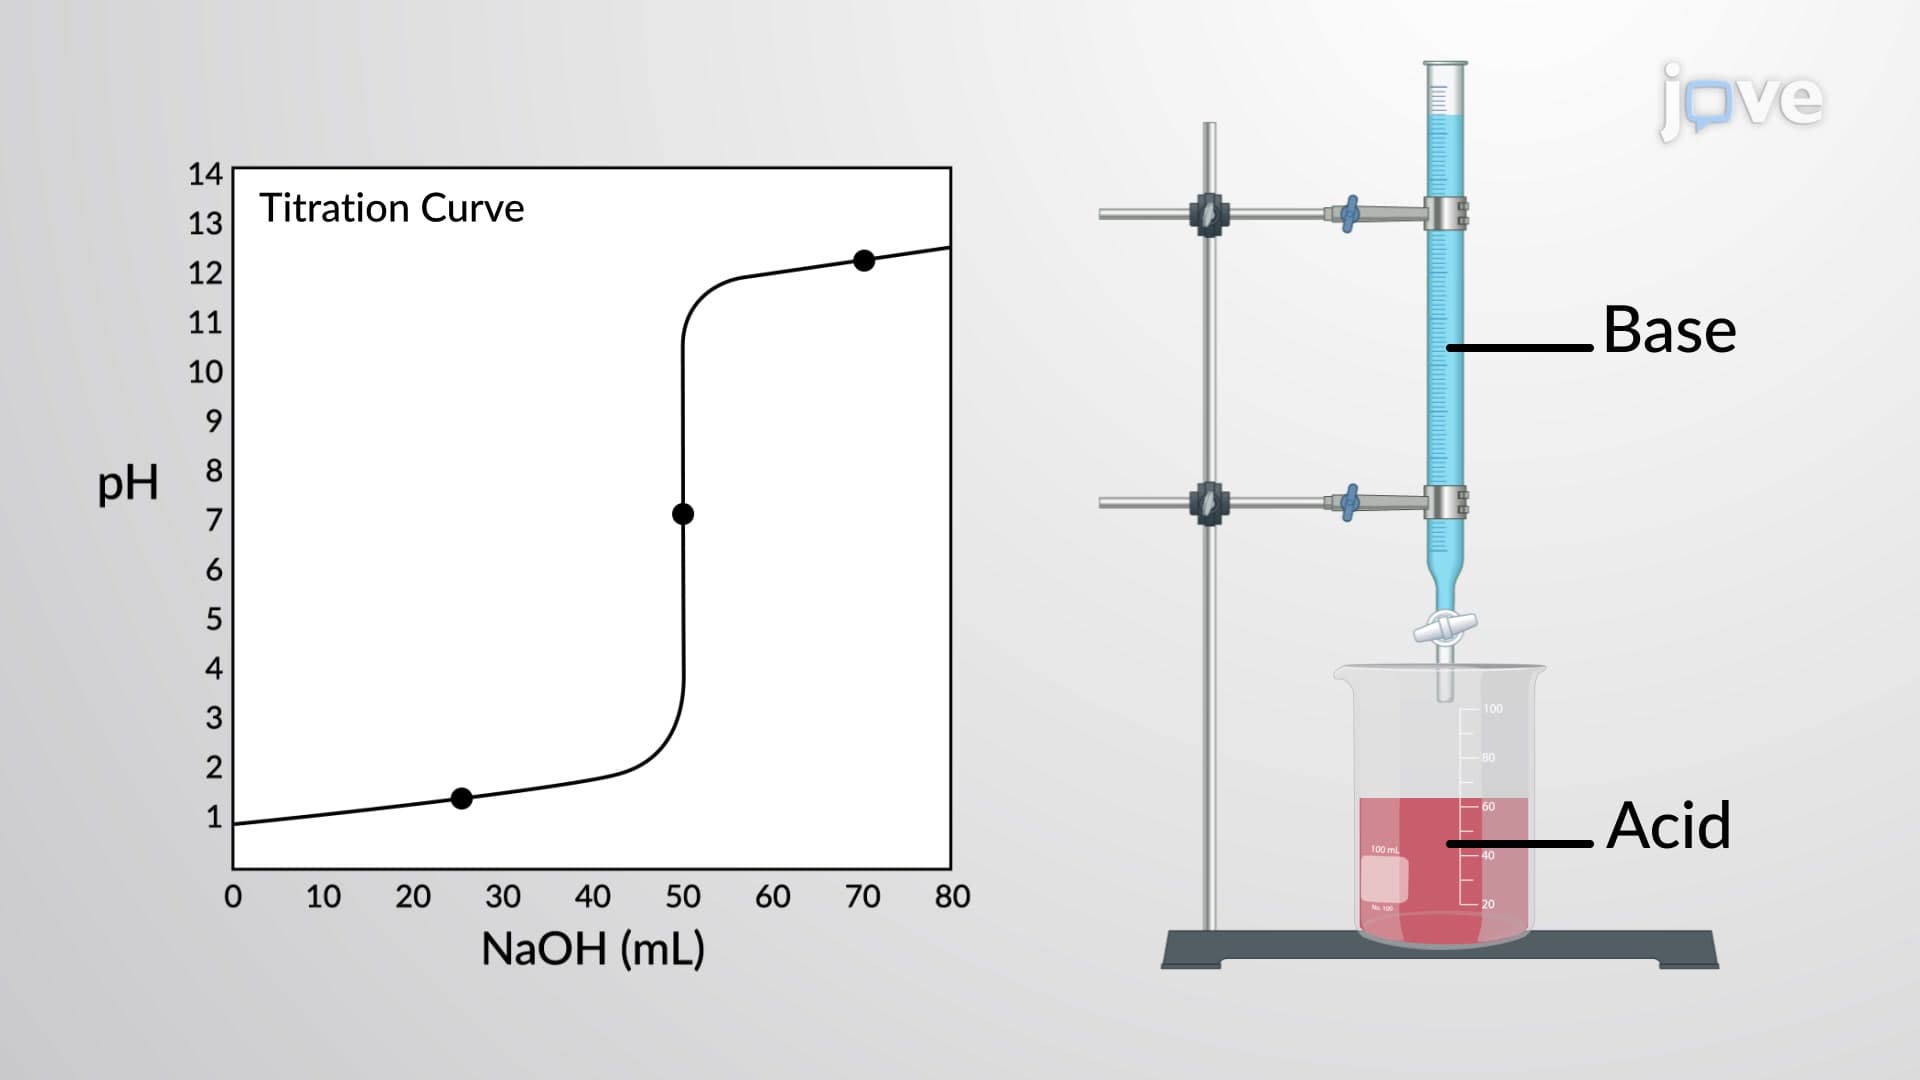
Titration Calculations: Strong Acid - Strong Base
A titration is carried out for 25.00 mL of 0.100 M HCl (strong acid) with 0.100 M of a strong base NaOH. The pH at different volumes of added base solution can be calculated as follows:
(a) Titrant volume = 0 mL. The solution pH is due to the acid ionization of HCl. Because this is a strong acid, the ionization is complete and the hydronium ion molarity is 0.100 M. The pH of the solution is then:
 03:22
Strong Acid and Base Solutions
 01:23
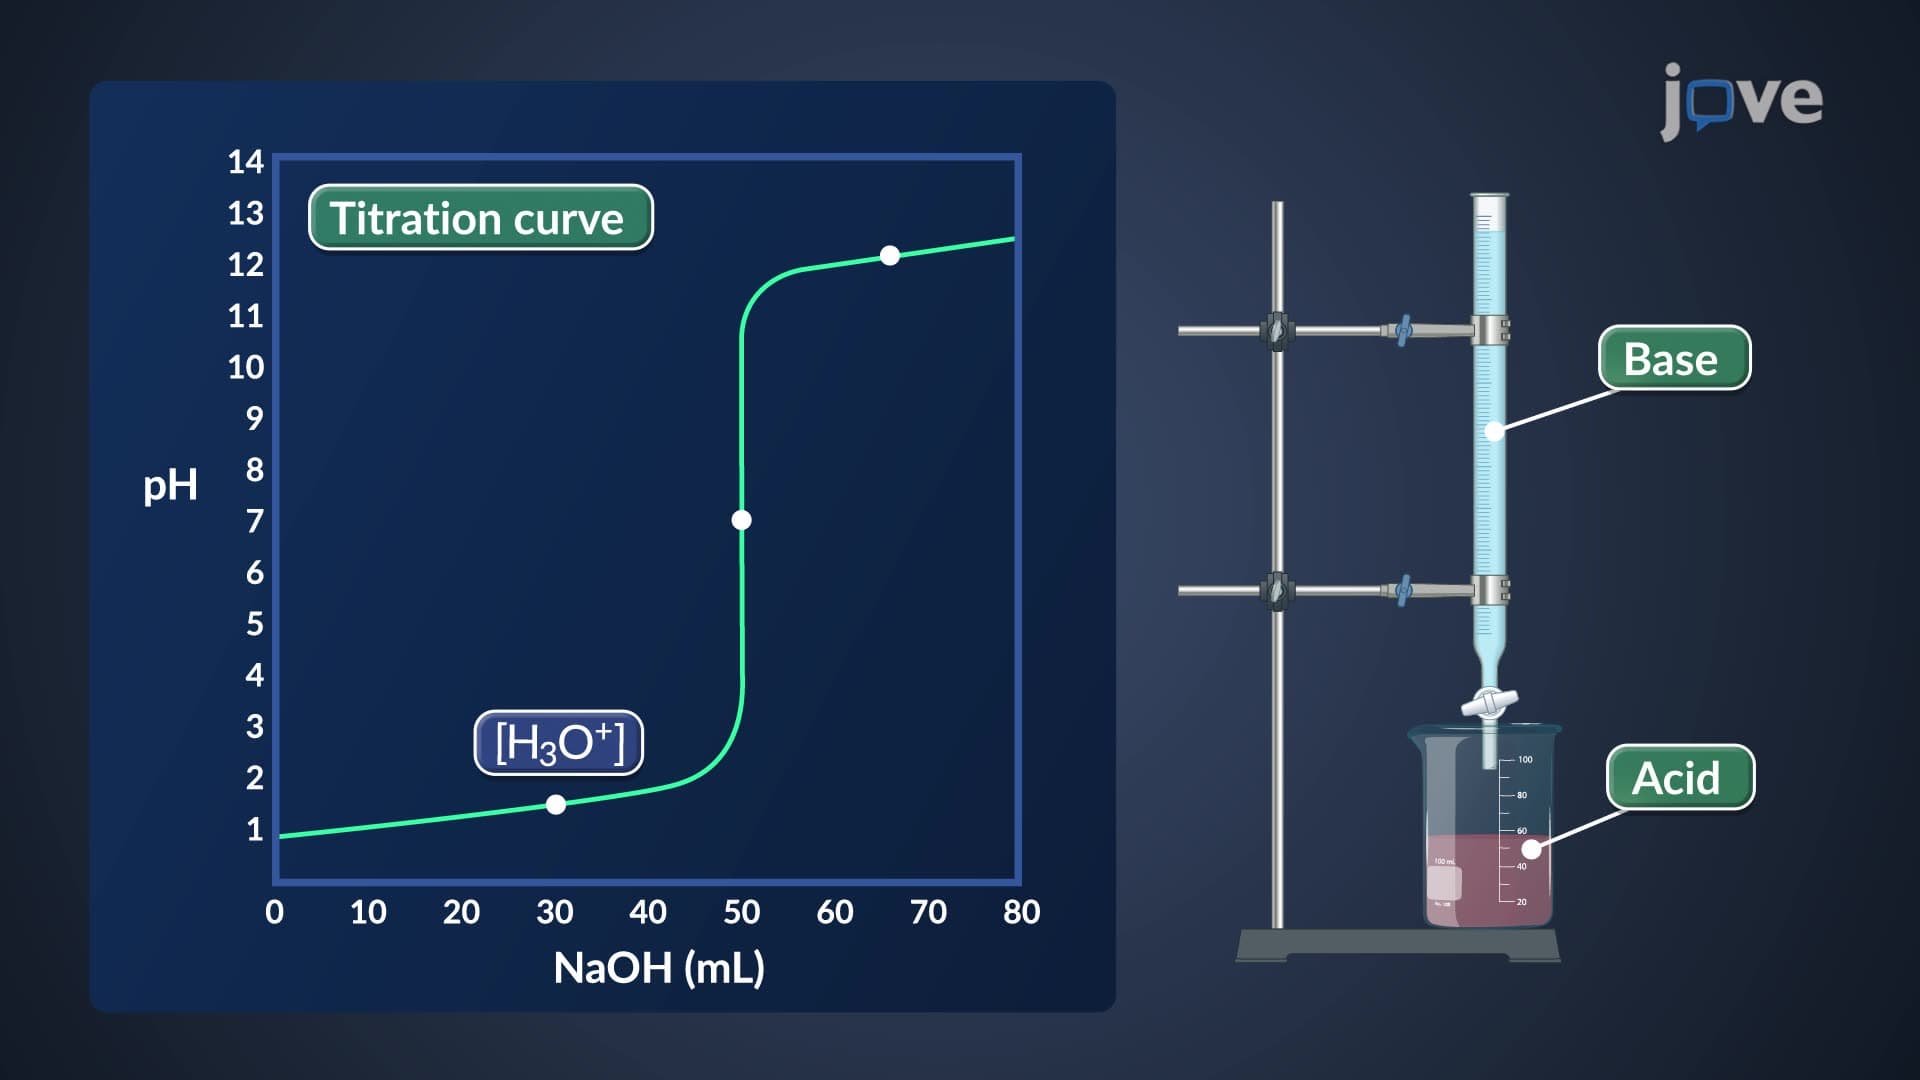
Titration of a Strong Acid with a Strong Base
 03:55
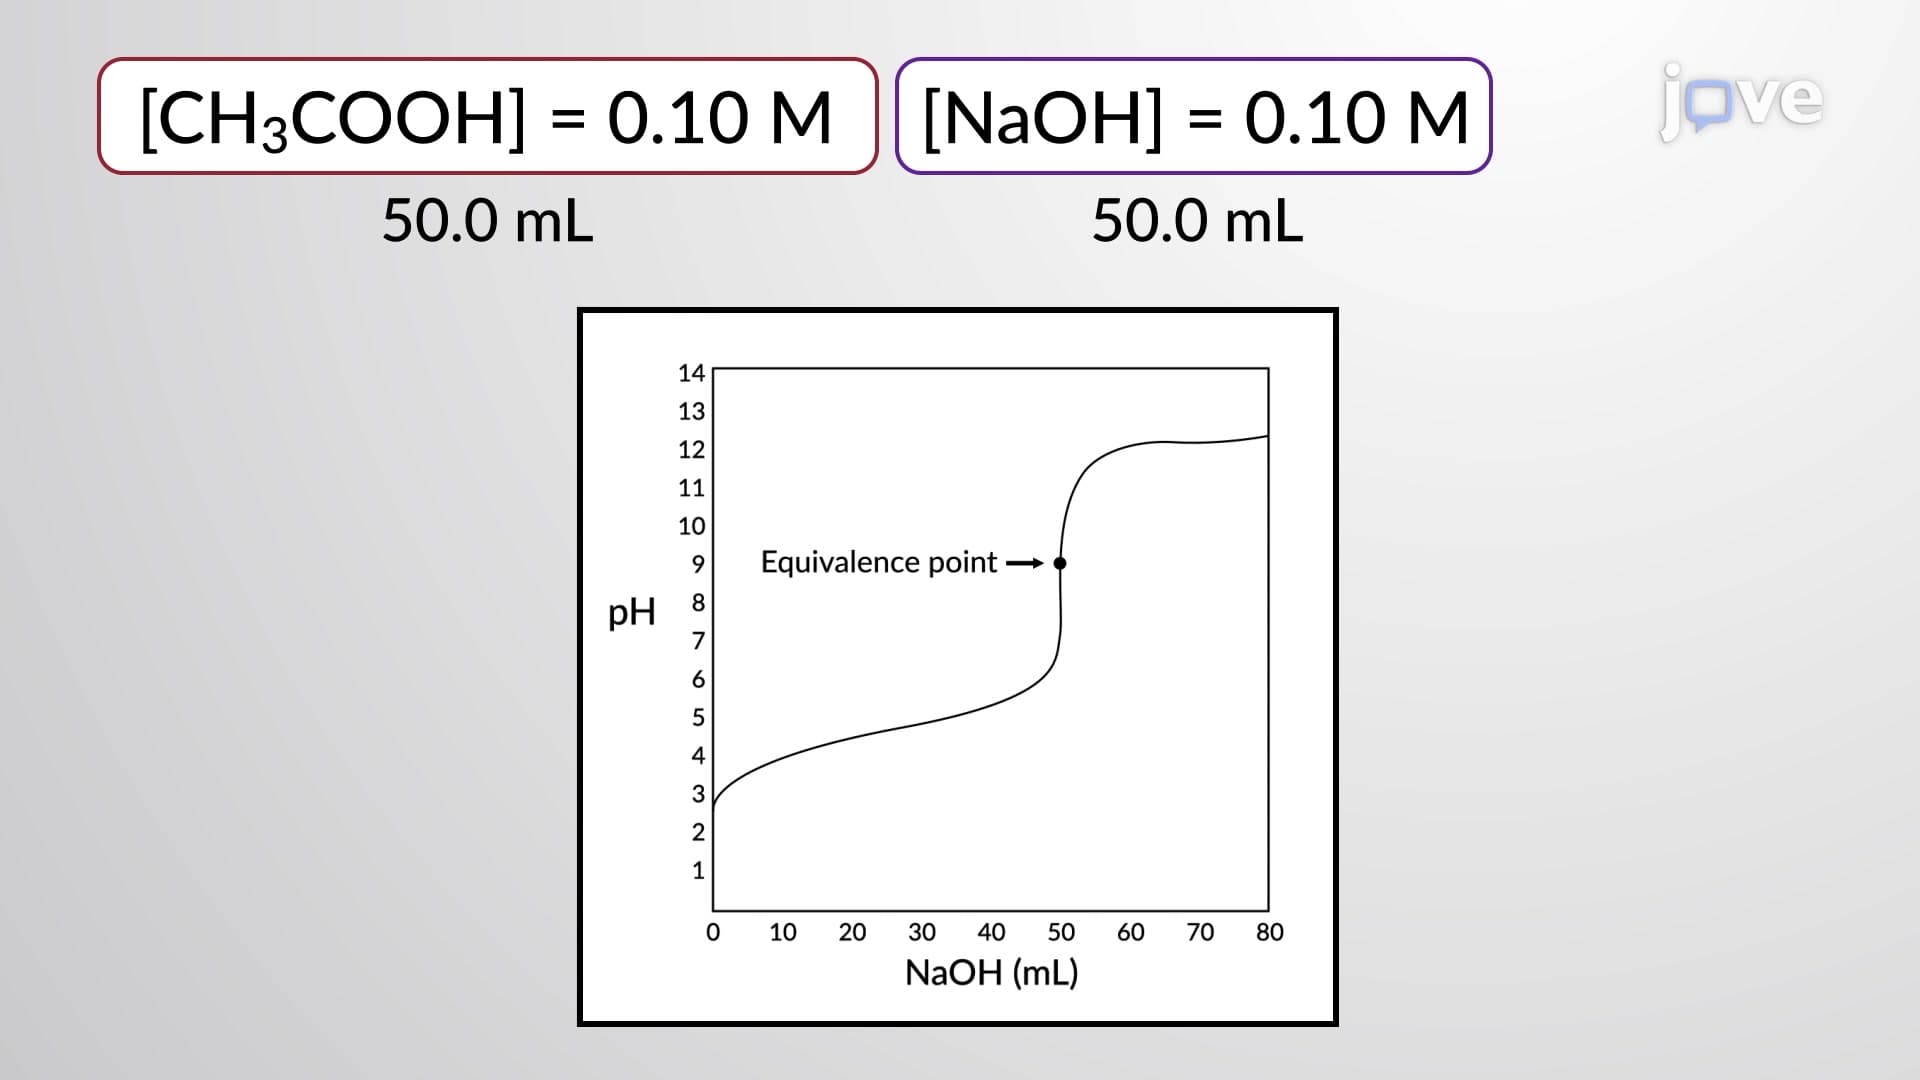
Titration Calculations: Weak Acid - Strong Base
For the titration of 25.00 mL of 0.100 M CH3CO2H with 0.100 M NaOH, the reaction can be represented as:
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...