Related Experiment Video
Updated: Feb 1, 2026


Investigating the Pathogenesis of MYH7 Mutation Gly823Glu in Familial Hypertrophic Cardiomyopathy using a Mouse Model
Published on: August 8, 2022
Hypertrophic cardiomyopathy with dynamic obstruction and high left ventricular outflow gradients associated with
Mark V Sherrid1, Katherine Riedy1, Barry Rosenzweig1
1Hypertrophic Cardiomyopathy Program, Division of Cardiology, New York University Langone Health, New York University School of Medicine, New York City, New York.

Insights
Acute left ventricular ballooning in obstructive hypertrophic cardiomyopathy is rare but can cause severe instability. Early recognition and treatment, including surgery in some cases, can lead to full recovery.
Area of Science:
- Cardiology
- Cardiovascular Medicine
- Medical Diagnostics
Background:
- Acute left ventricular (LV) apical ballooning with normal coronary angiography is a rare presentation in obstructive hypertrophic cardiomyopathy (OHCM).
- This condition can be associated with severe hemodynamic instability and profound LV decompensation.
Purpose of the Study:
- To investigate the occurrence and characteristics of acute LV apical ballooning in patients with OHCM.
- To understand the clinical course, management, and outcomes of this specific complication.
Main Methods:
- A retrospective search was conducted in two HCM treatment program databases for cases of acute LV ballooning with apical hypokinesia/akinesia.
- Diagnosis of OHCM was based on conventional criteria, and patient data including LV hypertrophy, outflow tract (LVOT) gradients, and echocardiographic findings were analyzed.
Main Results:
- Of 1519 patients, 13 (0.9%) presented with acute LV ballooning, characterized by high LVOT gradients (92 ± 37 mm Hg).
- The majority were female (77%), with mild septal hypertrophy and specific anatomical features like elongated anterior mitral leaflets (77%).
- Complications included cardiogenic shock and heart failure in 5 patients; 3 required urgent surgery for LVOT obstruction, resulting in immediate improvement and sustained normal LV function post-operatively.
Conclusions:
- Acute LV apical ballooning associated with high dynamic LVOT gradients can occur in obstructive HCM.
- This syndrome requires prompt recognition on echocardiography due to its association with severe, yet potentially reversible, LV decompensation.
Background:
Acute left ventricular (LV) apical ballooning with normal coronary angiography occurs rarely in obstructive hypertrophic cardiomyopathy (OHCM); it may be associated with severe hemodynamic instability.
Methods, Results:
We searched for acute LV ballooning with apical hypokinesia/akinesia in databases of two HCM treatment programs. Diagnosis of OHCM was made by conventional criteria of LV hypertrophy in the absence of a clinical cause for hypertrophy and mitral-septal contact. Among 1519 patients, we observed acute LV ballooning in 13 (0.9%), associated with dynamic left ventricular outflow tract (LVOT) obstruction and high gradients, 92 ± 37 mm Hg, 10 female (77%), age 64 ± 7 years, LVEF 31.6 ± 10%. Septal hypertrophy was mild compared to that of the rest of our HCM cohort, 15 vs 20 mm (P < 0.00001). An elongated anterior mitral leaflet or anteriorly displaced papillary muscles occurred in 77%. Course was complicated by cardiogenic shock and heart failure in 5, and refractory heart failure in 1. High-dose beta-blockade was the mainstay of therapy. Three patients required urgent surgical relief of LVOT obstruction, 2 for refractory cardiogenic shock, and one for refractory heart failure. In the three patients, surgery immediately normalized refractory severe LV dysfunction, and immediately reversed cardiogenic shock and heart failure. All have normal LV systolic function at 45-month follow-up, and all have survived.
Conclusions:
Acute LV apical ballooning, associated with high dynamic LVOT gradients, may punctuate the course of obstructive HCM. The syndrome is important to recognize on echocardiography because it may be associated with profound reversible LV decompensation.
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for:
 01:26
What is an Electrochemical Gradient?
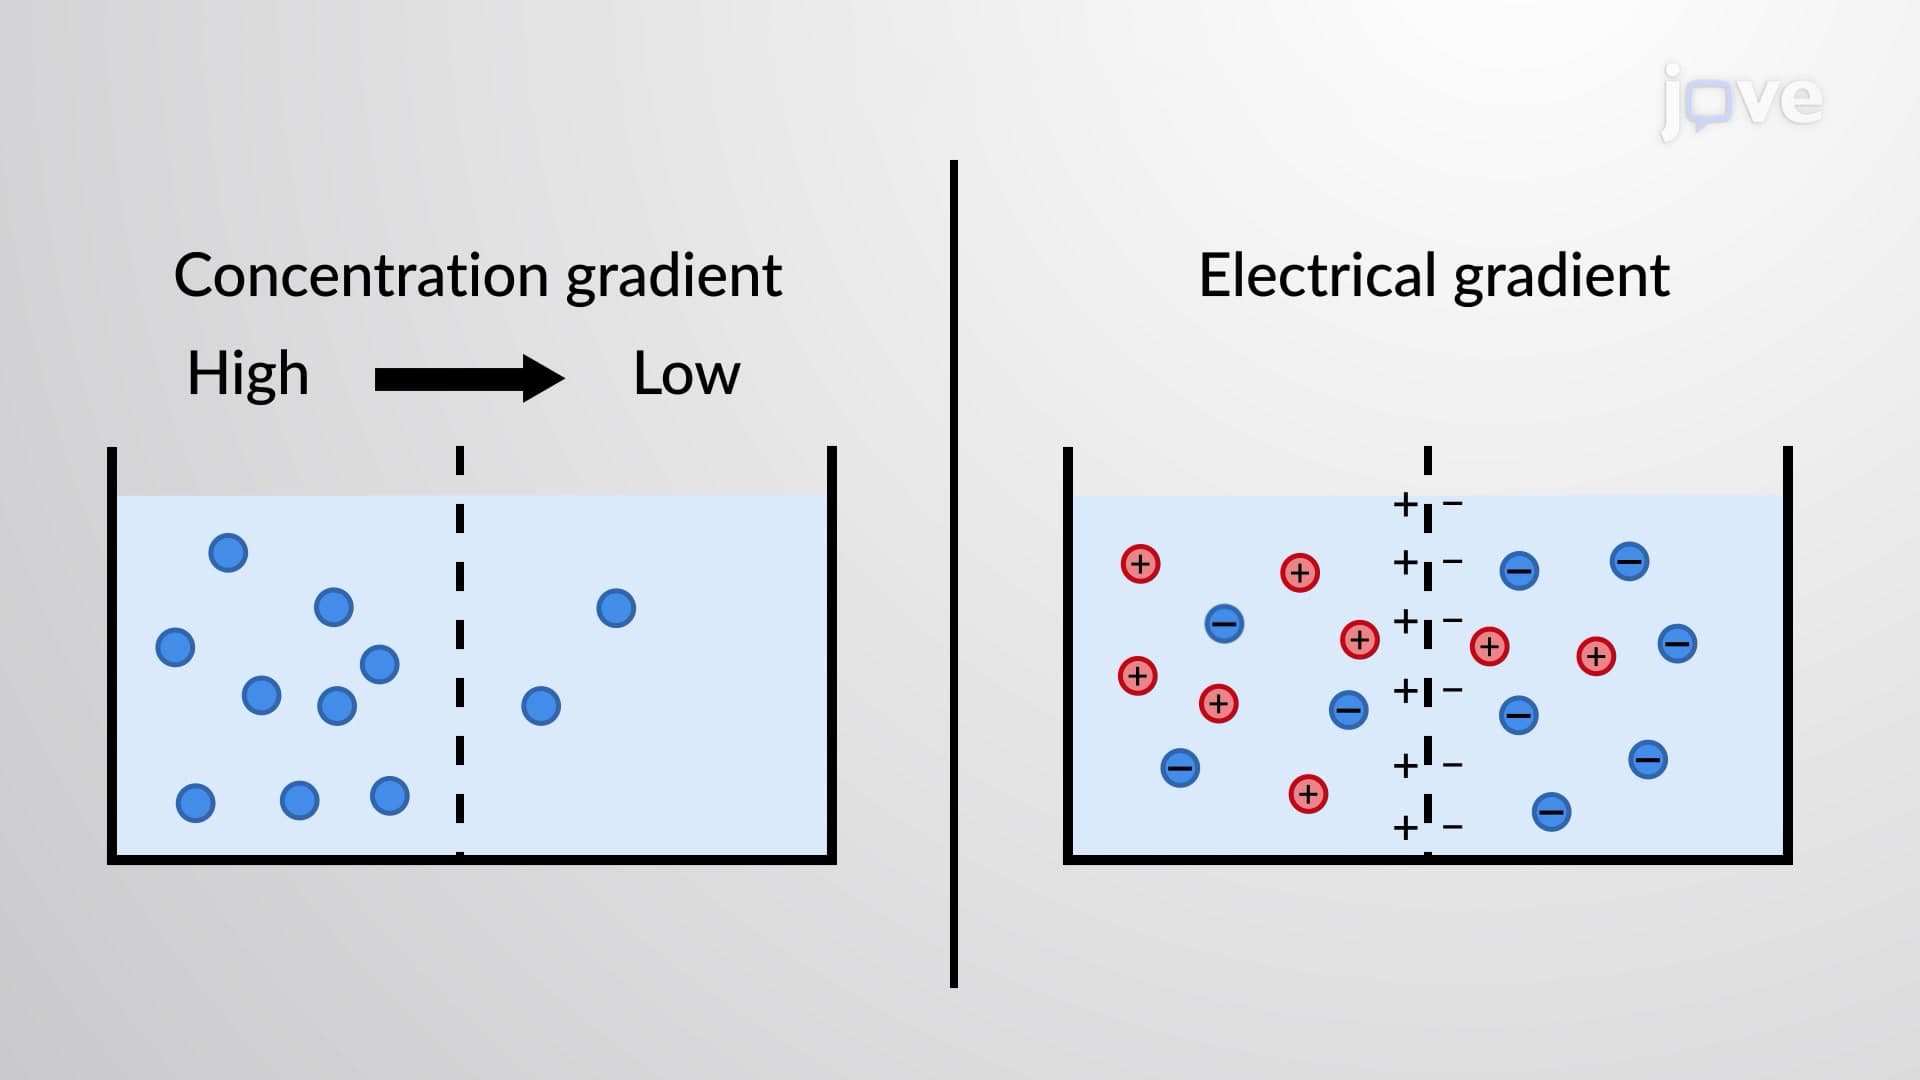
The chemical gradient relies on differences in the abundance of a substance on the outside versus the inside of a cell and flows from areas of high to low ion concentration. In contrast, the electrical gradient revolves around an...
 01:29
Cardiomyopathy V: Interprofessional Care