Related Experiment Video
Updated: Feb 1, 2026


Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Bevacizumab-associated glomerular microangiopathy
Fermin Person1, Markus M Rinschen2,3, Silke R Brix4
1Institute of Pathology and Nephropathology Section, University Hospital Hamburg Eppendorf, Hamburg, Germany.

Bevacizumab is a humanized monoclonal IgG1 antibody, which neutralizes vascular endothelial growth factor and is used for treating multiple cancer types. As a known and frequent adverse event, this therapy can lead to renal damage including proteinuria and nephrotic syndrome. In a retrospective approach, we analyzed 17 renal biopsies from patients receiving bevacizumab treatment. We observed a distinctive histopathological pseudothrombotic pattern different from the previously reported thrombotic microangiopathy. Since this pattern includes some features similar to acute and chronic thrombotic microangiopathy, focal segmental glomerulosclerosis and cryoglobulinemic membranoproliferative glomerulonephritis, biopsies with these diagnoses were included for comparison. Clinical, laboratory, light microscopic, immunohistochemical (including a proximity ligation assay), proteomic and electron microscopic features were assessed. Nephrotic syndrome was present in 15 of the 17 bevacizumab-treated patients. All 17 displayed a patchy pattern of variably PAS-positive hyaline pseudothrombi occluding markedly dilated glomerular capillaries in their biopsies. Mass spectrometry-based proteome analysis revealed a special protein pattern demonstrating some features of thrombotic microangiopathy and some of cryoglobulinemic glomerulonephritis, including a strong accumulation of IgG in the pseudothrombi. Proximity ligation assay did not show interaction of IgG with C1q, arguing for accumulation without classic pathway complement activation. In contrast to thrombi in thrombotic microangiopathy cases, the hyaline pseudothrombi did not contain clusters of CD61-positive platelets. Electron microscopy of bevacizumab cases did not show fibrin polymers or extensive loss of podocyte foot processes. Even though cases of bevacizumab-associated microangiopathy share some features with thrombotic microangiopathy, its overall histopathological pattern is quite different from acute or chronic thrombotic microangiopathy cases. We conclude that bevacizumab therapy can lead to a unique hyaline occlusive glomerular microangiopathy, likely arising from endothelial leakage followed by subendothelial accumulation of serum proteins. It can be diagnosed by light microscopy and is an important differential diagnosis in cancer patients with nephrotic syndrome.
Bevacizumab is a humanized monoclonal IgG1 antibody, which neutralizes vascular endothelial growth factor and is used for treating multiple cancer types. As a known and frequent adverse event, this therapy can lead to renal damage including proteinuria and nephrotic syndrome. In a retrospective approach, we analyzed 17 renal biopsies from patients receiving bevacizumab treatment. We observed a distinctive histopathological pseudothrombotic pattern different from the previously reported thrombotic microangiopathy. Since this pattern includes some features similar to acute and chronic thrombotic microangiopathy, focal segmental glomerulosclerosis and cryoglobulinemic membranoproliferative glomerulonephritis, biopsies with these diagnoses were included for comparison. Clinical, laboratory, light microscopic, immunohistochemical (including a proximity ligation assay), proteomic and electron microscopic features were assessed. Nephrotic syndrome was present in 15 of the 17 bevacizumab-treated patients. All 17 displayed a patchy pattern of variably PAS-positive hyaline pseudothrombi occluding markedly dilated glomerular capillaries in their biopsies. Mass spectrometry-based proteome analysis revealed a special protein pattern demonstrating some features of thrombotic microangiopathy and some of cryoglobulinemic glomerulonephritis, including a strong accumulation of IgG in the pseudothrombi. Proximity ligation assay did not show interaction of IgG with C1q, arguing for accumulation without classic pathway complement activation. In contrast to thrombi in thrombotic microangiopathy cases, the hyaline pseudothrombi did not contain clusters of CD61-positive platelets. Electron microscopy of bevacizumab cases did not show fibrin polymers or extensive loss of podocyte foot processes. Even though cases of bevacizumab-associated microangiopathy share some features with thrombotic microangiopathy, its overall histopathological pattern is quite different from acute or chronic thrombotic microangiopathy cases. We conclude that bevacizumab therapy can lead to a unique hyaline occlusive glomerular microangiopathy, likely arising from endothelial leakage followed by subendothelial accumulation of serum proteins. It can be diagnosed by light microscopy and is an important differential diagnosis in cancer patients with nephrotic syndrome.


Related Concept Videos
 01:15
Glomerular Filtration
Components of the Filtration Membrane
The filtration process involves three key layers: the glomerular endothelial cells, the basement membrane, and the podocyte-formed filtration slits.
 01:28
Glomerular Filtration Rate and its Regulation
GFR regulation involves two primary intrinsic controls: the myogenic and tubuloglomerular feedback mechanisms.
The myogenic...
 01:26
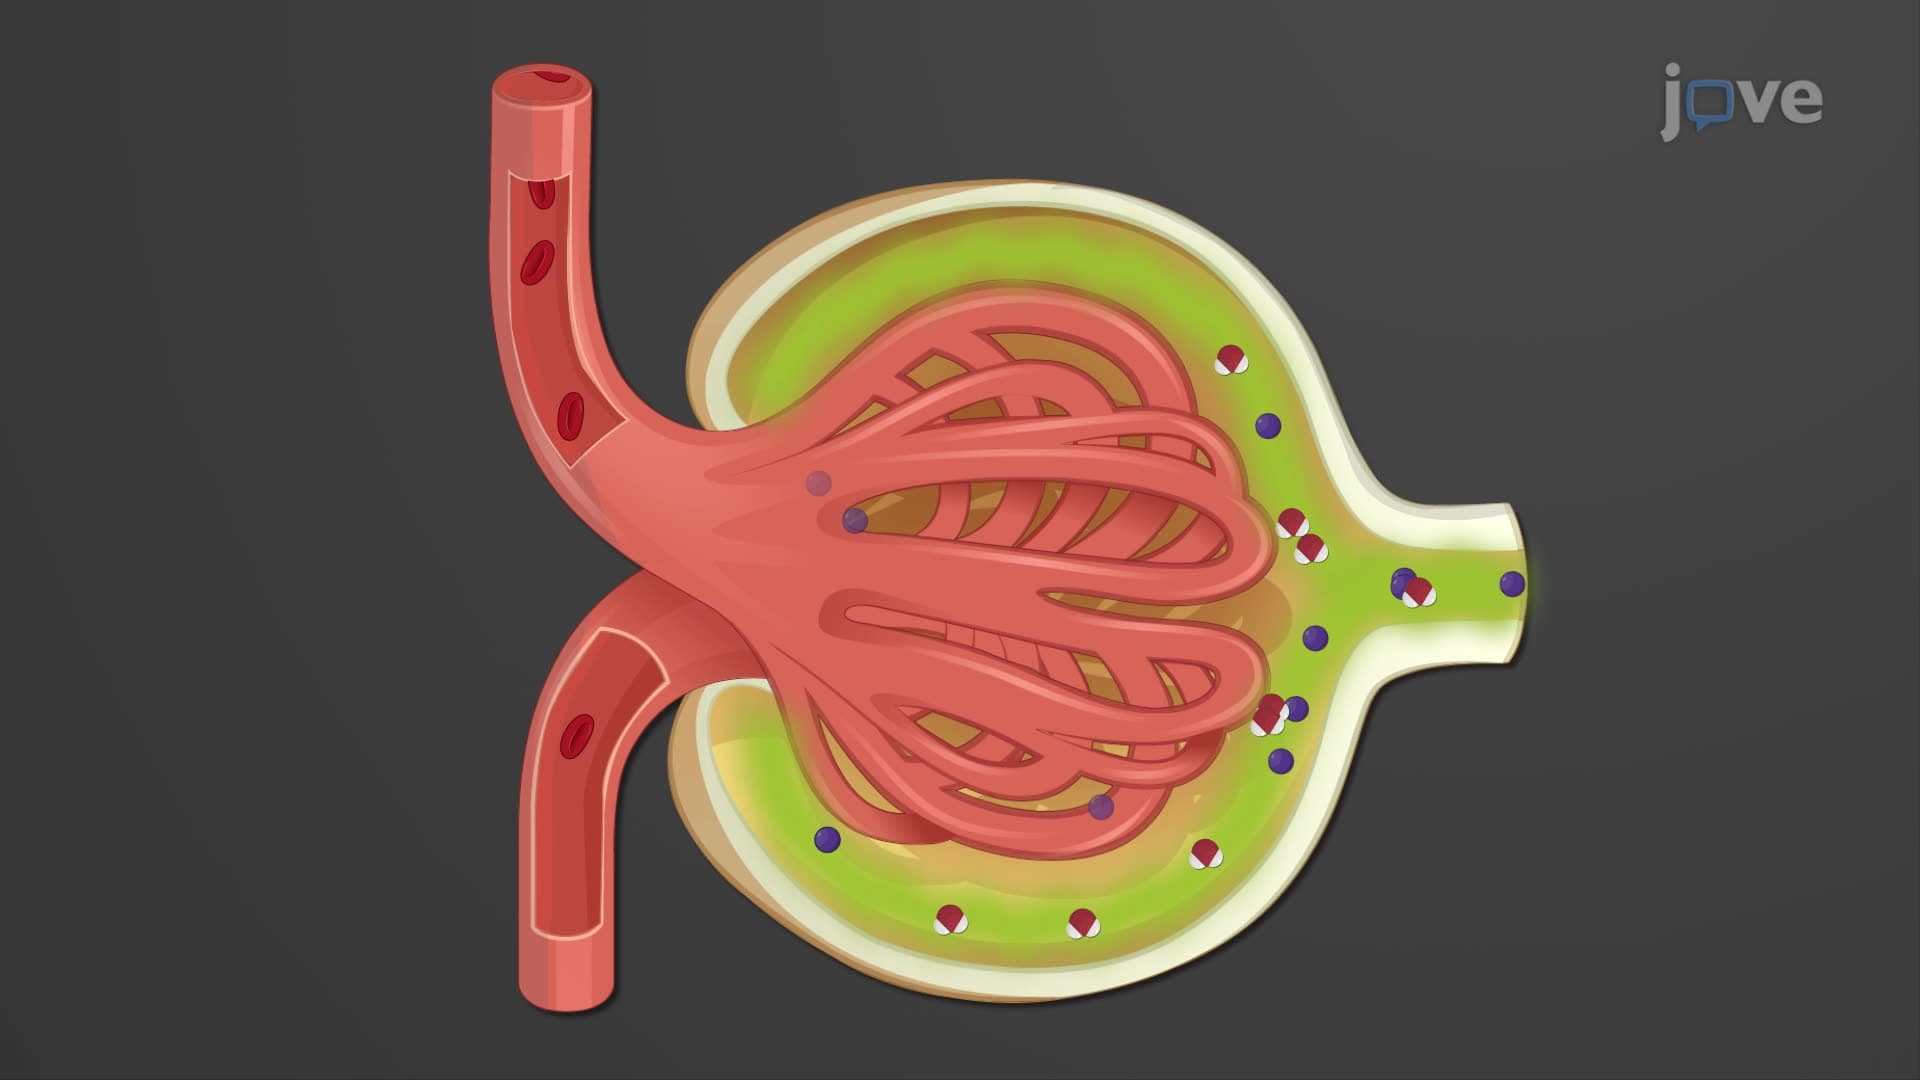
Glomerular Filtration: Net Filtration Pressure
GBHP, with an average value of 55 mmHg, promotes filtration by pushing water and solutes through the filtration membrane. This is balanced by two opposing forces: CHP, a "back pressure" exerted against the filtration membrane by fluid already in the capsular space and renal...
 01:02
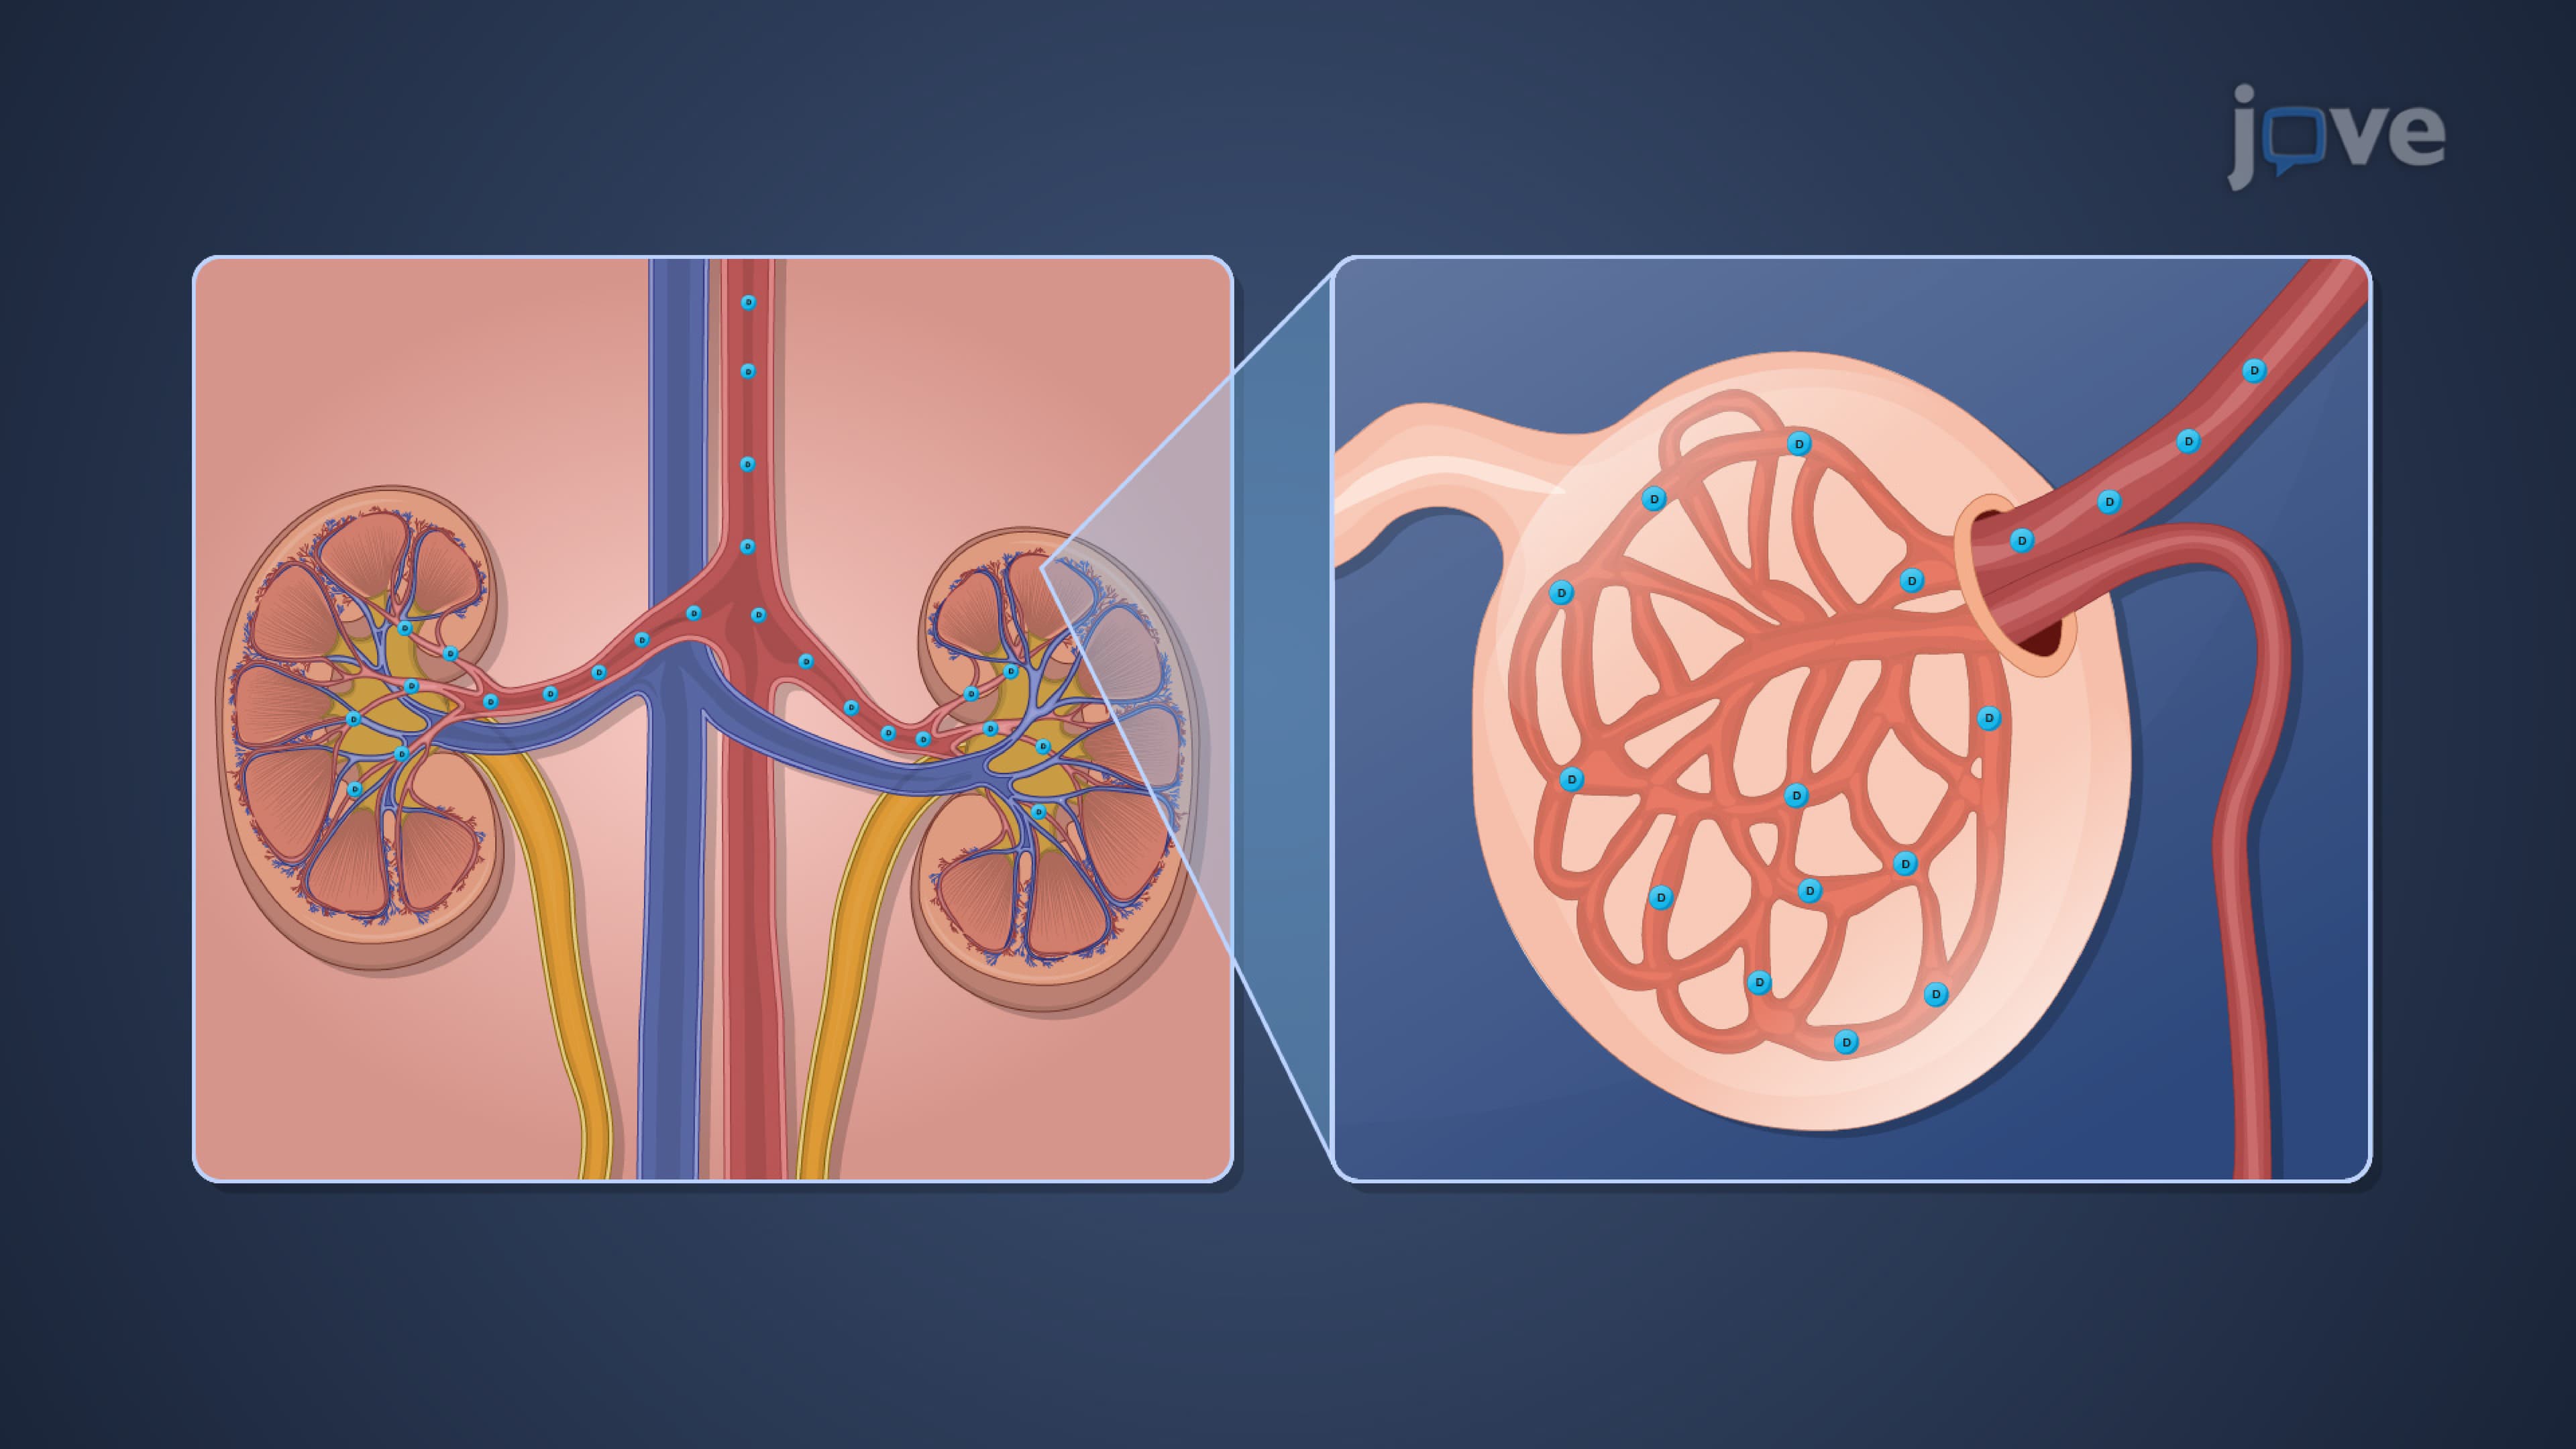
Renal Drug Excretion: Glomerular Filtration
Drugs gain access to the kidney via the renal artery, which progressively branches off into afferent arterioles....
 01:17
Drug Elimination by Renal Route: Glomerular Filtration
 01:29
Physiology of the Genitourinary System I: Renal Blood Flow and Glomerular Filtration