Related Experiment Video
Updated: Jan 31, 2026
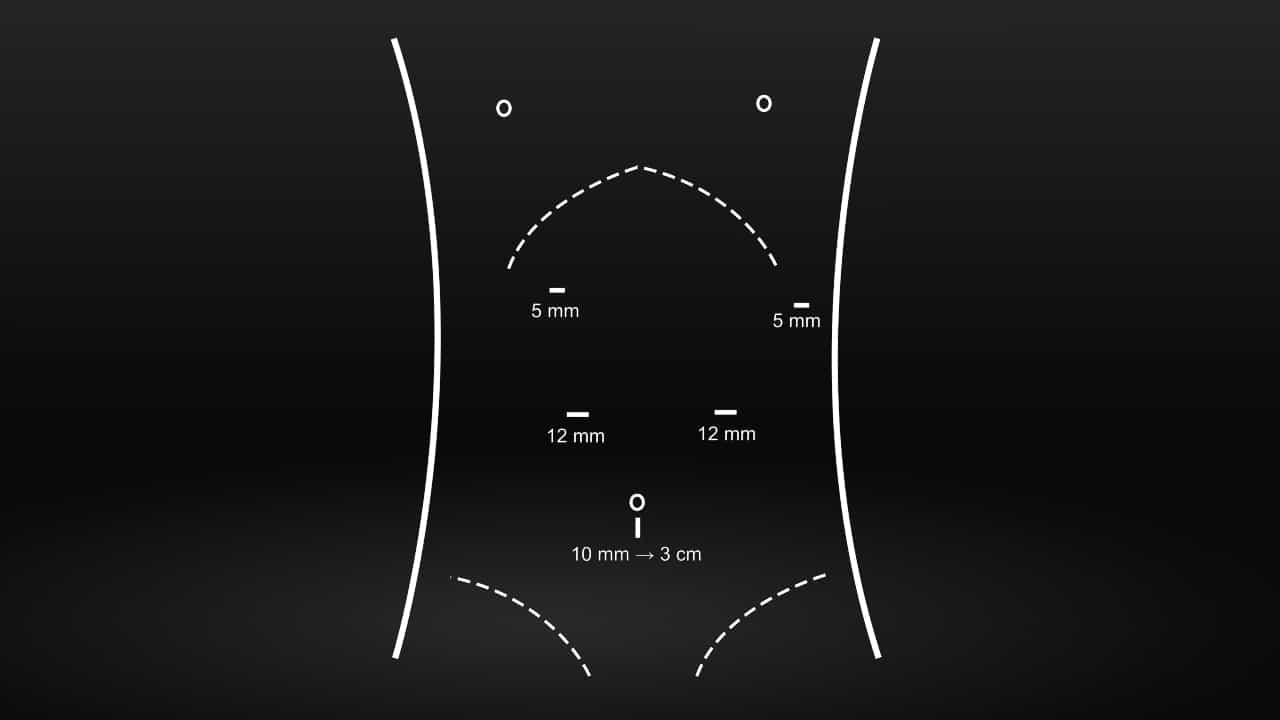
Application of Microwave Ablation in Laparoscopic Partial Splenectomy
Published on: November 15, 2024
Prediction of Technical Difficulties in Laparoscopic Splenectomy and Analysis of Risk Factors for Postoperative
Michał Wysocki1,2, Dorota Radkowiak3, Anna Zychowicz4
12nd Department of General Surgery, Jagiellonian University Medical College, 31-501 Kraków, Poland. michal92wysocki@gmail.com.

Prediction of intraoperative difficulties may be helpful in planning surgery; however, few studies explored this issue in laparoscopic splenectomy (LS). We performed retrospective analysis of consecutive 468 patients undergoing LS from 1998 to 2017 (295 women; median age 47 years). The patients were divided into difficult LS and control groups. The inclusion criteria for difficult LS were operative time ≥mean + 2SD; intraoperative blood loss ≥500 mL, intraoperative adverse events (IAE), conversion. Primary outcomes were risk factors for difficult splenectomy and secondary outcomes for perioperative morbidity. Fifty-six patients were included in the difficult LS group (12%). Spleens ≥19 cm and higher participation of younger surgeons in consecutive years were predictive for difficult splenectomy. Age ≥53 years and diagnosis other than idiopathic thrombocytopenic purpura (ITP) were independent risk factors of spleen ≥19 cm. The perioperative morbidity was 8.33%; its OR was increased only by blood loss and IAEs. Only blood loss significantly increased serious morbidity. Male sex, spleens ≥19 cm, and IAEs were independent risk factors for intraoperative hemorrhage. Spleen length ≥19 cm was a risk factor for difficult LS and intraoperative hemorrhage. Diagnoses other than ITP in patients aged ≥53 years with ≥19 cm spleens are predictive for intraoperative difficulties and perioperative complications.
Prediction of intraoperative difficulties may be helpful in planning surgery; however, few studies explored this issue in laparoscopic splenectomy (LS). We performed retrospective analysis of consecutive 468 patients undergoing LS from 1998 to 2017 (295 women; median age 47 years). The patients were divided into difficult LS and control groups. The inclusion criteria for difficult LS were operative time ≥mean + 2SD; intraoperative blood loss ≥500 mL, intraoperative adverse events (IAE), conversion. Primary outcomes were risk factors for difficult splenectomy and secondary outcomes for perioperative morbidity. Fifty-six patients were included in the difficult LS group (12%). Spleens ≥19 cm and higher participation of younger surgeons in consecutive years were predictive for difficult splenectomy. Age ≥53 years and diagnosis other than idiopathic thrombocytopenic purpura (ITP) were independent risk factors of spleen ≥19 cm. The perioperative morbidity was 8.33%; its OR was increased only by blood loss and IAEs. Only blood loss significantly increased serious morbidity. Male sex, spleens ≥19 cm, and IAEs were independent risk factors for intraoperative hemorrhage. Spleen length ≥19 cm was a risk factor for difficult LS and intraoperative hemorrhage. Diagnoses other than ITP in patients aged ≥53 years with ≥19 cm spleens are predictive for intraoperative difficulties and perioperative complications.
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 02:27
Predicting Molecular Geometry
 01:24
Hemodialysis II: Procedure and Complications
 01:12
Relative Risk
 01:03
Prediction Intervals
However, the point estimate is most likely not the exact value of the population parameter, but close to it. After calculating point estimates, we construct interval estimates, called confidence intervals or prediction intervals. This prediction interval comprises a range of values unlike the point estimate and is a better predictor of the observed sample value, y.
 01:30
Pneumonia III: Complications and Assessment