Related Experiment Video
Updated: Jan 31, 2026

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Intraoperative pyloric botulinum toxin injection during Ivor-Lewis gastroesophagectomy to prevent delayed gastric
J C Tham1, M Nixon1, A V Ariyarathenam1
1Peninsula Oesophago-gastric Centre, University Hospitals Plymouth NHS Trust, united Kingdom.

Abstract:
Delayed gastric emptying (DGE) is a common morbidity that affects 10%-50% of Ivor-Lewis gastroesophagectomy (ILGO) patients. DGE management is variable with no gold standard prevention or treatment. We conducted a study to assess the effectiveness of intraoperative pyloric botulinum toxin injection in preventing DGE. All patients undergoing an ILGO for curative intent, semi-mechanical anastomosis, and enhanced recovery between 1st December 2011 and 30th June 2017 were included. Patients with pyloroplasties were excluded and botulinum toxin was routinely given from the 2nd April 2016. We compared botulinum toxin injection (BOTOX) against no intervention (NONE) for patient demographics, adjuvant therapy, surgical approach, DGE incidence, length of stay (LOS), and complications. Additionally, we compared pneumonia risk, anastomotic leak rate, and LOS in DGE versus non-DGE patients. DGE was defined using nasogastric tube input/output differences and chest X-ray appearance according to an algorithm adopted in our unit, which were retrospectively applied. There were 228 patients: 65 (28.5%) received botulinum toxin and 163 (71.5%) received no intervention. One hundred twenty-four (54.4%) operations were performed laparoscopically, of which 11 (4.8%) were converted to open procedures, and 104 (45.6%) were open operations. DGE incidence was 11 (16.9%) in BOTOX and 29 (17.8%) in NONE, P = 0.13. Medical management was required in 14 of 228 (6.1%) cases: 3 (4.6%) in BOTOX and 11 (4.8%) in NONE. Pyloric dilatation was required in 26 of 228 (11.4%): 8 of 65 (12.3%) in the BOTOX and 18 of 163 (11.0%) in NONE. There were no significant differences between groups and requirement for intervention, P = 0.881. Overall median LOS was 10 (6.0-75.0) days: 9 (7.0-75.0) in BOTOX and 10 (6.0-70.0) in NONE, P = 0.516. In non-DGE versus DGE patients, median LOS was 9 (6-57) versus 14 (7-75) days (P < 0.0001), pneumonia incidence of 27.7% versus 30.0% (P = 0.478), and anastomotic leak rate of 2.1% versus 10.0% (P = 0.014). Overall leak rate was 3.5%. Overall complication rate was 67.1%, including minor/mild complications. There were 43 of 65 (66.2%) in BOTOX and 110 of 163 (67.5%) in NONE, P = 0.482. In-hospital mortality was 1 (0.44%), 30-day mortality was 2 (0.88%), 90-day mortality was 5 (2.2%), and there were no 30-day readmissions. Intraoperative pyloric botulinum toxin injections were ineffective in preventing DGE (BOTOX vs. NONE: 16.9% vs. 17.8%) or reducing postoperative complications. DGE was relatively common (17.5%) with 11.4% of patients requiring postoperative balloon dilatation. DGE also resulted in prolonged LOS (increase from 9 to 14 days) and significant increase in leak rate from 2.1% to 10.0%. A better understanding of DGE will guide assessment, investigation, and management of the condition.


Related Concept Videos
 01:16
Gastric Emptying
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 02:33
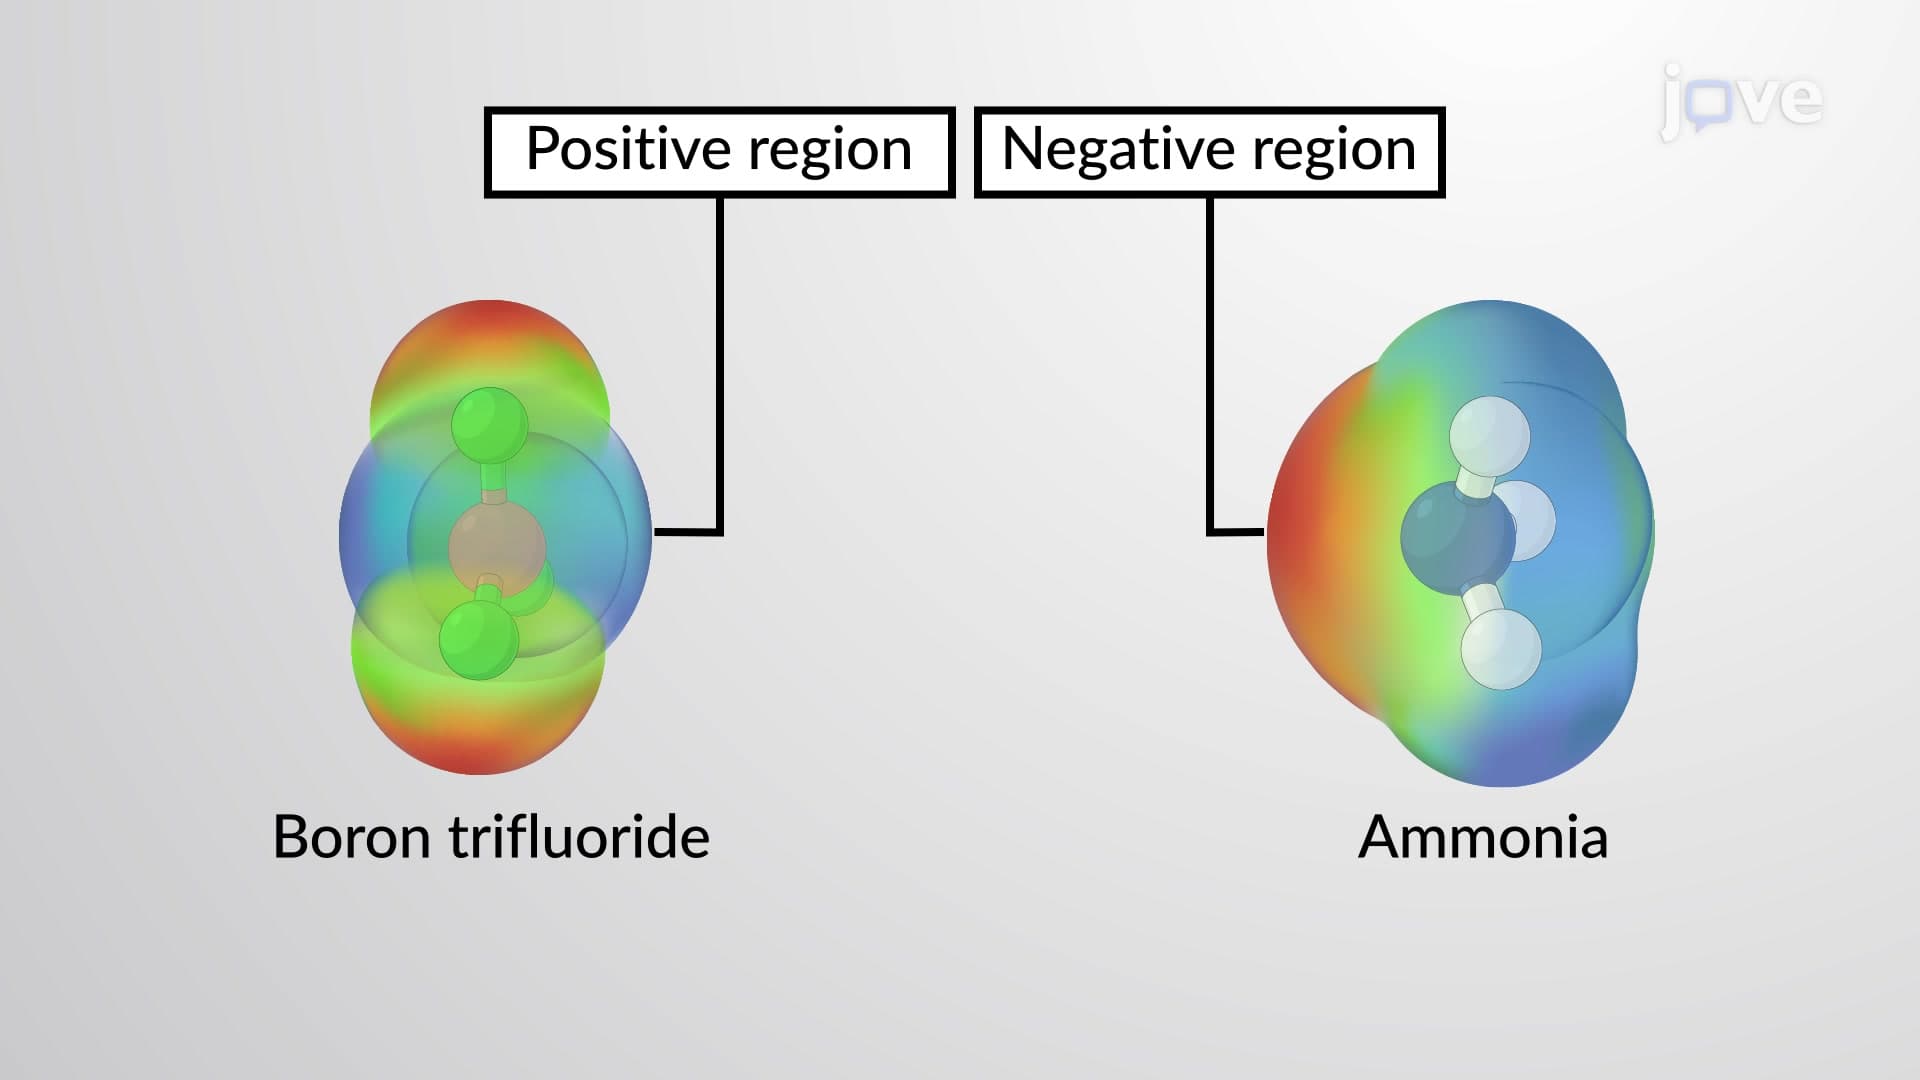
Lewis Acids and Bases
A coordinate covalent bond (or dative bond) occurs when one of the atoms in the bond provides both bonding electrons. For example, a coordinate covalent bond occurs when a water molecule combines with a hydrogen ion to form a hydronium ion. A coordinate covalent bond also results when...
 02:16
Lewis Acids and Bases
 02:36
Lewis Symbols and the Octet Rule
 02:46
Covalent Bonding and Lewis Structures