Related Experiment Video
Updated: Jan 31, 2026
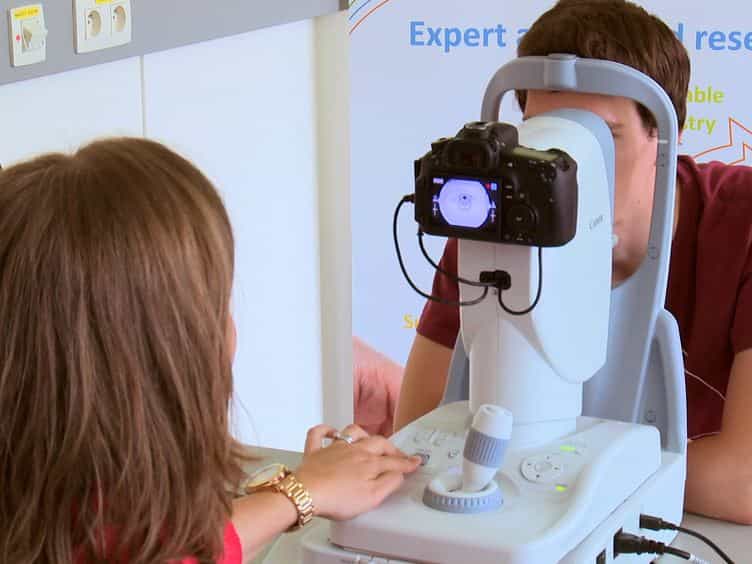
Fundus Photography as a Convenient Tool to Study Microvascular Responses to Cardiovascular Disease Risk Factors in Epidemiological Studies
Published on: October 22, 2014
Long-Term Association of Low-Density Lipoprotein Cholesterol With Cardiovascular Mortality in Individuals at Low
Shuaib M Abdullah1,2, Laura F Defina3, David Leonard3
1Department of Internal Medicine, University of Texas Southwestern Medical Center, Dallas (S.M.A., A.R., D.K.M., J.A.D., S.M.G., J.D.B., A.K.).

Background:
The associations of low-density lipoprotein cholesterol (LDL-C) with cardiovascular disease (CVD) and coronary heart disease mortality in an exclusively low estimated 10-year risk group are not well delineated. We sought to determine the long-term associations of various LDL-C and non-high-density lipoprotein cholesterol (HDL-C) thresholds and CVD and coronary heart disease mortality in a large, low 10-year risk cohort.
Methods:
The study sample included participants of the CCLS (Cooper Center Longitudinal Study) without a history of CVD or diabetes mellitus and defined as low risk (<7.5%) for 10-year atherosclerotic CVD events at baseline based on Pooled Cohort Risk Assessment Equations. The associations of fasting LDL-C and non-HDL-C with CVD mortality were tested with Cox proportional hazards models.
Results:
In 36 375 participants (72% men, median age 42) followed for a median of 26.8 years, 1086 CVD and 598 coronary heart disease deaths occurred. Compared with LDL-C <100 mg/dL, LDL-C categories 100 to 129 mg/dL, 130 to 159 mg/dL, 160 to 189.9 mg/dL, and ≥190 mg/dL were associated with a significantly higher risk of CVD death, with hazard ratios of 1.4 (95% CI, 1.1-1.7), 1.3 (95% CI, 1.1-1.6), 1.9 (95% CI, 1.5-2.4), and 1.7 (95% CI, 1.3-2.3), and mean reductions in years free of CVD death of 1.8, 1.1, 4.3, and 3.9, respectively. After adjustment for atherosclerotic CVD risk factors, LDL-C categories 160 to 189 mg/dL and ≥190 mg/dL remained independently associated with CVD mortality, with hazard ratios of 1.7 (95% CI, 1.4-2.2) and 1.5 (95% CI, 1.2-2.1), respectively. In multivariable-adjusted models using non-HDL-C <130 mg/dL as the reference, non-HDL-C 160 to 189 mg/dL, 190 to 219 mg/dL, and ≥220 mg/dL were significantly associated with CVD death, with hazard ratios of 1.3 (95% CI, 1.1-1.6), 1.8 (95% CI, 1.4-2.2), and 1.5 (95% CI, 1.2-2.0), respectively. Restricting the cohort to those with 10-year risk <5% did not diminish the associations of LDL-C and non-HDL-C with CVD mortality.
Conclusions:
In a low 10-year risk cohort with long-term follow-up, LDL-C and non-HDL-C ≥160 mg/dL were independently associated with a 50% to 80% increased relative risk of CVD mortality. These findings may have implications for future cholesterol treatment paradigms.

Related Concept Videos
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...
 01:14
Overview of the Cardiovascular System
Heart
The heart is the central pump of the cardiovascular system that circulates blood throughout the body. It comprises two atria receiving the blood and two ventricles pumping blood out of the heart. Their rhythmic contractions, called heartbeats, ensure that blood flow remains continuous.
Blood Vessels
Blood...
 01:27
Regulation of the Cardiovascular System
The regulation of the cardiovascular system involves the autonomic nervous system (ANS), baroreceptors, and chemoreceptors, ensuring that heart rate and blood pressure are appropriately modulated in response to varying physiological demands.
The ANS comprises two main divisions: the sympathetic and parasympathetic nervous systems. The sympathetic nervous system enhances...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:29
Assessment of the Cardiovascular System II: Inspection
Head and Neck
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.