Related Experiment Video
Updated: Jan 31, 2026

Urethral Stricture Induction Followed by Buccal Mucosa Graft Urethroplasty in a Rat Model
Published on: April 28, 2023
The Benefits of Using a Small Caliber Ureteroscope in Evaluation and Management of Urethral Stricture
Walid Shahrour1, Pankaj Joshi2, Craig B Hunter2
1Thunder Bay Regional Health Sciences Center, Northern Ontario School of Medicine, Division of Clinical Sciences, Thunder Bay, Canada.

Introduction And Objective:
The proper evaluation of urethral strictures is an essential part of the surgical planning in urethral reconstruction. The proper evaluation of the stricture can be challenging in certain situations, especially when the meatus is involved. We propose that the use of a small caliber ureteroscope (4.5 Fr and 6.5 Fr) can offer additional help and use for the surgical planning in urethroplasty.
Methods:
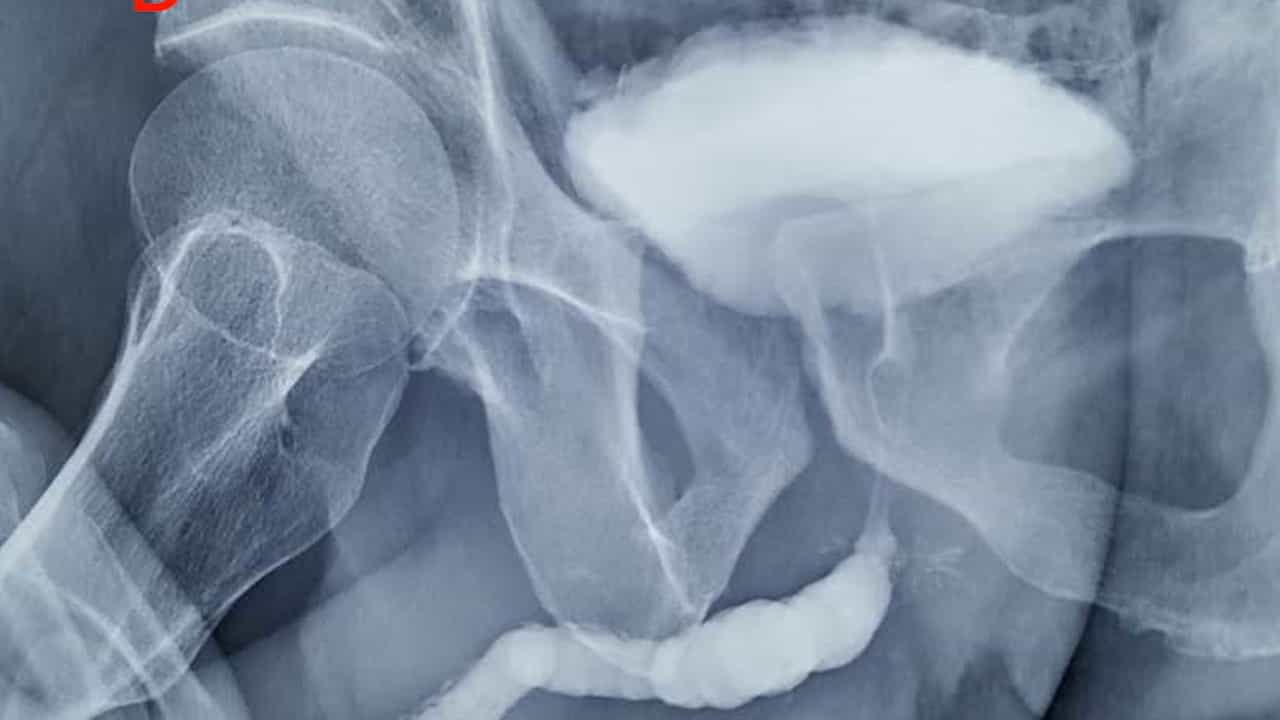
We prospectively collected data on 76 patients who underwent urethroplasties in Kulkarni Reconstructive Urology Center, Pune, India and Thunder Bay Regional Health Sciences Center, Thunder Bay, Canada. Patients had retrograde and micturition urethrograms performed preoperatively. The stricture was assessed visually using a 6.5 Fr ureteroscope. If the stricture was smaller than 6.5 Fr, we attempted using the 4.5 Fr ureteroscope. In nonobliterated strictures, we attempted bypassing the stricture making sure not to dilate the stricture. A glide wire would be passed to the bladder under vision. Stricture length, tissue quality, presence of other proximal strictures, false passages, and bladder tumors or stones would be assessed visually. If the penile stricture was near obliterative (smaller than 4.5 Fr caliber), a two-staged procedure is elected to be performed. For proximal bulbar strictures, if the urethral caliber is less than 4.5 Fr and the stricture length is less than 1 cm, we perform a nontransecting anastomotic urethroplasty (NTAU). If the stricture length is >1 cm, we perform a double-face augmented urethroplasty (DFAU). If the urethral caliber is >4.5 Fr and particularly those who are sexually active, ventral inlay with buccal mucosal grafts (BMGs) is performed. In mid to distal bulbar strictures, if the urethral caliber is >4.5 Fr, our procedure of choice is dorsal onlay with BMG. For those with urethral caliber <4.5 Fr and a stricture less than 1 cm, we perform a NTAU. For strictures longer than 1 cm, we perform a DFAU. With the exception of trauma, we very rarely transect the urethra. For panurethral strictures, we almost exclusively perform Kulkarni one-sided dissection.
Results:
Urethroscopy was performed in 76 patients who presented for urethroplasty from July 2014 to September 2014 (in Pune) and between April 2016 and September 2017 (in Thunder Bay). Bypassing the stricture was achieved in 68 patients (89%) while it was unsuccessful in 8 patients (11%). In all unsuccessful urethroscopies, the stricture was near obliterative <4.5 Fr. Our surgical planning changed in (13) 17% of the cases. Out of 43 bulbar strictures, the decision was changed in (9) 21% where we performed 4 DFAU, 3 AAU (augmented anastomotic urethroplasty), and 2 EAU (end anastomotic urethroplasty). In 13 penile strictures, we opted for staged urethroplasty including 3 Johansons and 1 first-stage Asopa in 30.7%. In 20 panurethral urethroplasties, 1 patient (5%) had a urethral stone found in a proximal portion of the bulbar urethra distal to a stricture ring that was removed using an endoscopic grasper.
Conclusion:
The use of the small caliber ureteroscope can help in evaluation of the stricture caliber, length, and tissue quality. The scope can also aid in placing a guide wire, evaluating the posterior urethra, and screening for urethral or bladder stones. It can also improve the preoperative patient counselling and avoid unwanted surprises.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 03:37
Iatrogenic Injury Recapitulated: Electroexcision Technique for Urethral Stricture Modeling in Rats
Published on: October 11, 2024
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Benefits of Self-Esteem
 01:26
Tonsillitis II: Management
 01:29
Impression Management Techniques I: Managing Appearances
 01:19
Managing Impressions