Related Experiment Video
Updated: Jan 31, 2026


Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Major Bleeding Rates in Atrial Fibrillation Patients on Single, Dual, or Triple Antithrombotic Therapy
Nienke van Rein1,2,3, Uffe Heide-Jørgensen3, Willem M Lijfering1,2,4
1Department of Thrombosis and Hemostasis, Leiden University Medical Center, The Netherlands (N.v.R., W.M.L.).

Insights
Triple therapy for atrial fibrillation significantly increases major bleeding risk, especially in elderly patients or those with high CHA2DS2-VASc scores. Careful consideration of triple antithrombotic therapy is warranted in these high-risk groups.
Area of Science:
- Cardiology
- Pharmacology
- Public Health
Background:
- Atrial fibrillation (AF) management often involves anticoagulants and antiplatelet agents.
- Data on bleeding risks with combination antithrombotic therapy in high-risk AF patients are limited.
Purpose of the Study:
- To evaluate major bleeding rates in elderly AF patients (≥50 years) across various antithrombotic treatment strategies.
- To compare bleeding risks associated with monotherapy, dual therapy, and triple therapy.
Main Methods:
- Nationwide cohort study of Danish AF patients using prescription data.
- Incidence rates (IRs) and hazard ratios (HRs) of major bleeding were estimated.
- Analyses stratified by treatment modality, age, CHA2DS2-VASc score, and comorbidities.
Main Results:
- Triple therapy demonstrated significantly higher major bleeding rates compared to monotherapy or dual therapy.
- Patients on triple therapy aged >90 years or with CHA2DS2-VASc score >6 had very high bleeding rates (17.6-22.8/100 PYs).
- Vitamin K antagonist triple therapy showed an HR of 3.73, and direct oral anticoagulant triple therapy showed an HR of 2.28 for major bleeding versus VKA monotherapy.
Conclusions:
- Triple antithrombotic therapy in AF patients is associated with substantially increased major bleeding risk.
- High bleeding rates in elderly patients (>90 years), those with high CHA2DS2-VASc scores (>6), or prior bleeding history necessitate cautious use of triple therapy.
Background:
Patients with atrial fibrillation generally require anticoagulant therapy and, at times, therapy with additional platelet aggregation inhibitors. Data are scarce on bleeding rates in high-risk groups receiving combination therapy, such as the elderly or patients with a high CHA2DS2-VASc score.
Methods:
We conducted a nationwide cohort study of Danish patients with atrial fibrillation ≥50 years of age. Treatments were ascertained from a prescription database. These included no anticoagulant treatment, and treatment with vitamin K antagonists, direct oral anticoagulants, platelet inhibitors, and combinations of antithrombotic drugs. Incidence rates (IRs) of major bleeding and hazard ratios were estimated overall, and also stratified by treatment modality, age, CHA2DS2-VASc score, and comorbidity. Major bleeding was defined as bleeding requiring hospitalization or causing death.
Results:
We identified 272 315 patients with atrial fibrillation. Median age was 75 years (interquartile range, 67-83) and 47% were women. Over a total follow-up period of 1 373 131 patient-years (PYs), 31 459 major bleeds occurred (IR 2.3/100 PYs; 95% CI, 2.3-2.3/100 PYs). In comparison with vitamin K antagonist monotherapy, adjusted hazard ratios of major bleeding were 1.13 (95% CI, 1.06-1.19) for dual antiplatelet therapy, 1.82 (95% CI, 1.76-1.89) for therapy with a vitamin K antagonist and an antiplatelet drug, 1.28 (95% CI, 1.13-1.44) for therapy of a direct oral anticoagulant with an antiplatelet drug, 3.73 (95% CI, 3.23-4.31) for vitamin K antagonist triple therapy, and 2.28 (95% CI, 1.67-3.12) for direct oral anticoagulant triple therapy. Subgroup analyses showed similar patterns. The IR for major bleeding was 10.2/100 PYs among patients receiving triple therapy. Very high major bleeding rates occurred among patients on triple therapy aged >90 years (IR 22.8/100 PYs) or with a CHA2DS2-VASc score >6 (IR 17.6/100 PYs) or with a history of major bleeding (IR 17.5/100 PYs).
Conclusions:
Patients with atrial fibrillation on triple therapy experienced high rates of major bleeding in comparison with patients on dual therapy or monotherapy. The high bleeding rates observed in patients on triple therapy >90 years of age or with a CHA2DS2-VASc score >6 or with a history of a major bleeding warrants careful consideration of such therapy in these patients.


Related Concept Videos
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining,...
03:03Amyloid Fibrils
 01:22
Bleeding in Fresh Concrete
Bleeding can cause several issues in the concrete structure. Sometimes, the rising water gets trapped beneath large aggregate...
 01:11
Fibril-associated Collagen
For example, the type II collagen fibrils in cartilage have covalently bound type IX fibril-associated collagens at regular intervals. Other types of fibril-associated collagens are...
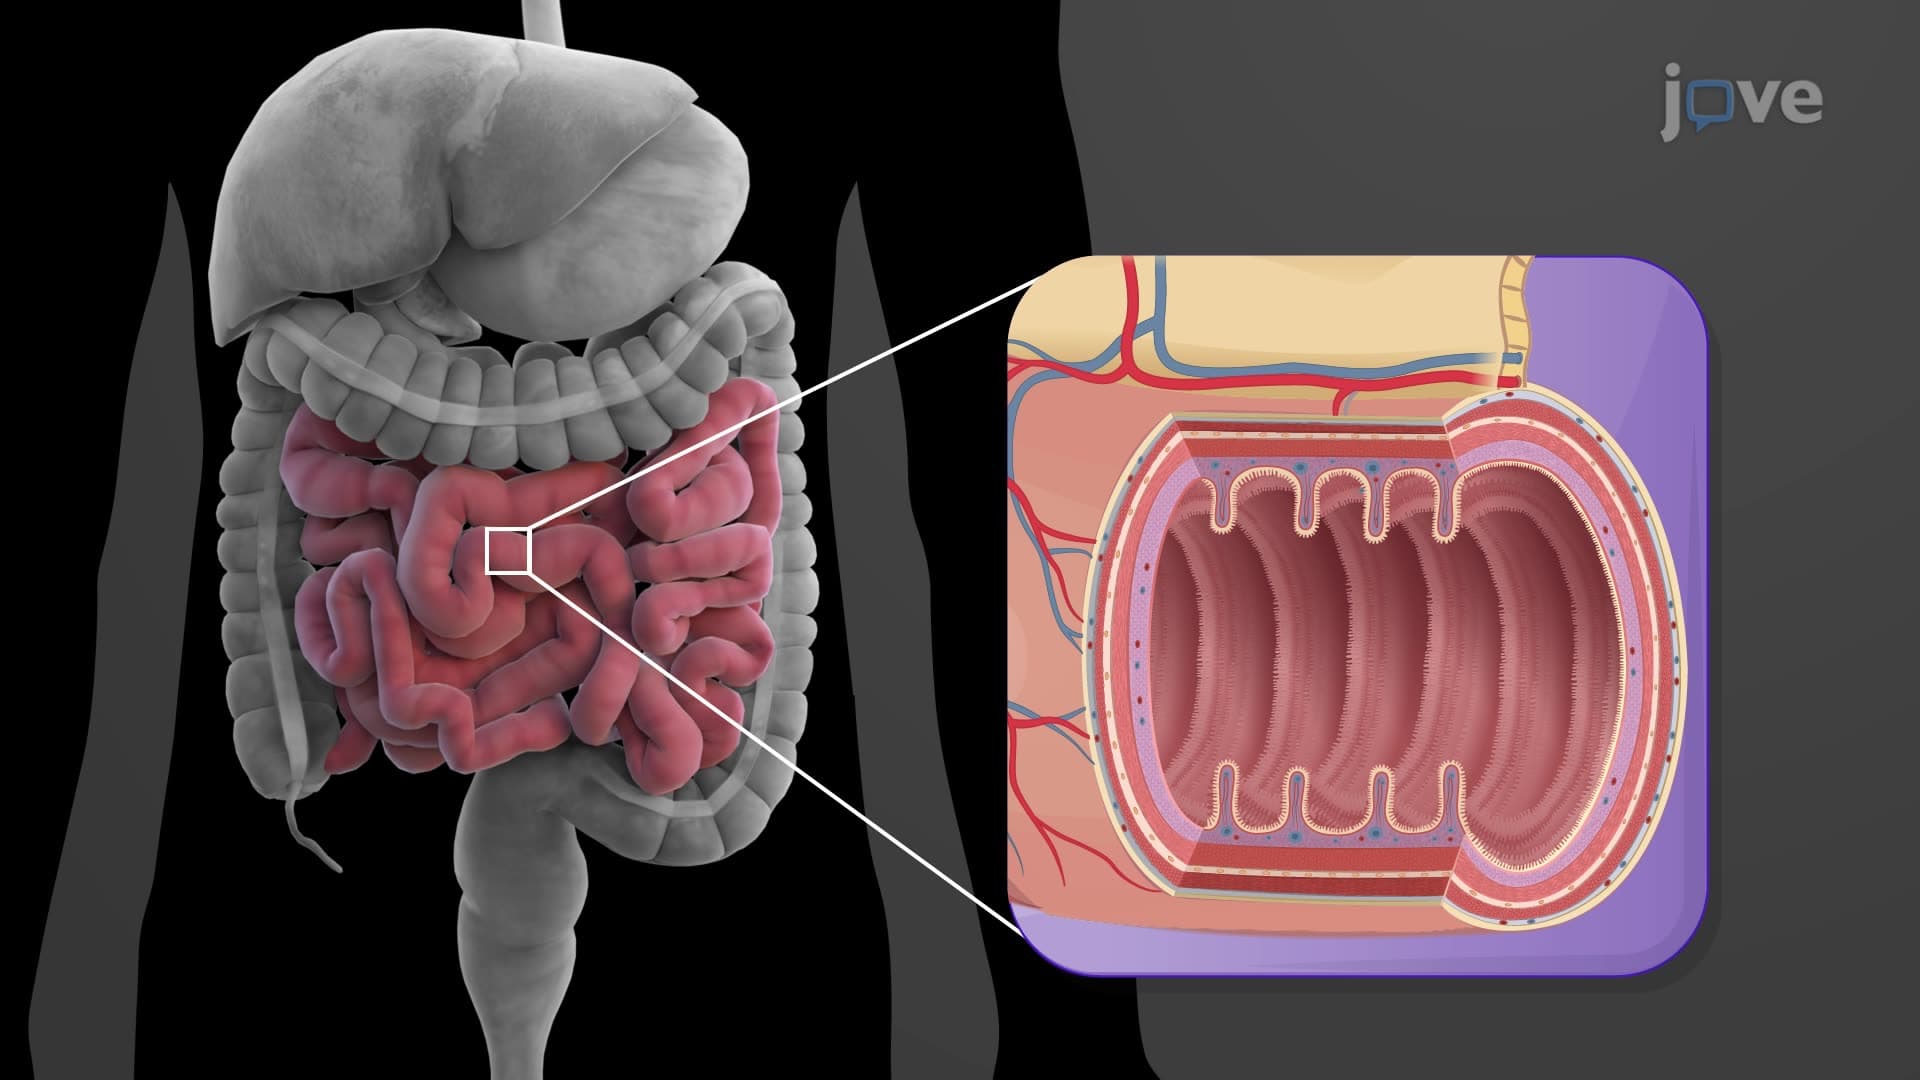 01:19
Major Organs of the Digestive System
Gastrointestinal tract:
 01:27
Major Hormones and Their Functions
Oxytocin, produced in the hypothalamus and released by the pituitary gland, plays a role in social bonding, childbirth, and...