Related Experiment Video
Updated: Jan 31, 2026
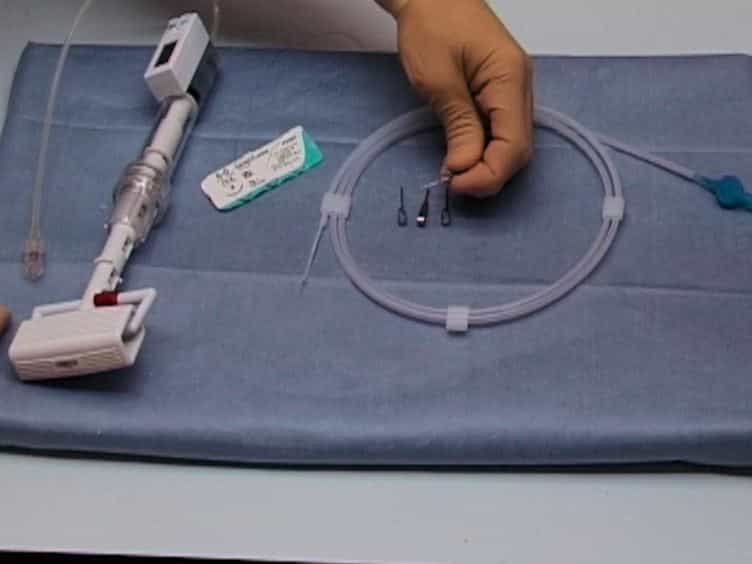
A New Murine Model of Endovascular Aortic Aneurysm Repair
Published on: July 7, 2013
Derivation and validation of thoracic sarcopenia assessment in patients undergoing thoracic endovascular aortic
Annalise M Panthofer1, Sydney L Olson1, Donald G Harris1
1Division of Vascular Surgery, University of Wisconsin School of Medicine and Public Health, Madison, Wisc.

Objective:
Sarcopenia, as assessed by computed tomography (CT)-based measurements of muscle mass, is an objective and patient-specific indicator of frailty, which is an important predictor of operative morbidity and mortality. Studies to date have primarily focused on psoas-defined sarcopenia, which may not be valid among patients with thoracic aortic disease. Using psoas sarcopenia as the reference for sarcopenia, the purpose of this study was to create and to validate a new thoracic-level method of measuring sarcopenia as a novel method to assess frailty among patients undergoing thoracic endovascular aortic repair.
Methods:
Prospectively collected data of patients undergoing thoracic endovascular aortic repair for thoracic aortic dissection, aneurysm, or injury using a conformable thoracic graft were reviewed. Patients with preoperative abdominal and thoracic CT imaging were included. Thoracic muscle mass was measured on axial images at the T12 level using our newly established standardized computer-assisted protocol. Psoas sarcopenia was measured at the L3 level using standard methods. Optimal sex-specific diagnostic T12 measurements were determined by receiver operating characteristic (ROC) curve analysis. A subset of scans were reviewed in duplicate by two trained observers and intraobserver and interobserver reliability tested by intraclass correlation coefficient. Agreement between T12 and L3 sarcopenia was tested by Cohen κ (scale, 0-1).
Results:
There were 147 patients included for analysis, including 34 dissection, 80 trauma, and 33 aneurysm patients. ROC curve analysis yielded sarcopenic cutoff values of 106.00 cm2/m2 for women and 110.00 cm2/m2 for men at the T12 level. Based on ROC curve analysis, overall accuracy of T12 measurements was high (area under ROC curve, 0.91 for men and 0.90 for women). Quantitative interobserver and intraobserver reliability yielded excellent intraclass correlation coefficient values (>0.95). Qualitative interobserver reliability yielded nearly perfect Cohen κ values (>0.85). Qualitative intraobserver reliability of calculating sarcopenia at both the T12 and L3 levels was fair for both readers (0.361 and 0.288). There was additionally a general correlation between changes in muscle area at L3 with changes at T12 during 48 months.
Conclusions:
Thoracic sarcopenia can be readily and reliably reproduced from CT-derived measurement of T12-level muscle area. This approach may be used as an alternative method to objectively define sarcopenia in patients without abdominal CT imaging. Future studies to assess the predictability of thoracic vs abdominal sarcopenia on postoperative outcomes will enhance the utility of these tools.

Related Concept Videos
 01:15
Thoracic Aorta
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:29
Reliability and Validity
 01:36
Mismatch Repair