Related Experiment Video
Updated: Jan 31, 2026

Author Spotlight: A Single-Entry Point Endoscopic Intraventricular Approach for Third Ventriculostomy and Pineal Biopsy
Published on: June 28, 2024
Unedited microneurosurgery of a high-grade pineal parenchymal tumor of intermediate differentiation
Joham Choque-Velasquez1, Juha Hernesniemi2
1Department of Neurosurgery, Helsinki University Hospital, Helsinki, Finland.

Background:
WHO Grade II-III pineal parenchymal tumors of intermediate differentiation (PPTIDs) were included in the 2007 World Health Organization Classification of Central Nervous System Tumors as pineal parenchymal tumors between pineocytomas and pineoblastomas. PPTIDs comprise more than 20-60% of all pineal parenchymal tumors (PPT) s and are characterized by moderately high cellularity, mild-to-moderate nuclear atypia, and low-to-moderate mitotic activity. Moreover, PPTID includes transitional cases in which pineocytomatous and pineoblastoma features are associated. Synaptophysin and neuron-specific enolase are usually positive, with variable reactivity to neurofilament protein, chromogranin A, retinal S-antigen, and S-100 protein. PPTID Grades II and III can be distinguished on the basis of mitotic activity (higher in high-grade PPTID) and neurofilament protein immunoreactivity (higher in low-grade PPTID). Herein, we present the microsurgical management of a histologically confirmed high-grade PPTID.
Case Description:
A patient with high grade PPTID underwent sitting praying position and right paramedian supracerebellar infratentorial approach. The lesion was identified after lateral opening of the quadrigeminal cistern, followed by removal of its cystic component. Tissue samples were obtained under high microscopic magnification, and internal debulking of the tumor was performed with ring microforceps and bipolar forceps in the right hand and a thumb-regulated suction tube in the left hand. Continuous water irrigation provided us a clean surgical field and the recognition of small bleeding vessels. Moreover, water dissection technique was applied to recognize the cleavage plane of the tumor. Bipolar coagulation forceps were used to shrink the tumor and remove it by piecemeal reduction aiming to identify the anterior and lateral limits of the lesion. The poorly differentiated borders between the tumor and the surrounding parenchyma were determined under microscopic vision. Small vessels feeding the tumor were coagulated and cut. The most critical surgical stage was related with removal of some tumor remnants attached to the internal cerebral veins. A meticulous and skillful dissection was essential aiming to preserve these vascular structures. The final steps included meticulous hemostasis with electrocoagulation, Tachosil, and Surgicel. The postoperative course was uneventful. The patient underwent adjuvant radiotherapy and currently is alive, free of tumor recurrence 4 years after surgery.
Conclusion:
This unedited video offers all detailed aspects that are, as the senior author JH considers, essential for a neurosurgeon when performing an efficient and safe surgery for a high-grade PPTID.
Videolink:
http://surgicalneurologyint.com/videogallery/pineal-tumor-2.

Related Concept Videos
 01:02
The Pineal Gland
The primary secretion of the pineal gland is the hormone melatonin, derived from serotonin. The concentration of melatonin in the...
 01:25
The Intermediate Value Theorem
 01:19
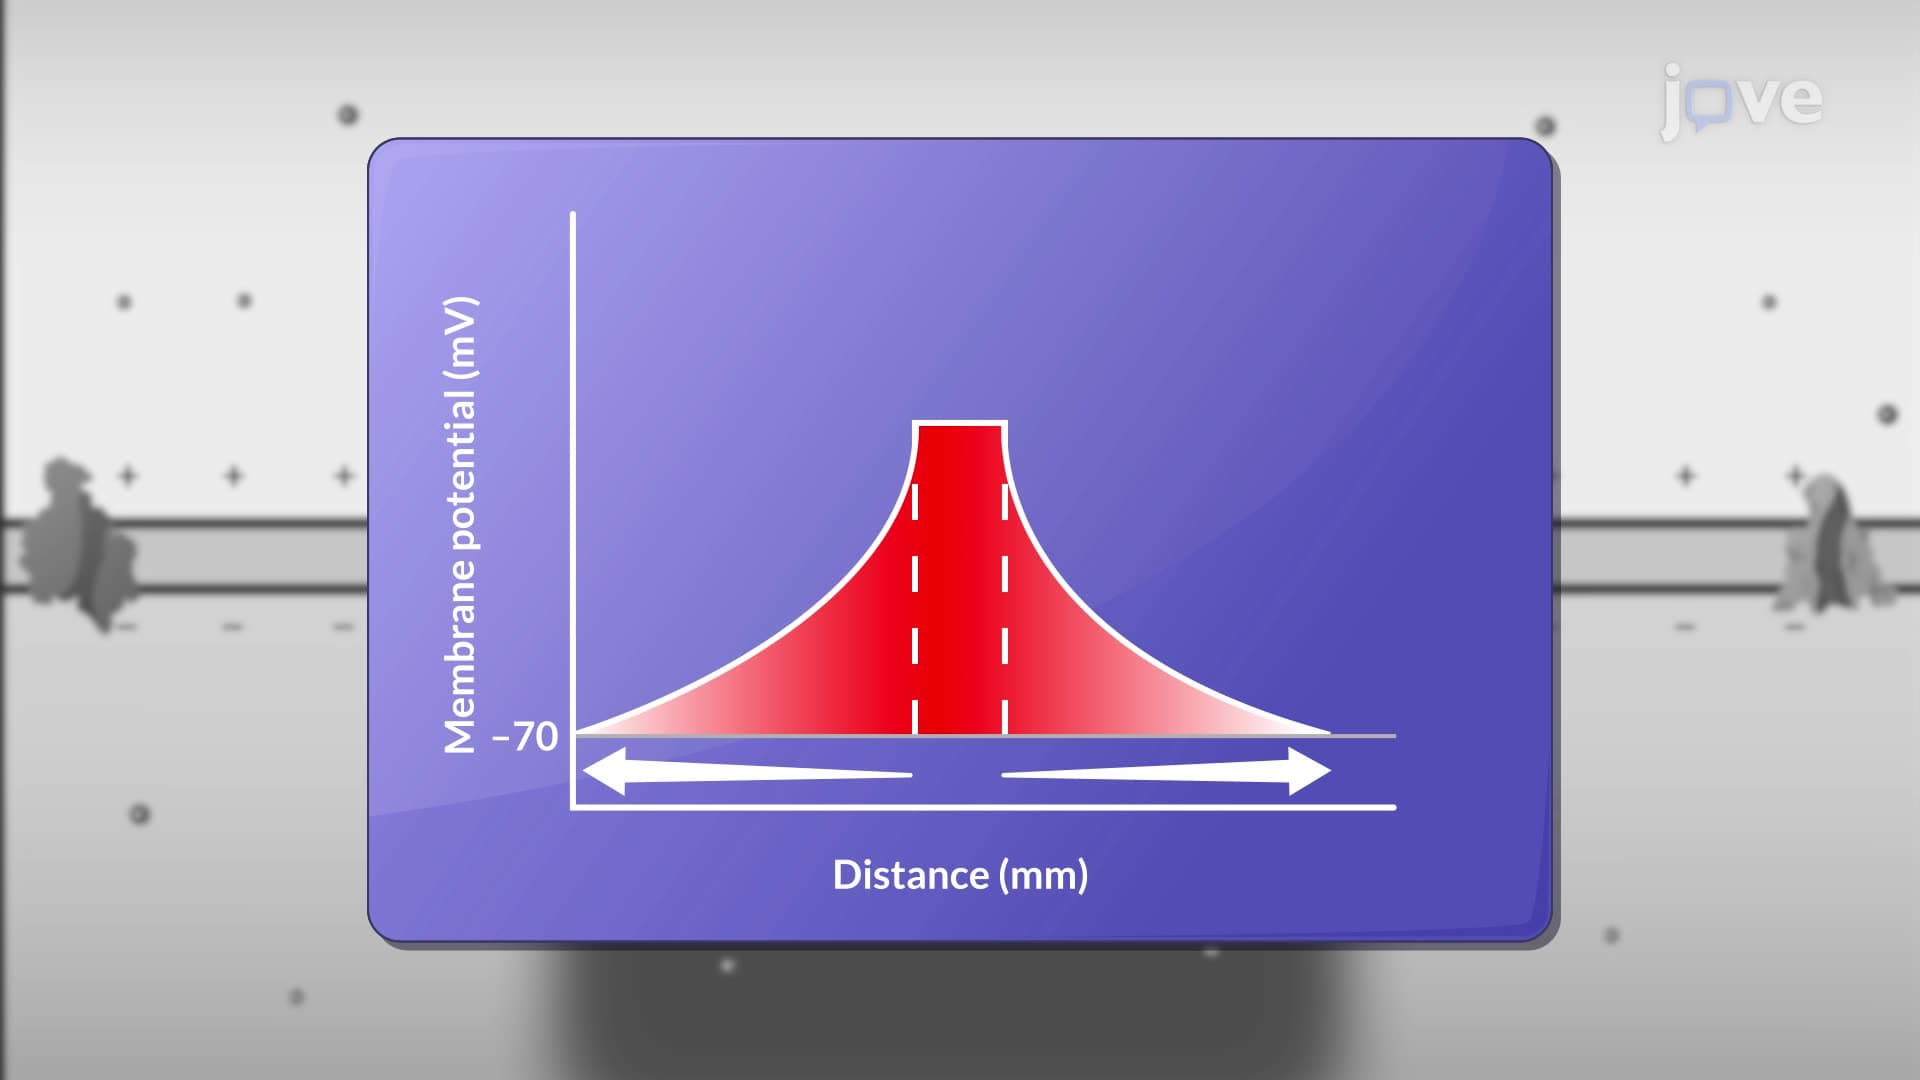
Graded Potential
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:35
Disassembly of Intermediate Filaments
Keratin proteins, found at the cell periphery near cell junctions, undergo a cycle of assembly and disassembly. In Type...
 01:31
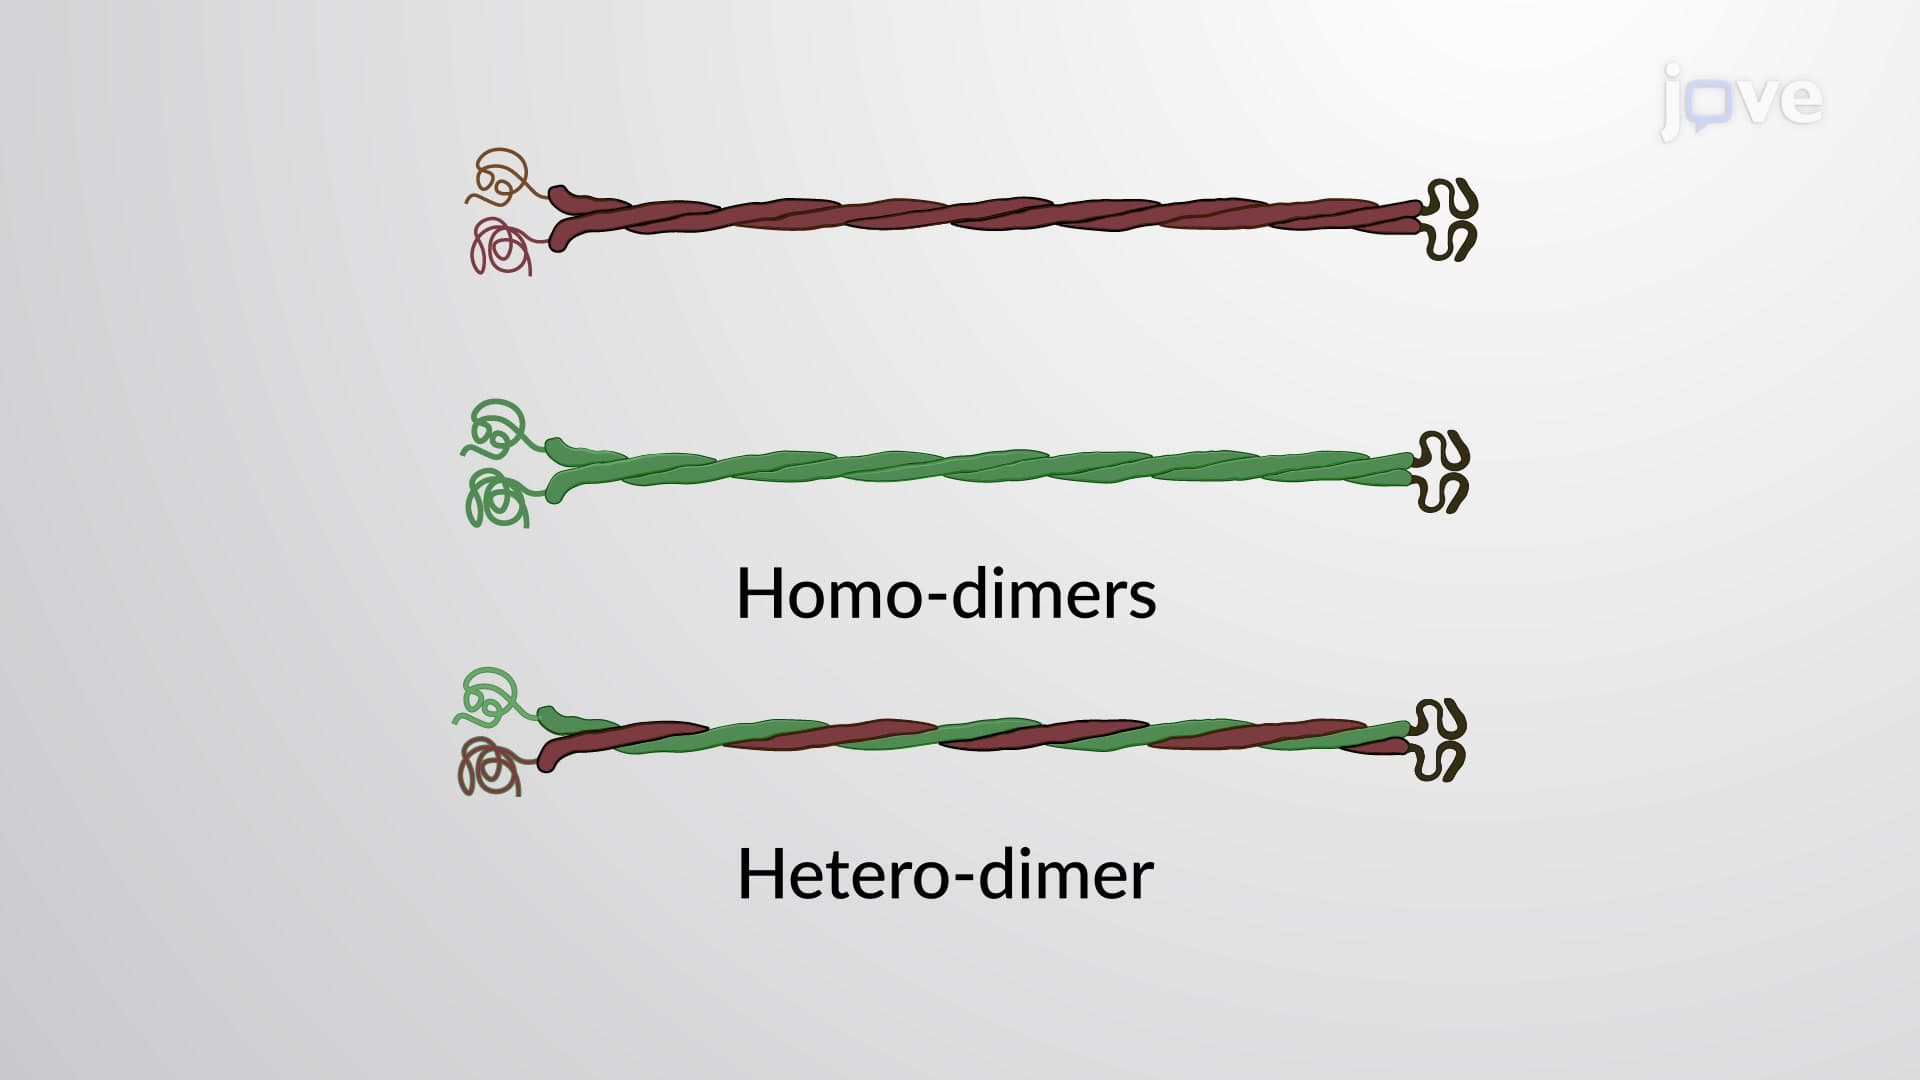
Types of Intermediate Filaments
 00:57
Formation of Intermediate Filaments