
Evaluation of data-driven respiratory gating waveforms for clinical PET imaging
Matthew D Walker1, Andrew J Morgan2, Kevin M Bradley3
1Radiation Physics and Protection, Churchill Hospital, Oxford University Hospitals NHS Foundation Trust, Oxford, OX3 7LE, UK. matthew.walker@ouh.nhs.uk.

Background:
We aimed to evaluate the clinical robustness of a commercially developed data-driven respiratory gating algorithm based on principal component analysis, for use in routine PET imaging.
Methods:
One hundred fifty-seven adult FDG PET examinations comprising a total of 1149 acquired bed positions were used for the assessment. These data are representative of FDG scans currently performed at our institution. Data were acquired for 4 min/bed position (3 min/bed for legs). The data-driven gating (DDG) algorithm was applied to each bed position, including those where minimal respiratory motion was expected. The algorithm provided a signal-to-noise measure of respiratory-like frequencies within the data, denoted as R. Qualitative evaluation was performed by visual examination of the waveforms, with each waveform scored on a 3-point scale by two readers and then averaged (score S of 0 = no respiratory signal, 1 = some respiratory-like signal but indeterminate, 2 = acceptable signal considered to be respiratory). Images were reconstructed using quiescent period gating and compared with non-gated images reconstructed with a matched number of coincidences. If present, the SUVmax of a well-defined lesion in the thorax or abdomen was measured and compared between the two reconstructions.
Results:
There was a strong (r = 0.86) and significant correlation between R and scores S. Eighty-six percent of waveforms with R ≥ 15 were scored as acceptable for respiratory gating. On average, there were 1.2 bed positions per patient examination with R ≥ 15. Waveforms with high R and S were found to originate from bed positions corresponding to the thorax and abdomen: 90% of waveforms with R ≥ 15 had bed centres in the range 5.6 cm superior to 27 cm inferior from the dome of the liver. For regions where respiratory motion was expected to be minimal, R tended to be < 6 and S tended to be 0. The use of DDG significantly increased the SUVmax of focal lesions, by an average of 11% when considering lesions in bed positions with R ≥ 15.
Conclusions:
The majority of waveforms with high R corresponded to the part of the patient where respiratory motion was expected. The waveforms were deemed suitable for respiratory gating when assessed visually, and when used were found to increase SUVmax in focal lesions.

Related Concept Videos
 01:12
Statistical Software for Data Analysis and Clinical Trials
 01:07
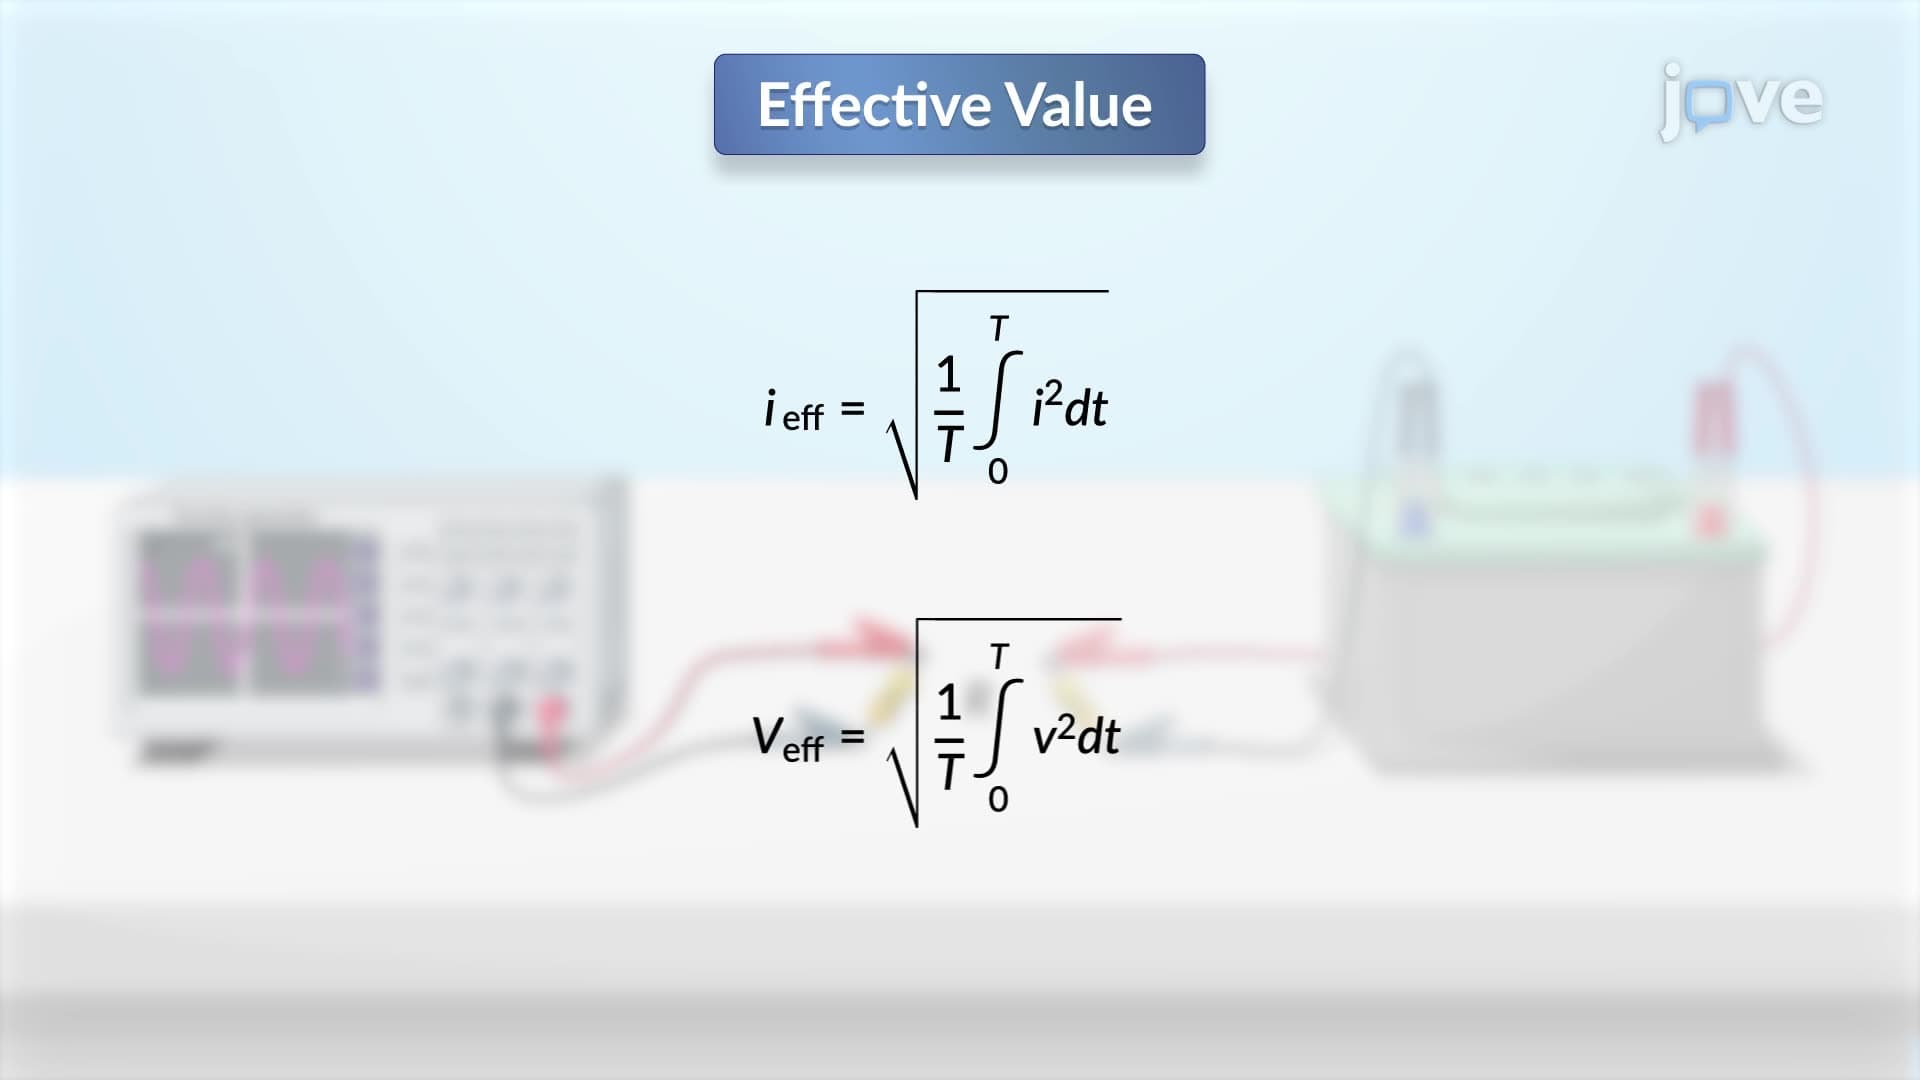
Effective Value of a Periodic Waveform
The effective value of a periodic current represents the direct current (DC) that conveys the same average power to a resistor as the periodic current itself. This concept is crucial when assessing AC circuits. To determine the...
 01:30
Underflow Gates
 01:30
Ligand-Gated Ion Channel Receptor: Gating Mechanism
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation