

Ulnar osteotomy and the ilizarov mini-fixator for pediatric chronic monteggia fracture-dislocations
Masaki Take1, Yuji Tomori, Takuya Sawaizumi
1Department of Orthopaedic Surgery, Nippon Medical School, Tokyo, Japan.

Abstract:
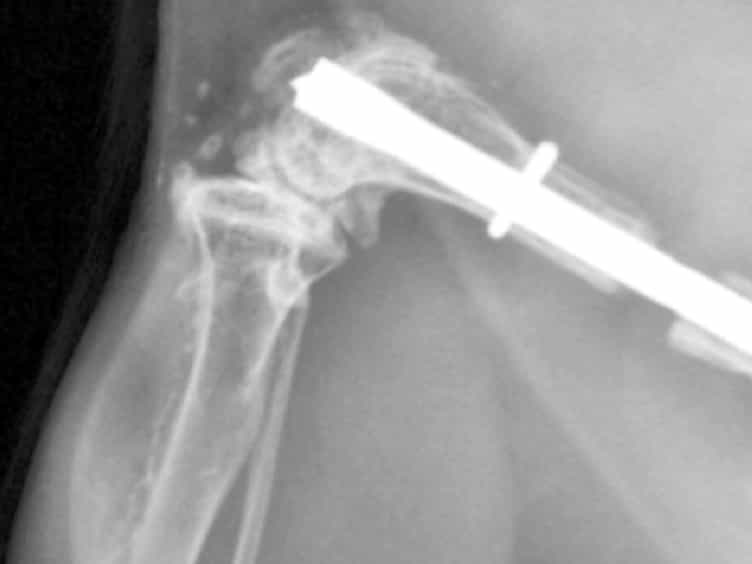
Treatment of chronic Monteggia fracture-dislocations remains controversial in skeletally immature patients. The present study aimed to review the clinical outcomes of surgical treatment with an Ilizarov mini-fixator for chronic Monteggia fracture-dislocations in children. From April 2003 to March 2014, 5 pediatric patients (4 males, 1 female) with chronic Monteggia fracture-dislocation were treated with an Ilizarov mini-fixator at our institution. The median age at the time of surgery was 9 years (range 5-14 years), median duration from injury to surgery was 31 months (range 2-125 months), and median duration of follow-up was 12 months (range 11 months-10 years). All patients underwent opening wedge osteotomy of the proximal ulna followed by the application of an Ilizarov mini-fixator. Although closed reduction was attempted after ulnar osteotomy and application of the Ilizarov mini-fixator, open reduction of the radial head was required in all patients. In 4 patients, dense scar tissue in the radiocapitellar joint was excised to enable reduction of the radial head; the remaining patient had traumatic radioulnar synostosis, and underwent separation of the synostosis followed by anconeus interposition arthroplasty. No patient received bone grafting at the ulnar osteotomy site, repair or reconstruction of the annular ligament, or temporary fixation of the radial head with transarticular wire. The median period of external fixation was 10 weeks (range 8-13 weeks). Although there were no severe complications such as deep infection and neurovascular disturbance, asymptomatic radial head subluxation occurred in 2 patients. The patient with traumatic synostosis had residual posterior subluxation with limitation of forearm rotation, and another patient with radial head enlargement had residual anterior subluxation. The median postoperative ranges of motion in pronation, supination, extension, and flexion were 90°, 90°, 0°, and 140°, respectively. The median Kim's elbow performance score was 65 (range 50-75) preoperatively, which improved to 94 (range 80-100) at final follow-up. The outcome was rated as excellent in 4 cases, and good in 1. In pediatric chronic Monteggia fracture-dislocations, ulnar osteotomy followed by the application of an Ilizarov mini-fixator is a viable option that is less invasive than plate fixation.
More Related Videos
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling
Published on: January 5, 2015
 07:41
An Intramedullary Locking Nail for Standardized Fixation of Femur Osteotomies to Analyze Normal and Defective Bone Healing in Mice
Published on: November 13, 2016
Related Concept Videos
 01:03
Fixation and Sectioning
The simplest type of preparation is the wet mount, in which the specimen is placed in a drop of liquid on the slide. A liquid specimen can be directly deposited on the slide using a dropper. Solid specimens, such as skin scraping, can be placed on the slide before adding a drop of liquid to prepare the wet mount. Sometimes the liquid is simply water, but stains are often added...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:28
Carbon-dioxide Fixation
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism