Related Experiment Video
Updated: Jan 31, 2026

A Protocol for Lentiviral Transduction and Downstream Analysis of Intestinal Organoids
Published on: April 20, 2015
Autologous Intestinal Reconstructive Surgery in the Management of Total Intestinal Aganglionosis
Fabio Fusaro1, Francesco Morini1, Annika Mutanen2
1Department of Medical and Surgical Neonatology, Newborn Surgery Unit, Digestive and Endoscopic Surgery, Gastroenterology and Nutrition, Intestinal Failure Rehabilitation Research Group, Bambino Gesù Children's Hospital Research Institute, Rome, Italy.

Objectives:
Total/near total intestinal aganglionosis (TIA/NTIA) is the most uncommon and life-threatening form of Hirschsprung disease (HD). The management of TIA/NTIA is challenging and the role of autologous intestinal reconstructive (AIR) surgery is controversial. The objective is to evaluate the effectiveness of AIR in patients with TIA/NTIA.
Methods:
Records from children affected by TIA and enrolled in the multicenter international Pediatric Intestinal Rehabilitation and Transplantation Registry were retrospectively reviewed.
Results:
Fourteen patients with TIA were identified. TIA diagnosis was confirmed histologically at the median age of 14 days of life. All received a proximal decompressive jejunostomy. Two patients died, 4 patients had satisfactory stoma output with enteral tolerance without additional procedures, 8 underwent 10 AIR procedures (4 Ziegler myotomy-myectomy, 3 transposition of aganglionic ileum with or without myotomy, 2 simple tapering, 1 longitudinal lengthening and tailoring procedure with associated myotomy). AIR significantly reduced median stoma output, from 197 to 31 mL · kg · day (P = 0.0001). The reduction was seen in all patients. In addition, AIR improved enteral tolerance in the long term in 5 of 8 patients (63%), and temporarily in 1, leading to a reduction of parenteral nutrition requirement from 100% to 70% (P = 0.0231).
Conclusions:
AIR surgery in carefully selected patients may be useful and effective way to enhance residual bowel absorptive function and to reduce parenteral nutrition requirements. AIR and intestinal transplantation are complementary surgical tools in the complex treatment algorithm of TIA/NTIA.

Related Concept Videos
 01:23
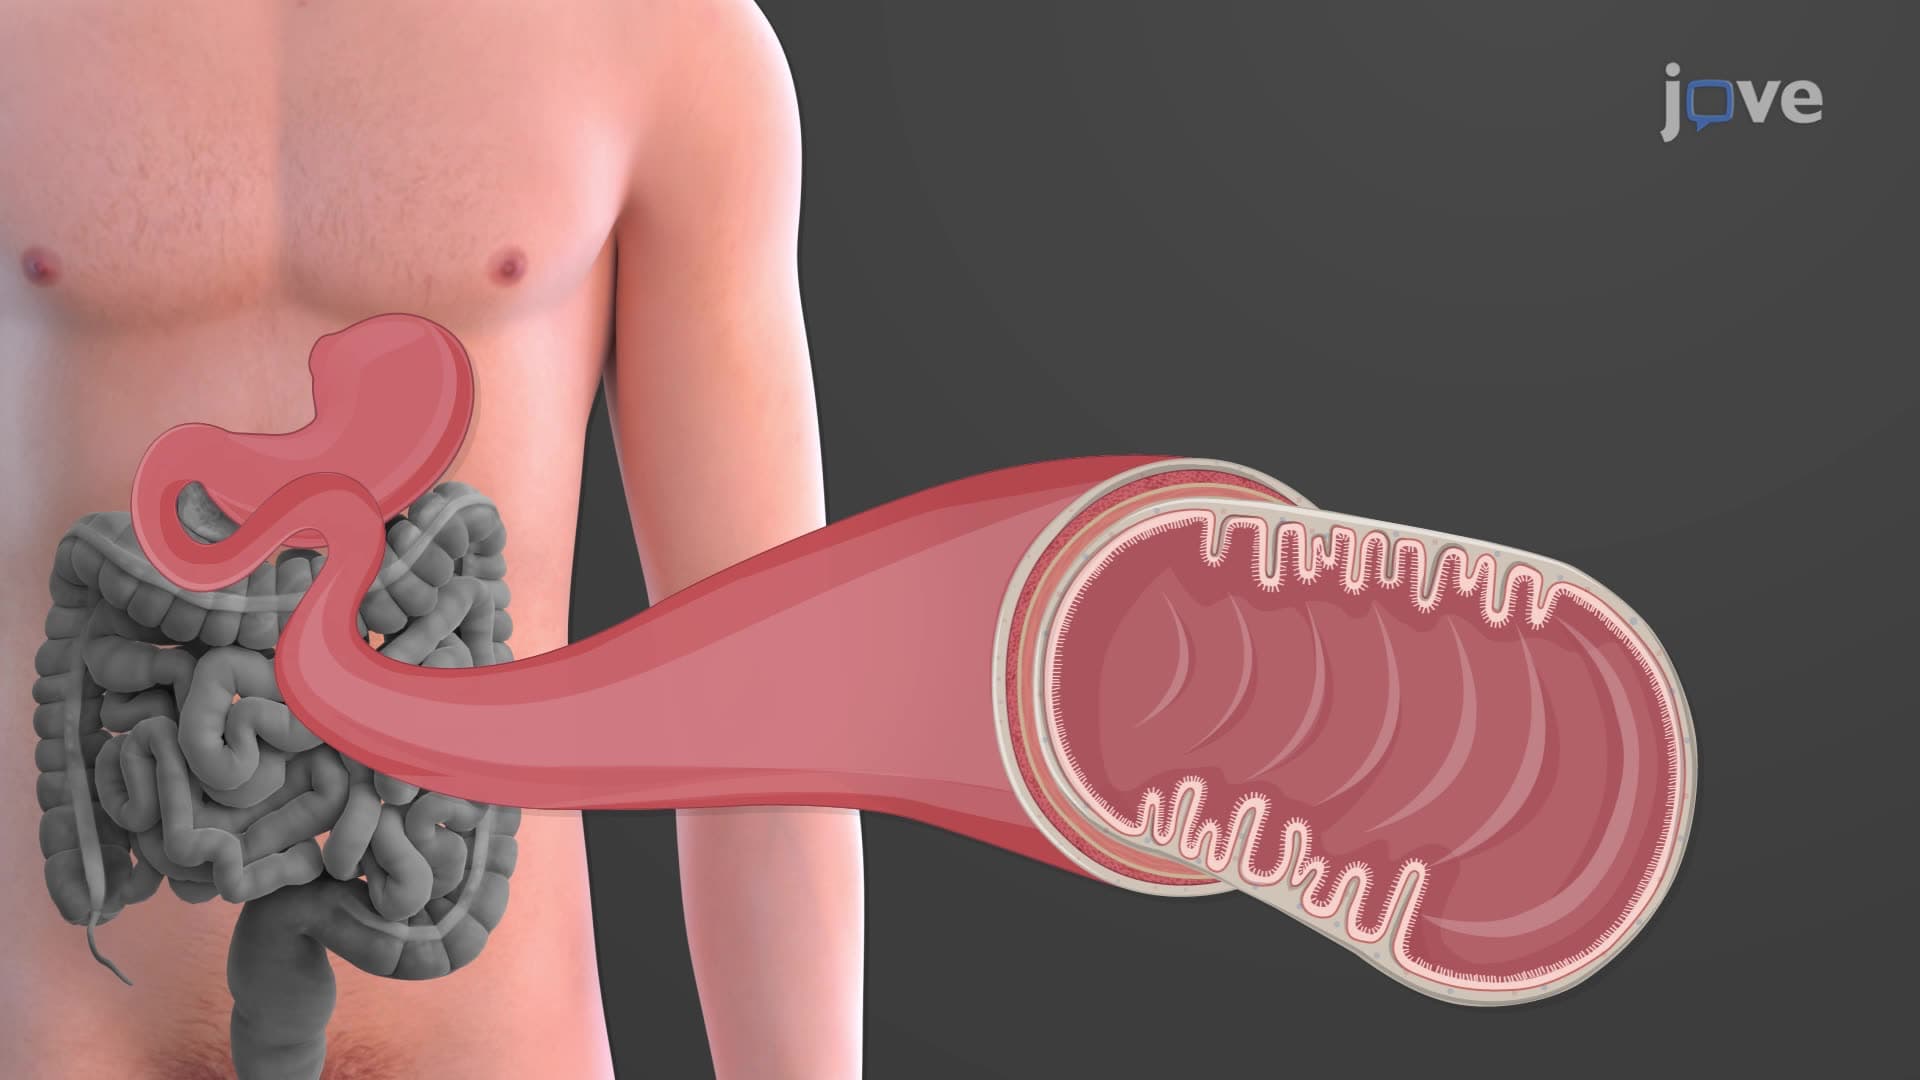
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:15
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
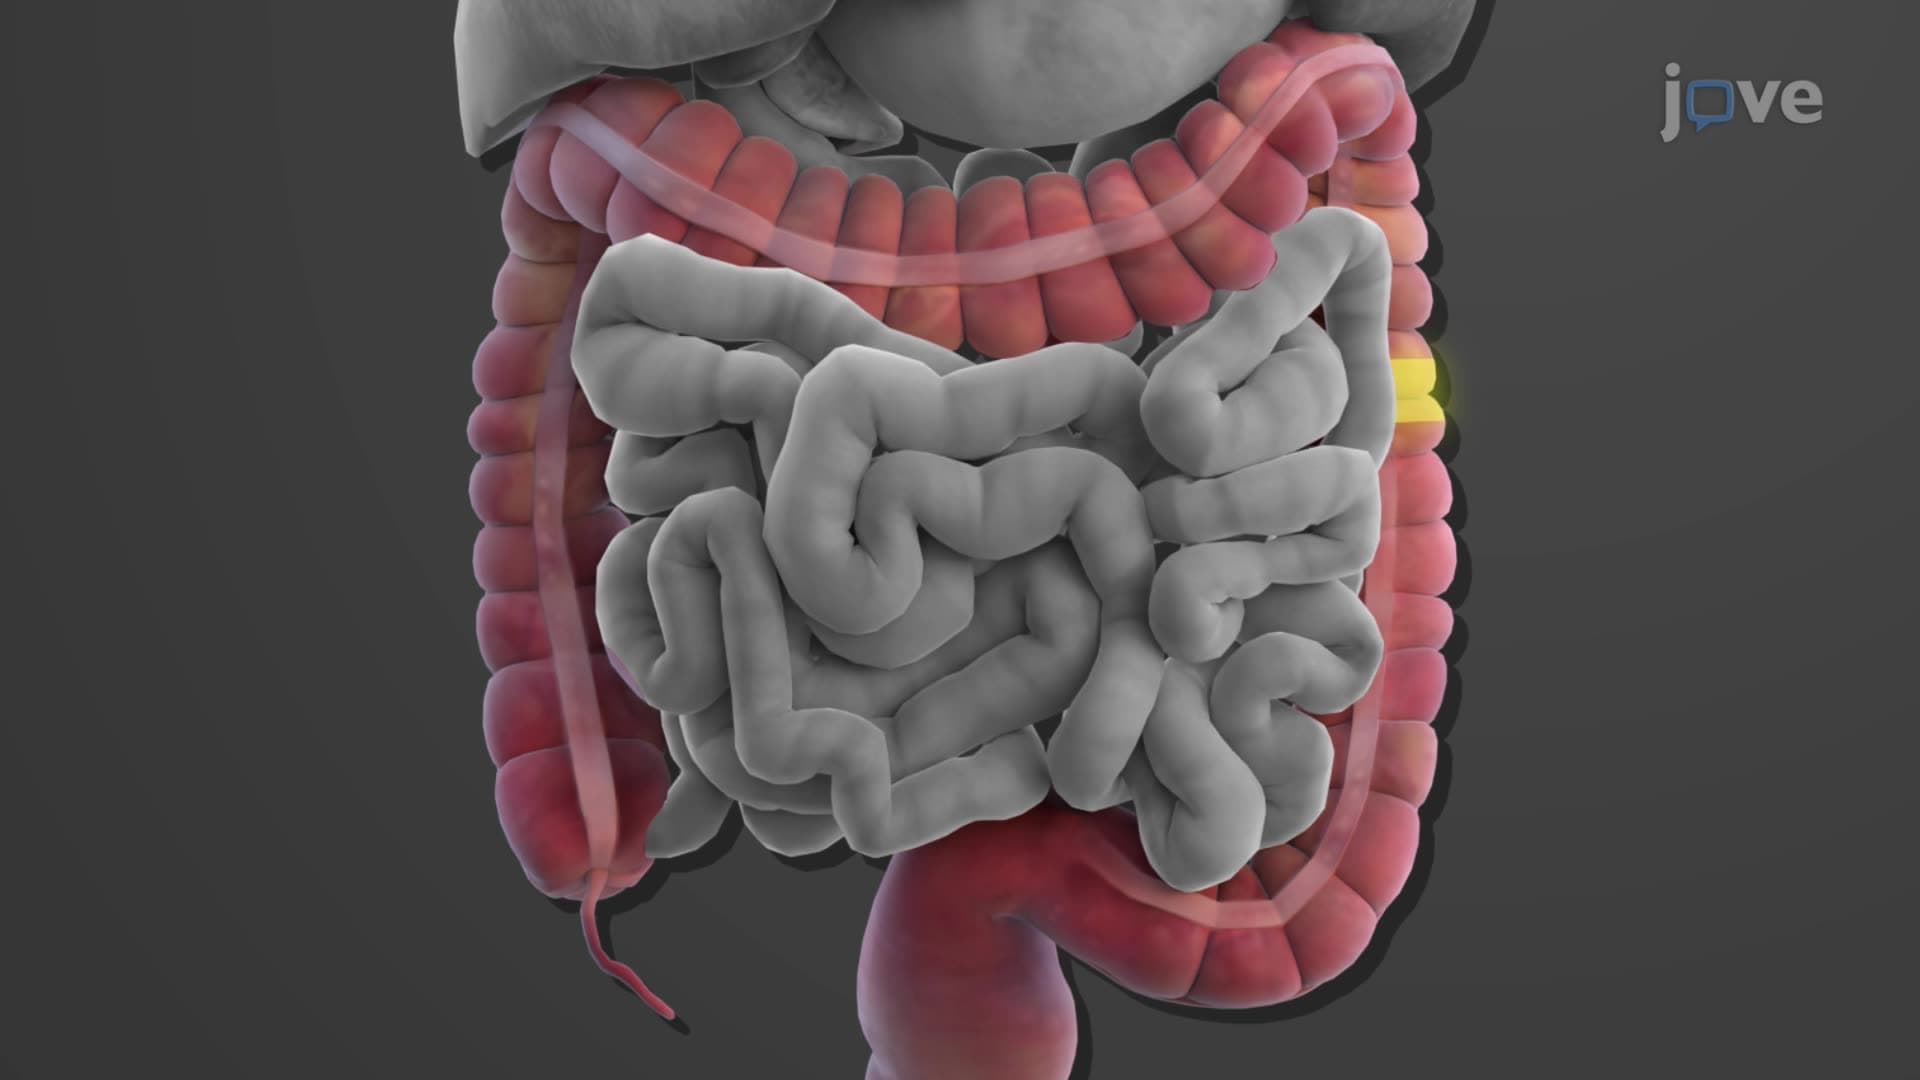
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
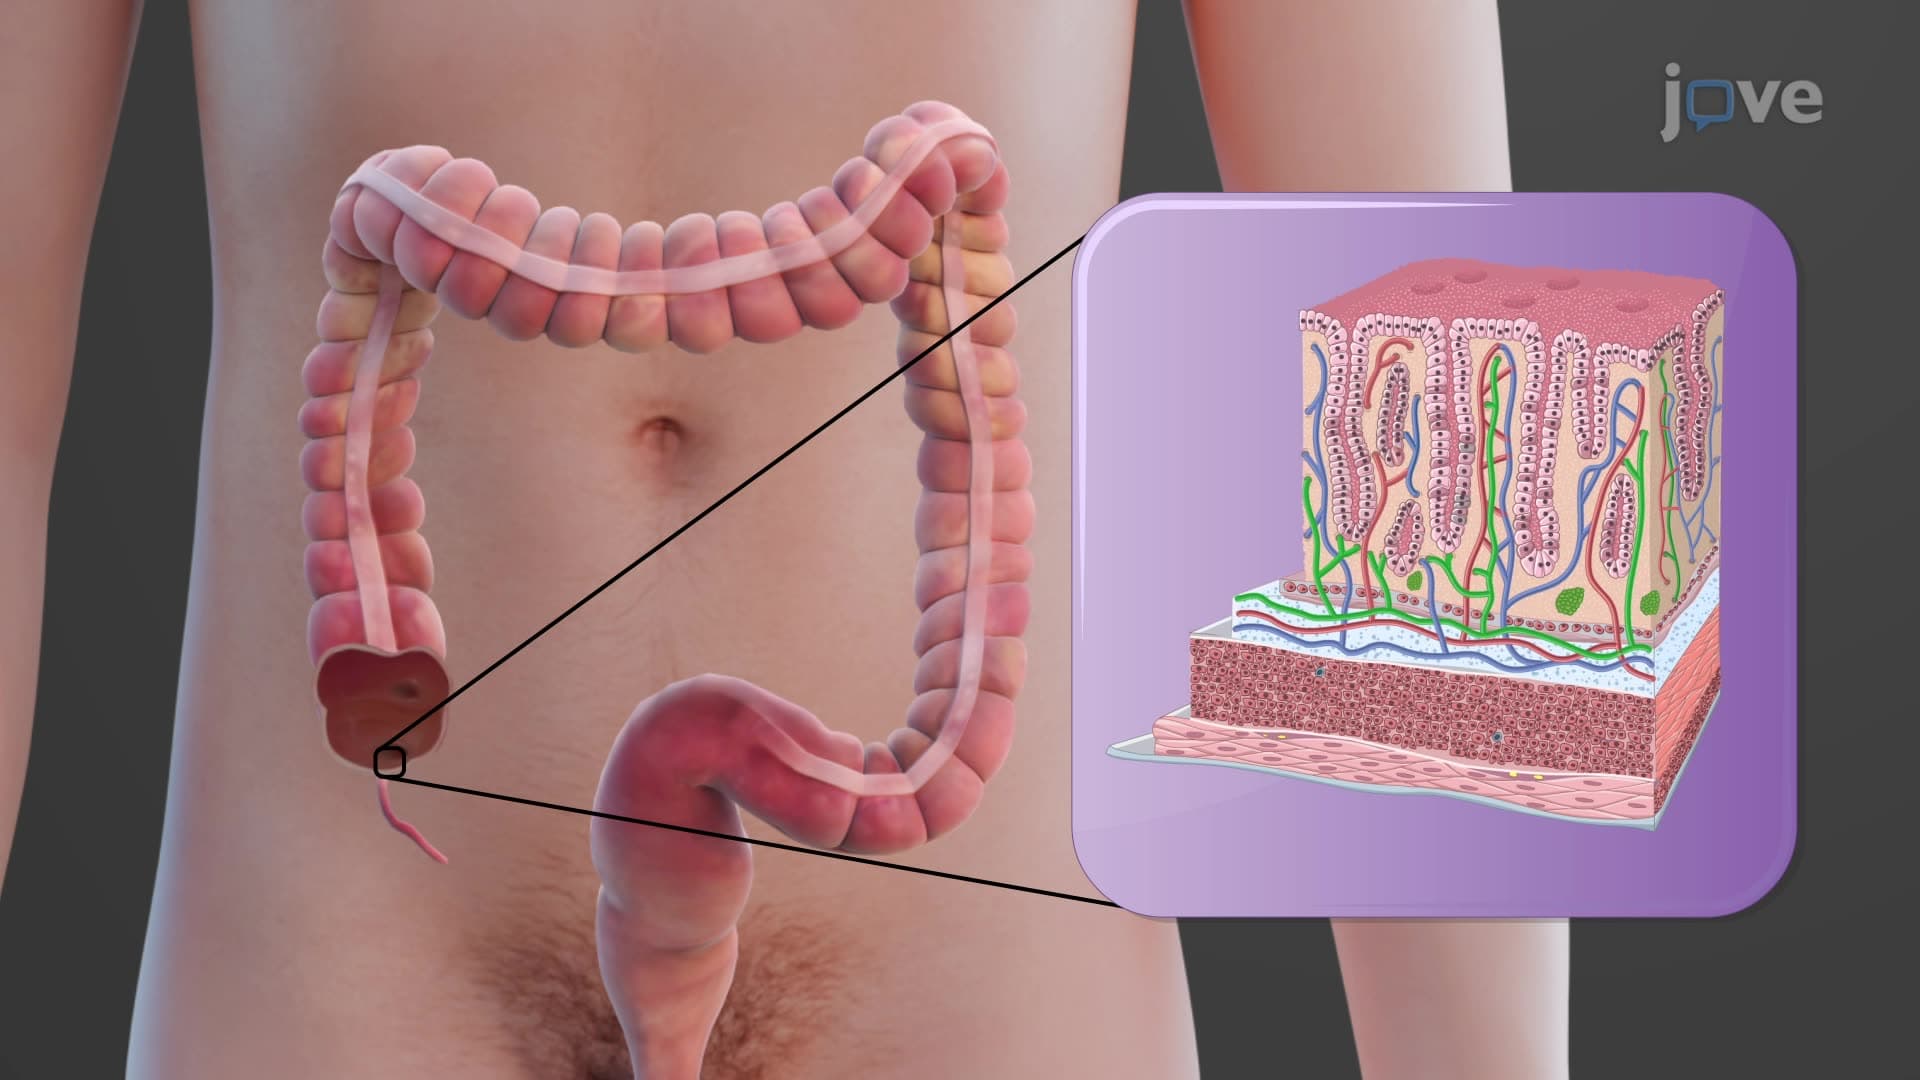
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
Histology of the Small Intestine
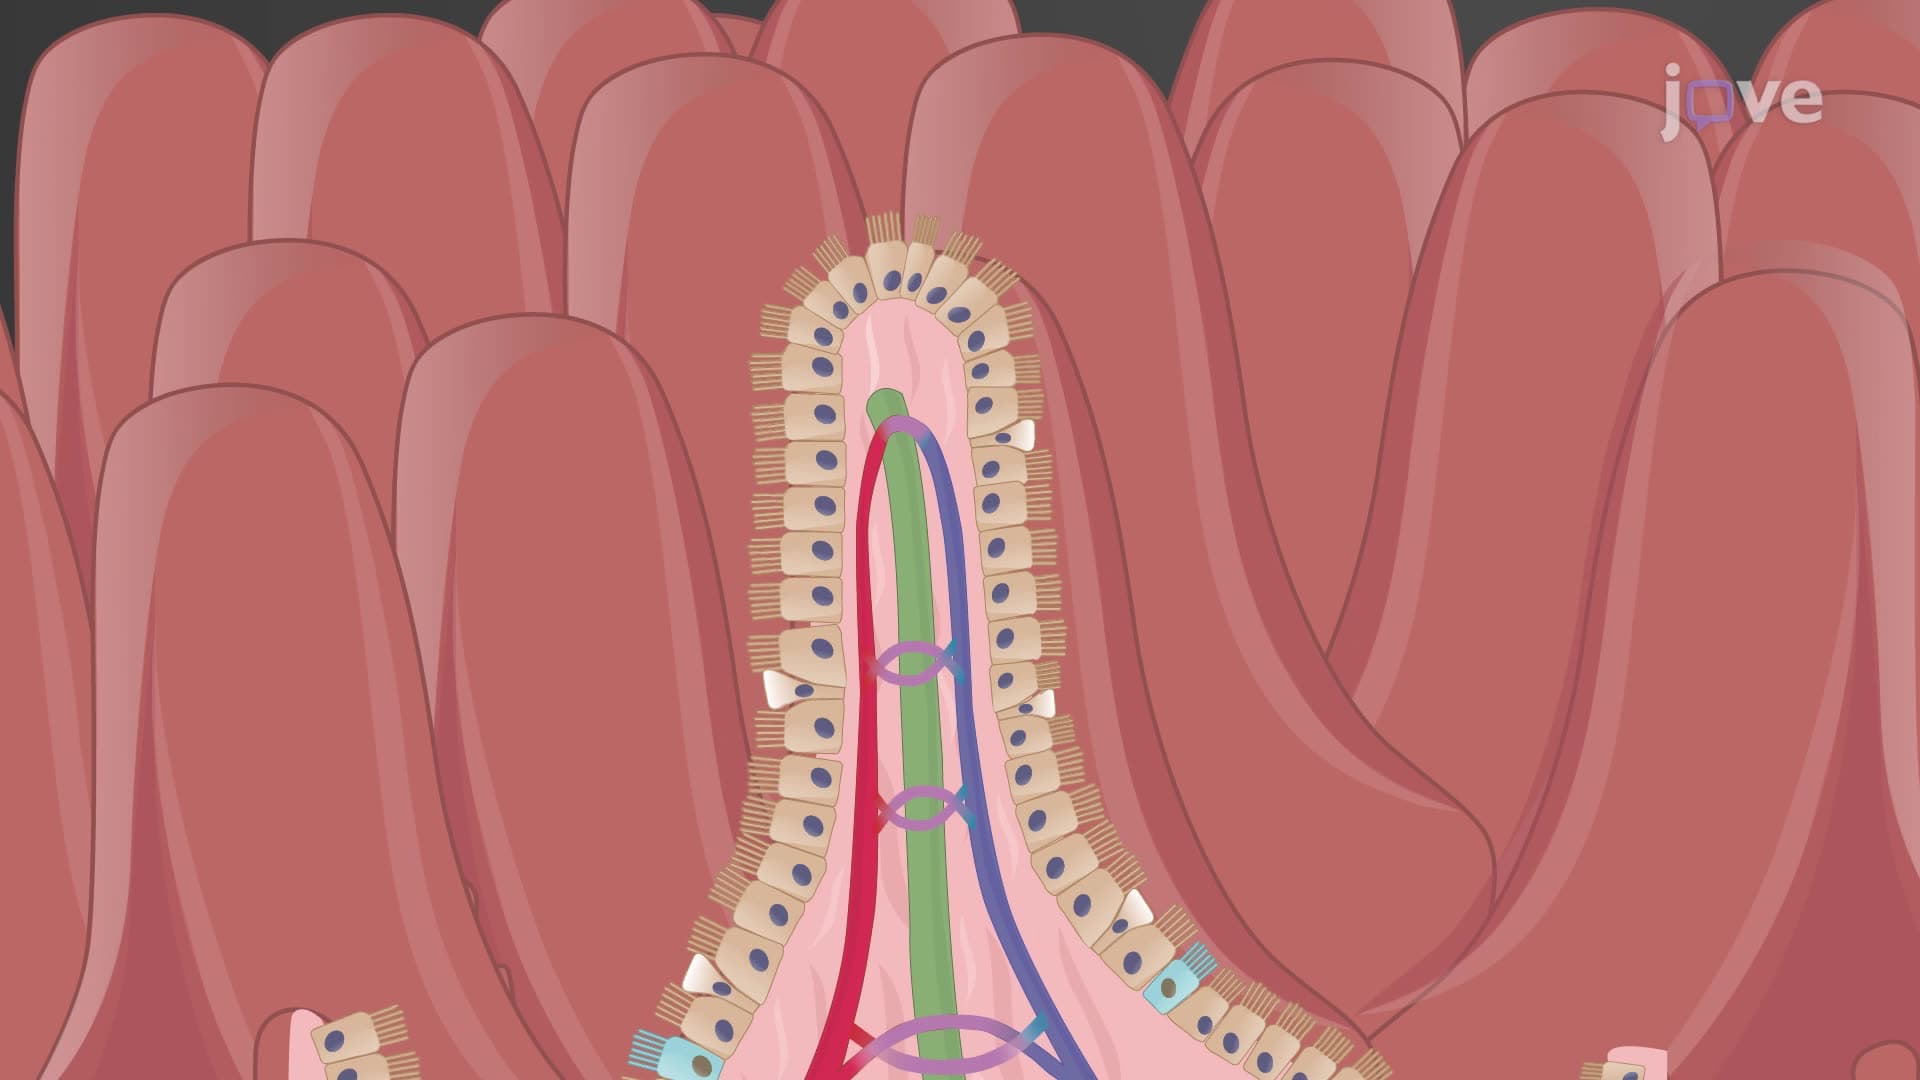
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:29
Bacterial Flora of the Large Intestine
The normal gut flora of the colon plays a critical role in generating essential vitamins such as vitamins K, B5, and B7.