Related Experiment Video
Updated: Jan 31, 2026
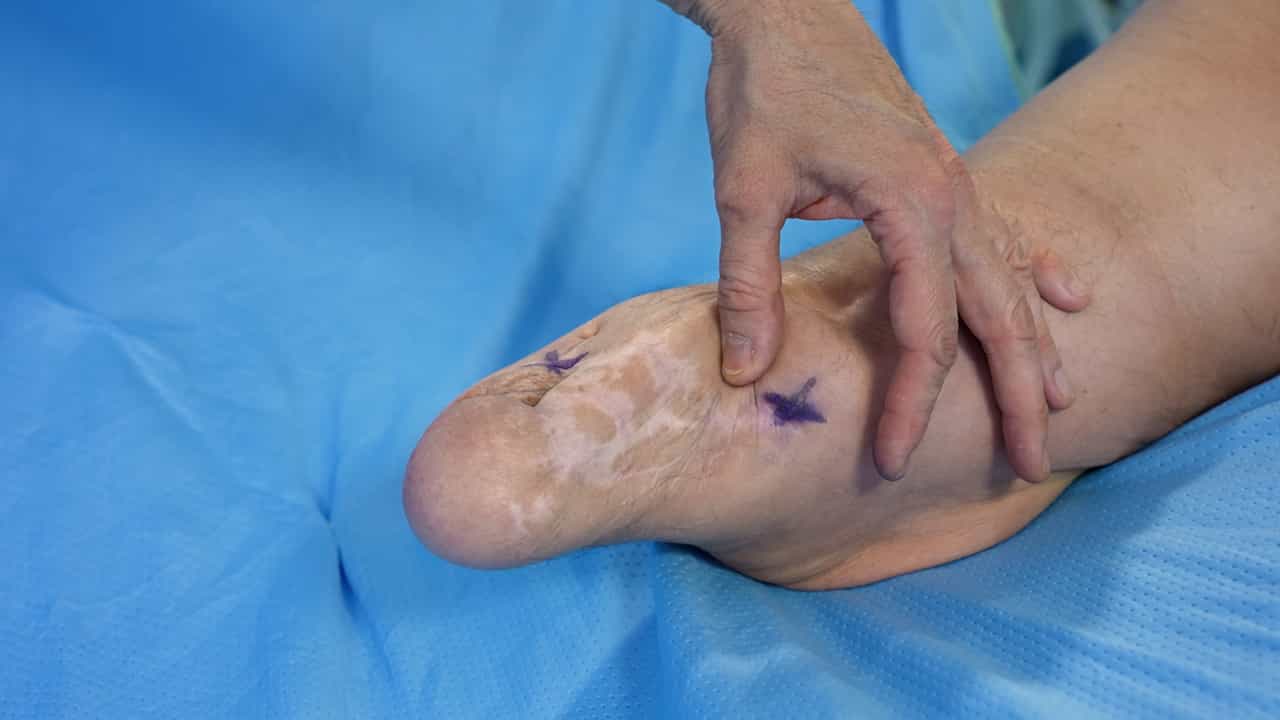

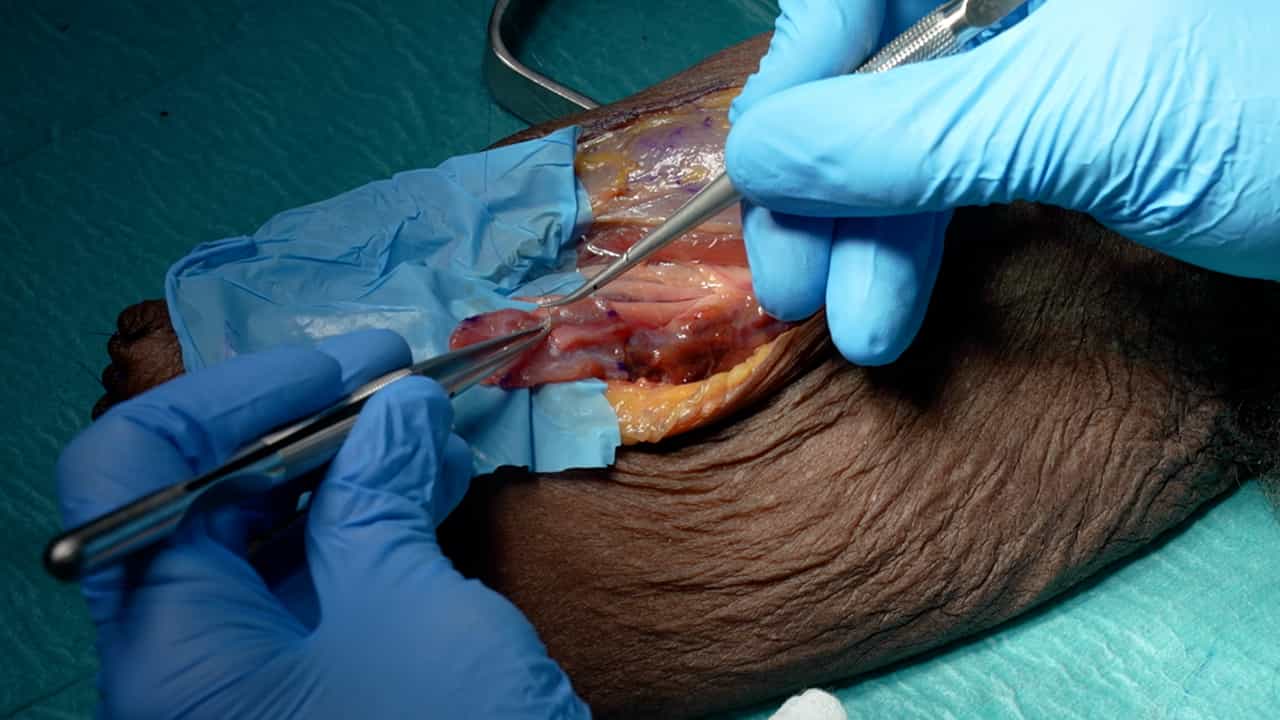
Author Spotlight: Advancements and Challenges in Surgical Treatments for Postamputation Pain
Published on: March 8, 2024
Enteral versus intravenous approach for the sedation of critically ill patients: a randomized and controlled trial
Giovanni Mistraletti1,2, Michele Umbrello3, Silvia Salini4
1Dipartimento di Fisiopatologia Medico-Chirurgica e dei Trapianti, Università degli Studi di Milano, A.O. San Paolo - Polo Universitario, Via A. Di Rudinì, 8, 20142, Milano, Italy. giovanni.mistraletti@unimi.it.

Background:
ICU patients must be kept conscious, calm, and cooperative even during the critical phases of illness. Enteral administration of sedative drugs might avoid over sedation, and would be as adequate as intravenous administration in patients who are awake, with fewer side effects and lower costs. This study compares two sedation strategies, for early achievement and maintenance of the target light sedation.
Methods:
This was a multicenter, single-blind, randomized and controlled trial carried out in 12 Italian ICUs, involving patients with expected mechanical ventilation duration > 72 h at ICU admission and predicted mortality > 12% (Simplified Acute Physiology Score II > 32 points) during the first 24 h on ICU. Patients were randomly assigned to receive intravenous (midazolam, propofol) or enteral (hydroxyzine, lorazepam, and melatonin) sedation. The primary outcome was percentage of work shifts with the patient having an observed Richmond Agitation-Sedation Scale (RASS) = target RASS ±1. Secondary outcomes were feasibility, delirium-free and coma-free days, costs of drugs, length of ICU and hospital stay, and ICU, hospital, and one-year mortality.
Results:
There were 348 patients enrolled. There were no differences in the primary outcome: enteral 89.8% (74.1-100), intravenous 94.4% (78-100), p = 0.20. Enteral-treated patients had more protocol violations: n = 81 (46.6%) vs 7 (4.2%), p < 0.01; more self-extubations: n = 14 (8.1%) vs 4 (2.4%), p = 0.03; a lighter sedative target (RASS = 0): 93% (71-100) vs 83% (61-100), p < 0.01; and lower total drug costs: 2.39 (0.75-9.78) vs 4.15 (1.20-20.19) €/day with mechanical ventilation (p = 0.01).
Conclusions:
Although enteral sedation of critically ill patients is cheaper and permits a lighter sedation target, it is not superior to intravenous sedation for reaching the RASS target.
Trial Registration:
ClinicalTrials.gov, NCT01360346 . Registered on 25 March 2011.
More Related Videos
Related Concept Videos
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:23
Sedatives and Hypnotics: Overview
Sedative-hypnotics are categorized into barbiturates, benzodiazepines (BZDs), and non-benzodiazepines or Z-drugs. These drugs work by suppressing central nervous system activity, and this suppression is dose-dependent. Older sedative medications, like barbiturates, follow a linear curve in...
 01:20
Sedatives and Hypnotics Drugs: Barbiturates
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...
 01:11
Clinical Trials: Overview
 01:12
Trial and Error and Algorithm