Related Experiment Video
Updated: Jan 31, 2026
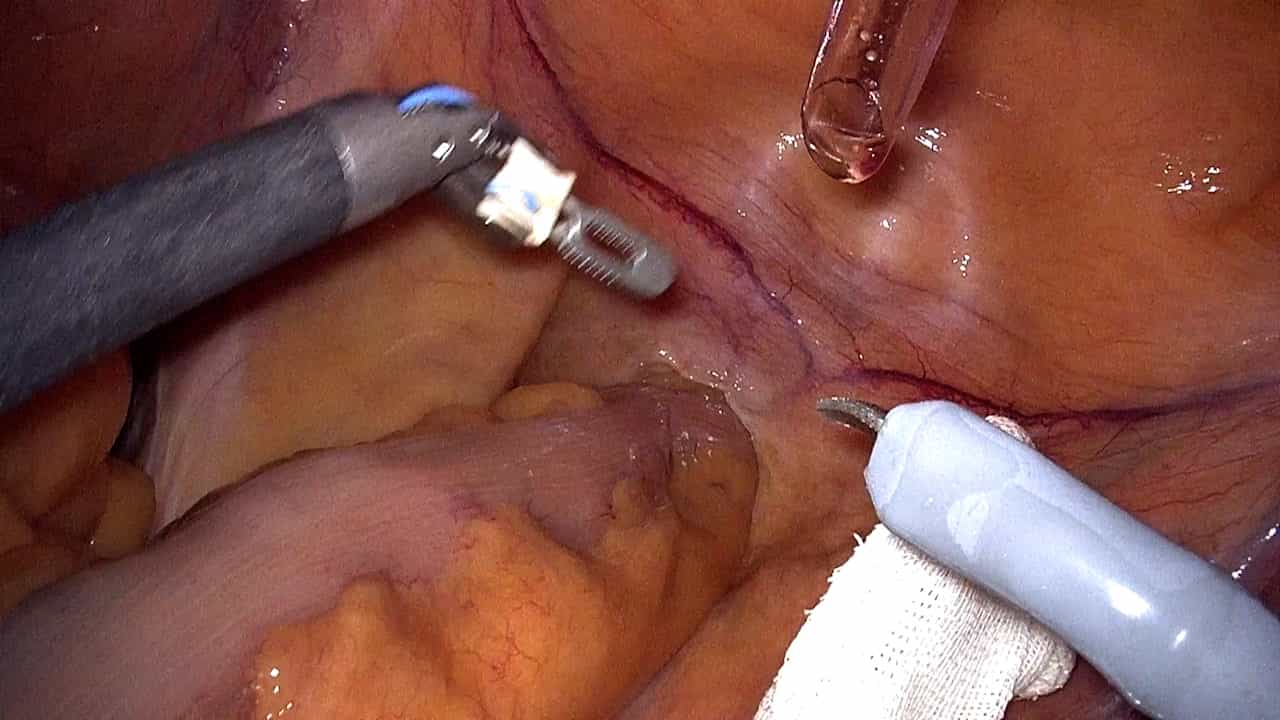

Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Standard stapled transanal rectal resection versus stapled transanal rectal resection with one high-volume stapler to
Domenico Mascagni1, Alessandra Panarese1, Chiara Eberspacher1
1Department of Surgical Sciences, Sapienza University, Rome, Italy.

Background:
The causes of obstructed defecation syndrome (ODS) can actually be either functional or mechanical (primary or secondary deficit of the sensitivity, slow bowel transit, pelvic floor dyssynergia, internal and external rectal prolapse, recto-anal intussusceptions, anterior or posterior rectocele and pelvic prolapse of the bladder, uterus, bowel or sigma). The aim of our study was to evaluate the safety, efficacy and feasibility of stapled transanal rectal resection (STARR) procedure performed by a single or double stapler through clinical and functional outcomes for transanal stapled surgery.
Methods:
From January 2016 to October 2017, ninety patients with ODS secondary to rectal prolapse, anal-rectal intussusception and anterior rectocele, that underwent to a STARR procedure were enrolled. Thirty of these underwent a STARR procedure with double circular stapler PPH-01 (Group A); 30 with single circular stapler CPH34HV with a purse string suture (Group B); and 30 with single circular stapler CPH34HV with a "parachute technique" (Group C). All patients were selected with clinical examination, Wexner score for fecal incontinence and ODS score for constipation. Patients also underwent a Defeco RMN for an anatomical and dynamic evaluation of the pelvic floor.
Results:
No recurrence rates were observed in the three groups. The mean operative time was 46.3 minutes in group A; 34.5 minutes in group B; and 37.6 minutes in Group C. The volume of the resected specimen was 17 mL in group A; 15 mL in group B; and 16 mL in Group C. Complications were bleeding (3.3% in group A); fecal urgency (6.6% in group A, 10% in group B and 3.3% in group C); rectal hematoma (3.3% in group A). all symptoms significantly improved after the operation without differences between groups.
Conclusions:
The STARR technique performed with a single stapler CPH34HV is safe, faster and less expensive than the STARR performed by a double PPH01. Besides, with the parachute technique, it is possible to resect asymmetric prolapses.
More Related Videos
 07:51
The C-seal: A Biofragmentable Drain Protecting the Stapled Colorectal Anastomosis from Leakage
Published on: November 4, 2010
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Related Concept Videos
 01:27
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:24
Hemodialysis II: Procedure and Complications
 02:59
Cancer Prevention
Some...
 01:30
Pneumonia III: Complications and Assessment
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma