Related Experiment Video
Updated: Jan 31, 2026
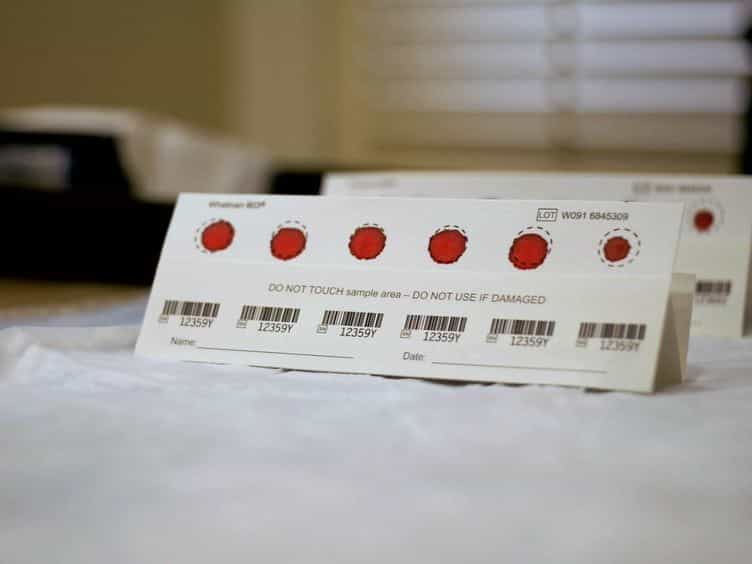

Dried Blood Spot Collection of Health Biomarkers to Maximize Participation in Population Studies
Published on: January 28, 2014
Perceived racism may partially explain the gap in health between Aboriginal and non-Aboriginal Victorians: A
Alison Markwick1, Zahid Ansari1, Darren Clinch2
1Department of Epidemiology and Preventive Medicine, School of Public Health and Preventive Medicine, Monash University, 553 St Kilda Rd, Melbourne, Victoria 3004, Australia.

Background:
There is a persistent gap in the health of Aboriginal Victorians compared with non-Aboriginal Victorians, where Aboriginal Victorians have poorer health. Currently, the most commonly touted explanation for this gap revolves around health behaviours known as 'lifestyle risk factors'. Yet the gap in health is similarly matched by persistent gaps in social and economic outcomes that reflect past and ongoing discrimination of Aboriginal peoples across Australia. Perceived racism has been implicated as a key determinant of the gap in health between Indigenous and non-Indigenous peoples across the world. We sought to determine the contribution of perceived racism to the gap in health and how this compared with the contribution of lifestyle risk factors and other determinants of health such as socioeconomic status.
Methods:
We combined data from 2011, 2012 and 2014 Victorian Population Health Surveys (VPHS) to obtain a sample size of 33,833 Victorian adults, including 387 Aboriginal adults. The VPHS is a population-representative, cross-sectional, computer-assisted telephone interview survey conducted annually. Using logistic regression, poor self-reported health status was the dependent variable and Aboriginal status was the primary independent variable of interest. Secondary independent variables included age, sex, perceived racism, socioeconomic status, and lifestyle risk factors.
Results:
Aboriginal Victorians were almost twice as likely as non-Aboriginal Victorians to report poor health; OR=1.9 (95% confidence interval; 1.3-2.6). Perceived racism explained 34% of the gap in self-reported health status between Aboriginal and non-Aboriginal Victorians, followed by: smoking (32%), unhealthy bodyweight (20%), socioeconomic status (15%), excessive consumption of alcohol (13%), and abstinence from alcohol consumption (13%). In contrast, physical inactivity made no contribution. Together, perceived racism and smoking explained 58% of the gap, while all secondary independent variables explained 82% of the gap.
Conclusions:
Perceived racism may be an independent health risk factor that explains more than a third of the health gap between Aboriginal and non-Aboriginal Victorians; equivalent in strength to smoking. The recognised failure of the Australian government's Closing the Gap strategy may be due in part to the failure to consider other determinants of the health gap beyond the lifestyle risk factors, namely racism, which may act to damage health through multiple pathways at multiple points along the causal chain.
More Related Videos
 08:57
Quantification of Optic Nerve Cross Sectional Area on MRI: A Novel Protocol using Fiji Software
Published on: September 4, 2021
 05:57
A Rapid Automated Protocol for Muscle Fiber Population Analysis in Rat Muscle Cross Sections Using Myosin Heavy Chain Immunohistochemistry
Published on: March 28, 2017
Related Concept Videos
 01:50
Cross-Sectional Research
 01:24
Finding Volume Using Cross-Sectional Area
 01:26
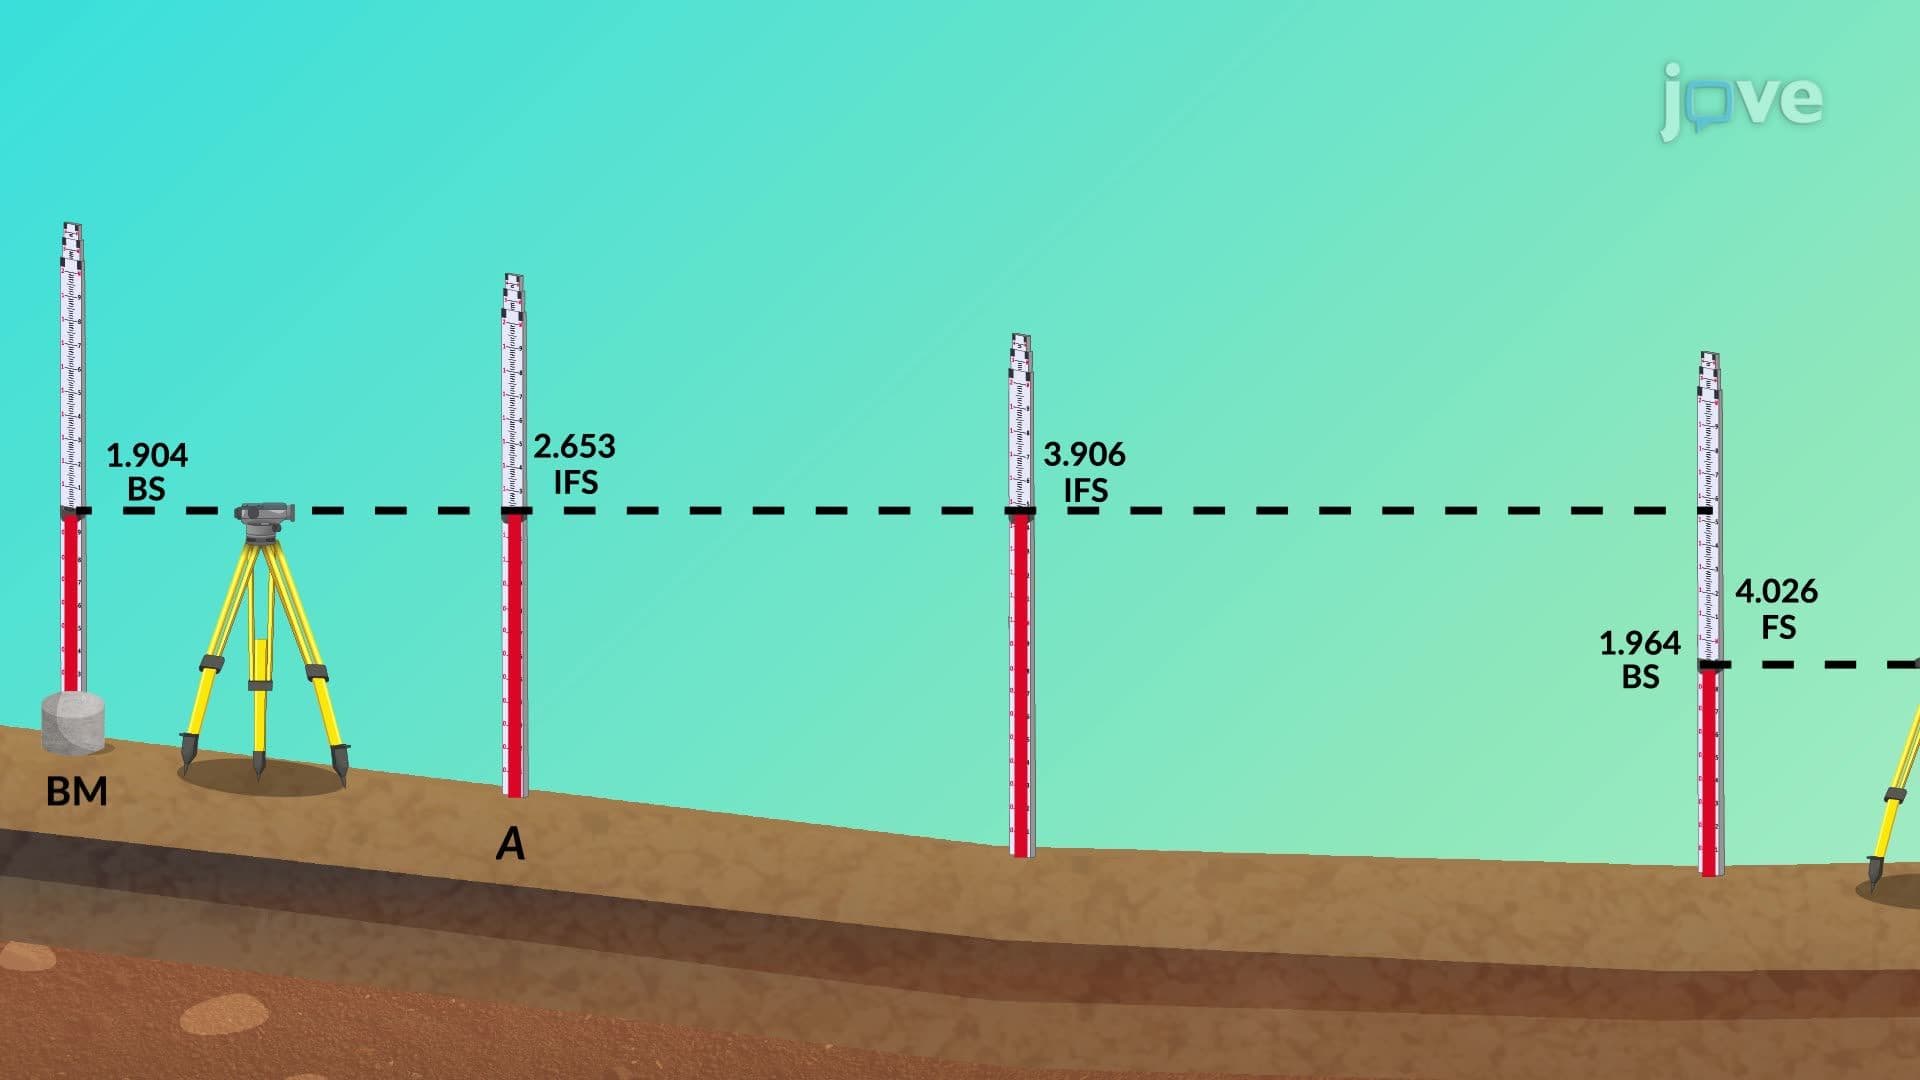
Profile Leveling and Cross Sections
 01:16
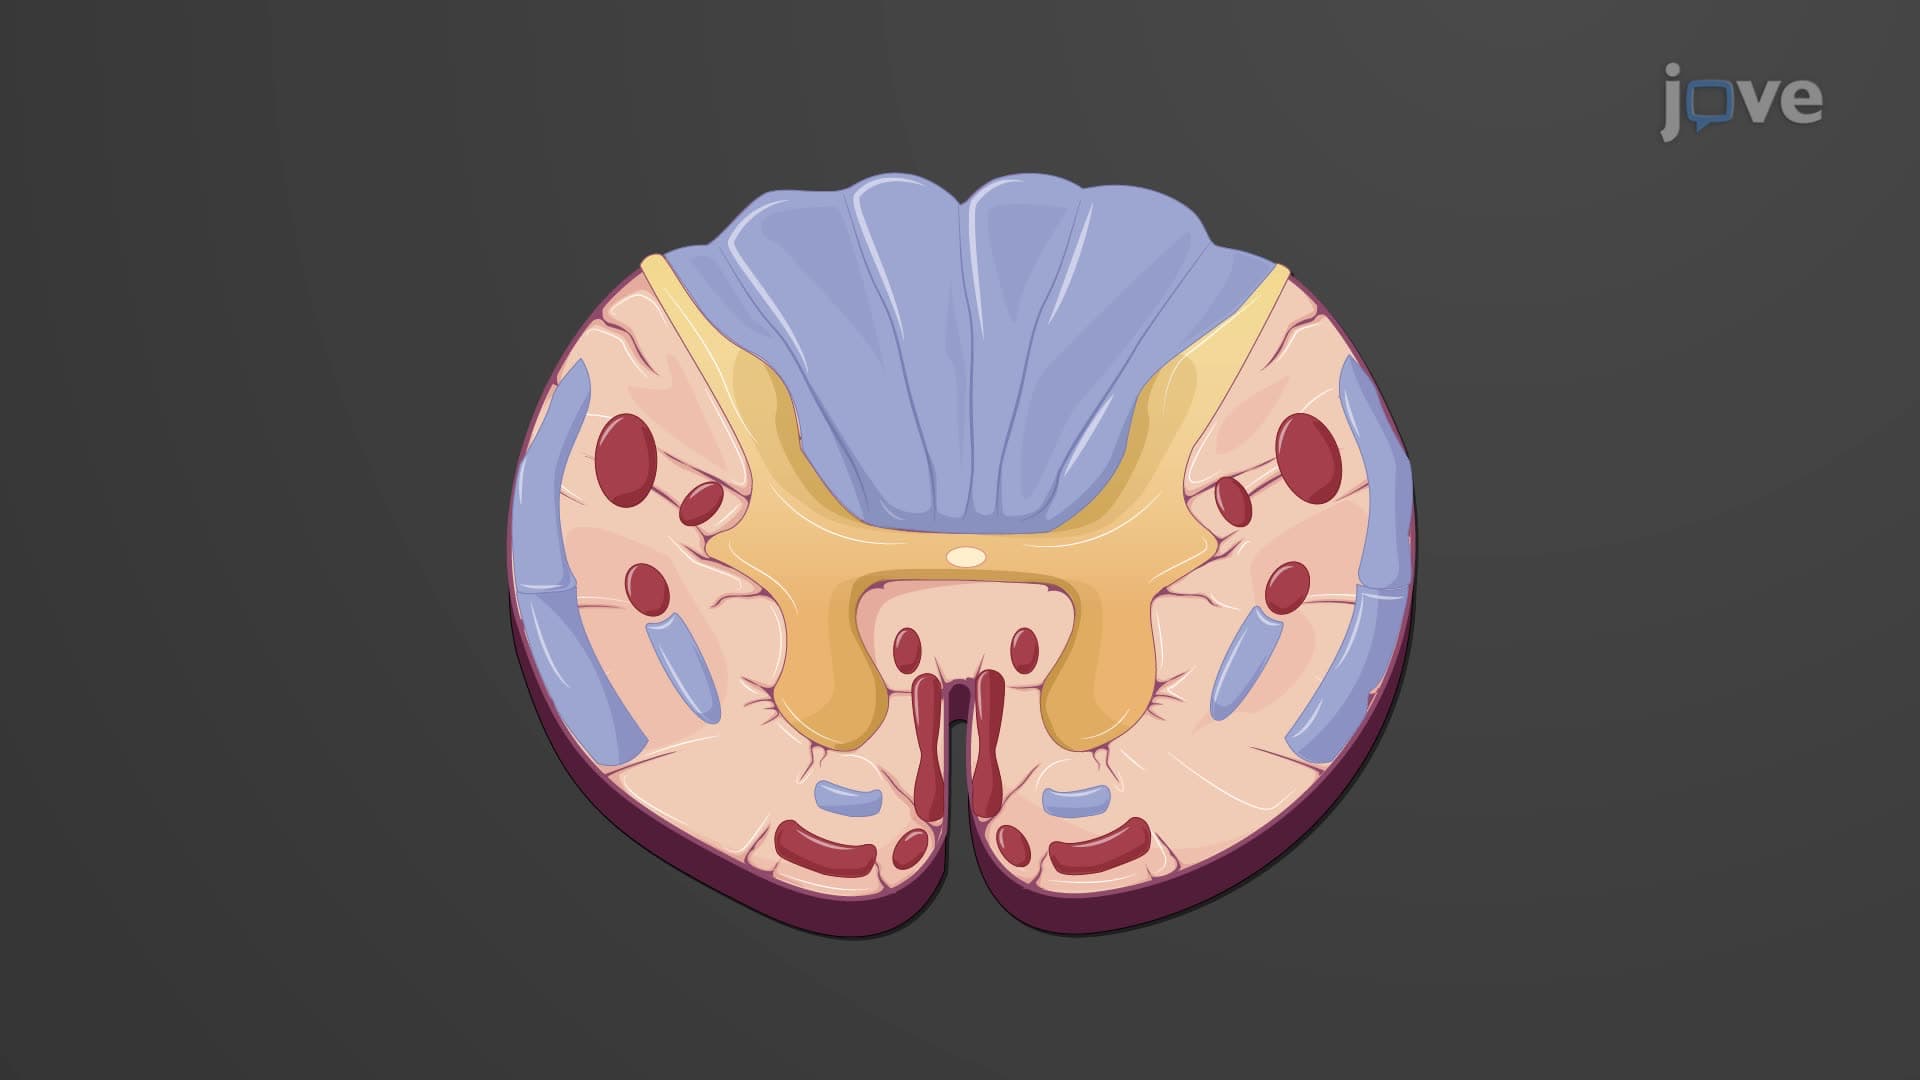
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 02:04
Conservation of Small Populations
 01:21
Perceiving Loudness, Pitch, and Location
Place theory, or place coding, suggests that different pitches are heard because various sound waves activate specific locations along the cochlea's basilar membrane. The brain determines the pitch of a sound by...