Related Experiment Video
Updated: Jan 31, 2026
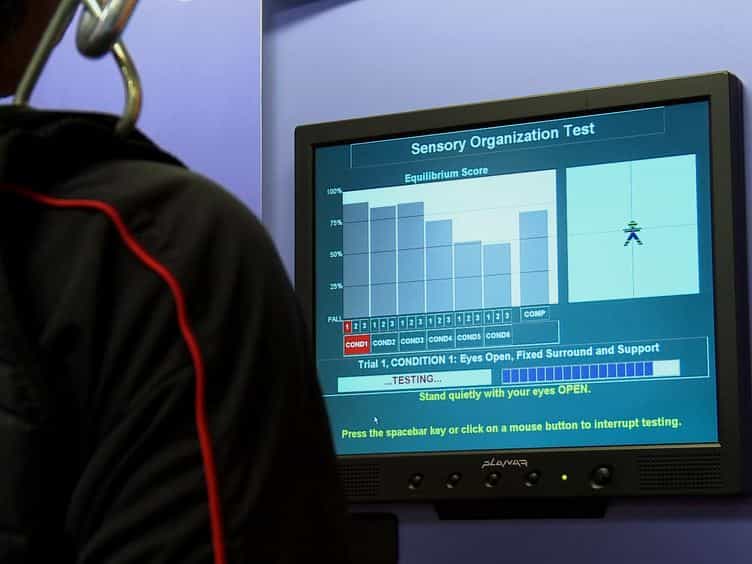
Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Ankle-brachial index in patients with intermittent claudication is a poor indicator of patient-centered and
Abigail L Johnston1, Sreekanth Vemulapalli2, Kensey L Gosch3
1Department of Medicine, Duke University School of Medicine, Durham, NC.

Background:
The association between the severity of ankle-brachial index (ABI), a traditional measure of the severity of peripheral artery disease (PAD), and patients' perceptions of their health status is poorly characterized. In Patient-Centered Outcomes Related to Treatment Practices in Peripheral Artery Disease: Investigating Trajectories (PORTRAIT), a study of patients with intermittent claudication (IC), we studied the correlation of ABI values and Rutherford symptom classification with PAD-specific health status as measured by the Peripheral Artery Questionnaire (PAQ).
Methods:
Among 1251 patients with new onset or exacerbation of IC enrolled at 16 sites in the United States, Netherlands, and Australia, ABI values were categorized as mild (>0.80), moderate (0.40-0.79), and severe (<0.40). Spearman rank correlation coefficients were calculated between raw ABI values and PAQ scores and between the Rutherford classification and PAQ scores.
Results:
Mean ABI was 0.67 (standard deviation, 0.19); 24.3% had mild, 67.6% moderate, and 8.1% severe PAD. According to the Rutherford classification, 22.7% were stage 1 (mild claudication), 49.5% stage 2 (moderate claudication), and 27.8% stage 3 (severe claudication). Correlations (95% confidence interval) were found between ABI and the PAQ summary score (r = 0.09 [0.04-0.15]) and the PAQ physical limitations score (r = 0.14 [0.09-0.20]); no correlations were found between ABI and the PAQ quality of life score (r = 0.03 [-0.02 to 0.09]) and the PAQ symptoms score (r = 0.04 [-0.01 to 0.10]). With the correlations between ABI and PAQ scores, ABI explained only 0.1% to 2.1% of the variation in PAQ scores. Rutherford classification had stronger but still modest associations with PAQ scores (PAQ summary, r = -0.27 [-0.21 to -0.32]; PAQ quality of life, r = -0.21 [-0.16 to -0.27]; PAQ symptoms, r = -0.18 [-0.13 to -0.23]; PAQ physical limitations, r = -0.27 [-0.22 to -0.32]); Rutherford class explained 3.2% to 7.3% of the variation in PAQ scores.
Conclusions:
In a large, international cohort of patients with IC, patient-centered health status assessments are weakly associated with physicians' or hemodynamic assessments. To best measure the impact of PAD on patients' symptoms, functional capacity, and quality of life, direct assessment from patients is needed, rather than relying on physiologic or clinician-assigned assessments.
More Related Videos
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
 07:51
Hydra, a Computer-Based Platform for Aiding Clinicians in Cardiovascular Analysis and Diagnosis
Published on: September 26, 2018
Related Concept Videos
 01:13
Patient-centered Care
 02:39
Indicators
 01:20
Nursing Process for Patient and Caregiver Teaching III: Evaluation and Documentation
Nurses can use several methods to evaluate patient outcomes. For example, oral questions can assess cognitive learning,...
 01:15
Drug Dosing: Geriatric Patients
 01:21
Drug Dosing: Obese Patients
 01:10
Ankle Joint