Related Experiment Video
Updated: Jan 30, 2026

Small Bowel Transplantation In Mice
Published on: August 20, 2007
Blunt small bowel perforation (SBP): An Eastern Association for the Surgery of Trauma multicenter update 15 years
Samir M Fakhry1, Ahmed Allawi, Pamela L Ferguson
1From the Department of Surgery, Reston Hospital Center, Reston, Virginia (S.M.F.); Department of Surgery, Medical University of South Carolina, Charleston, South Carolina (A.A., P.L.F.); Department of Surgery, Inova Fairfax Hospital, Falls Church, Virginia. (C.P.M., A.B.N., C.L.); and Department of Surgery, University of North Carolina, Chapel Hill, NC (M.R.B.).

Background:
Previous work demonstrated diagnostic delays in blunt small bowel perforation (SBP) with increased mortality and inability of scans to reliably exclude the diagnosis. We conducted a follow-up multicenter study to determine if these challenges persist 15 years later.
Methods:
We selected adult cases with blunt injury, International Classification of Diseases, Ninth Revision or current procedural terminology (CPT) indicating small bowel surgery, no other major injury and at least one abdominal computed tomography (CT) within initial 6 hours. Controls had blunt trauma with abdominal CT but not SBP. After institutional review board approval, data from each center were collected and analyzed.
Results:
Data from 39 centers (from October 2013 to September 2015) showed 127,919 trauma admissions and 94,743 activations. Twenty-five centers were Level 1. Centers submitted 77 patients (mean age, 39; male, 68%; mean length of stay, 11.3 days) and 131 controls (mean age, 44; male, 64.9%; length of stay, 3.6 days). Small bowel perforation cases were 0.06% of admissions and 0.08% of activations. Mean time to surgery was 8.7 hours (median, 3.7 hours). Initial CT showed free air in 31 cases (43%) and none in controls. Initial CT was within normal in three cases (4.2%) and 84 controls (64%). Five cases had a second scan; two showed free air (one had an initial normal scan). One death occurred among the patients (mortality, 1.4%; and time to surgery, 16.9 hours). Regression analysis showed sex, abdominal tenderness, distention, peritonitis, bowel wall thickening, free fluid, and contrast extravasation were significantly associated with SBP.
Conclusions:
Blunt SBP remains relatively uncommon and continues to present a diagnostic challenge. Trauma centers have shortened time to surgery with decreased case mortality. Initial CT scans continue to miss a small number of cases with potentially serious consequences. We recommend (1) intraperitoneal abnormalities on CT scan should always evoke high suspicion and (2) strong consideration of additional diagnostic/therapeutic intervention by 8 hours after arrival in patients who continue to pose a clinical challenge.
Level Of Evidence:
Observational study, level III.
Related Concept Videos
 01:16
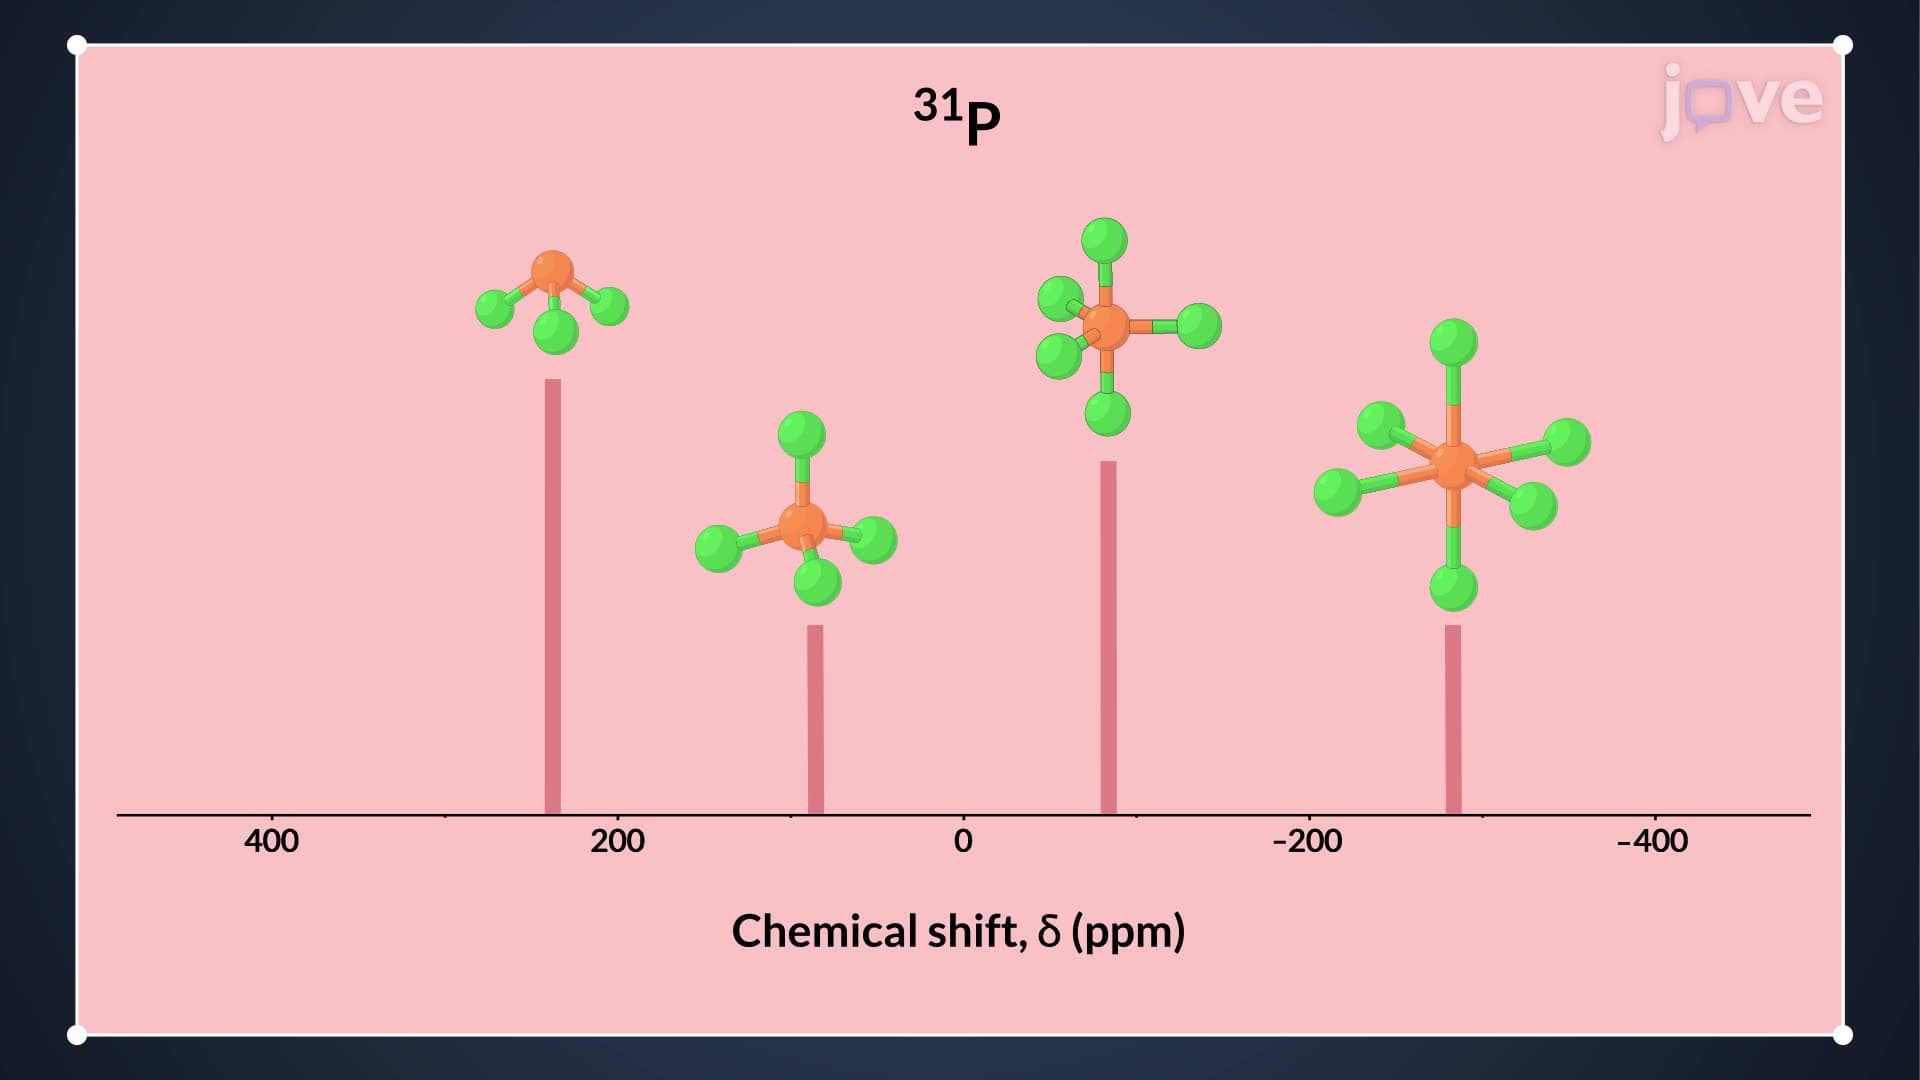
Other Nuclides: 31P, 19F, 15N NMR
While fluorine-19 and phosphorous-31 have high natural abundances (100%) and positive gyromagnetic ratios, nitrogen-15 has a low natural abundance and a negative gyromagnetic ratio. However, nitrogen-15 is still preferred over nitrogen-14 (which has a...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:21
Association Areas of the Cortex
Prefrontal Association Area: This area is located in the frontal lobe and is involved in planning, decision-making, and moderating social behavior. It connects with primary motor areas,...
 01:27
Associative Learning
Classical conditioning, also known...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...