Related Experiment Video
Updated: Jan 30, 2026


Handheld Metal Detector Screening for Metallic Foreign Body Ingestion in Children
Published on: September 11, 2018
Residual airway foreign bodies in children who underwent rigid bronchoscopy
Bin Xu1, Lei Wu2, Ziying Jin3
1Department of Otorhinolaryngology-head and Neck Surgery, Children's Hospital, Zhejiang University School of Medicine, China.

Insights
Residual airway foreign bodies in children are often caused by friable foods like nuts. Surgeon experience significantly impacts removal success rates, highlighting the need for skilled practitioners in rigid bronchoscopy procedures.
Area of Science:
- Pediatric Pulmonology
- Otolaryngology
- Surgical Outcomes
Background:
- Airway foreign bodies pose a significant risk to children.
- Rigid bronchoscopy is a common procedure for removal.
- Residual foreign bodies can lead to complications.
Purpose of the Study:
- To identify key factors contributing to residual airway foreign bodies after rigid bronchoscopy.
- To enhance the success rate of primary surgical interventions for pediatric airway foreign bodies.
Main Methods:
- Retrospective analysis of 1130 pediatric patients undergoing rigid bronchoscopy.
- Data collected on patient demographics, foreign body characteristics, and surgeon experience.
- Patients categorized into groups with and without residual foreign bodies based on post-procedure imaging and examination.
Main Results:
- A 2.7% residual foreign body rate was observed.
- Friable, food-related foreign bodies (especially nuts) were most common.
- Higher residual rates were associated with less experienced surgeons and specific bronchial locations.
Conclusions:
- The nature of the foreign body (friable foods), bronchial anatomy complexity, and surgeon experience are critical factors in residual airway foreign bodies.
- Experienced surgeons are crucial for successful rigid bronchoscopy outcomes.
- Chest CT and flexible bronchoscopy aid in confirming residual foreign bodies.
Objective:
To analyze the causes of residual airway foreign bodies in children who underwent rigid bronchoscopy in order to improve the success rate of primary surgery.
Methods:
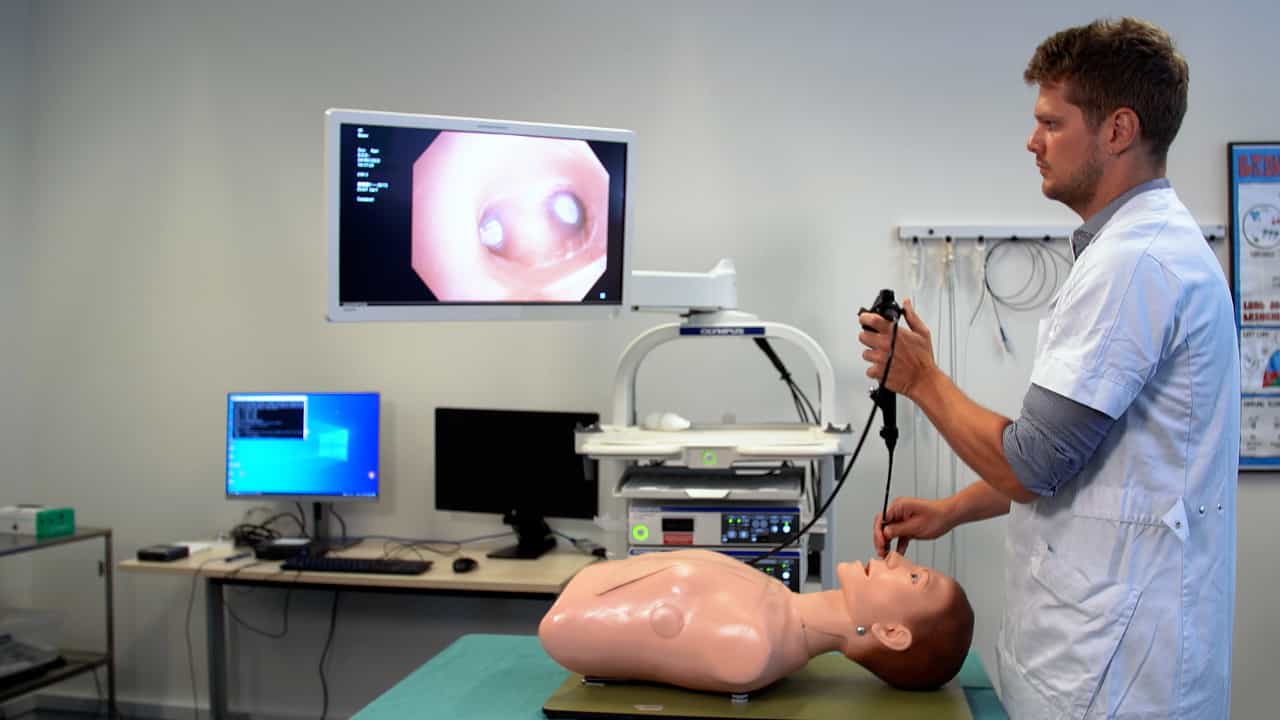
Clinical data from 1130 children with airway foreign bodies, including 736 males and 394 females aged 0.42-14 years, who underwent rigid bronchoscopy in our hospital from January 2015 to May 2018 were retrospectively collected and analyzed by cluster sampling. Clinical characteristics including sex, age, time of onset, location of the foreign body, type of foreign body and experience of surgeon were gathered. All patients were classified into two groups as Group A (with residual airway foreign bodies) and Group B (without residual airway foreign bodies) according to chest CT scans and fiberoptic bronchoscope examinations after rigid bronchoscopy. The values were compared between the two groups.
Results:
Thirty-one patients with residual foreign bodies were confirmed by fiberoptic bronchoscopy among 1130 children with airway foreign bodies who underwent rigid bronchoscopy under general anesthesia. The percentage of residual airway foreign body was 2.7%. The mean age was 1.55 ± 0.46 years (range 1-3 years). There were 24 male patients (77.4%), and 7 female patients (22.6%), with a male/female ratio of 3.43:1. The time of onset was 1.0 (interquartile range: 1.0-8.0) day. There were no significant difference in age, sex and time of onset between the two groups. Most residual foreign bodies were food-related: nuts (n = 27, 87.1%), beans (n = 3, 9.7%), and one case was unclear in nature (3.2%). The residual incidence of fragile foreign bodies was higher than non-friable foreign bodies (P = 0.028). The most common residual foreign body locations were left superior lobar bronchi (32.3%), left inferior lobar bronchi (25.8%) and right inferior lobar bronchi (25.8%). The residual rate of foreign bodies for surgeons with more than 5 years of operative experience was 1.92%, and 4.25% for surgeons with less than 5 years of operation experience, showing a significant difference (P = 0.022).
Conclusion:
Friable foods, the complicated structure of the bronchus tree and the surgeon's experience are important causes of residual foreign bodies in the airway. Surgeons with sufficient experience are important for the success of the procedure, which is supported by chest CT and flexible bronchoscopy.

Related Concept Videos
 00:49
Rigid Body Equilibrium Problems - I
 01:21
Rigid Body Equilibrium Problems - II
Consider two children sitting on a seesaw, which has negligible mass. The first child has a mass (m1) of 26 kg and sits at point A, which is 1.6 meters (r1) from the pivot point B; the second child has a mass (m2) of 32 kg and sits at point C. How far from the pivot point B should the second child sit (r2) to balance the seesaw?
 01:11
Angular Momentum: Rigid Body
This calculation can get complicated when tiny particles within the rigid body are not rotating in the same plane but have...
 01:06
Virtual Work for a System of Connected Rigid Bodies
Next,...
 01:13
Kinetic Energy for a Rigid Body
 01:12
Equation of Motion for a Rigid Body
The combined moments generated about the center of mass of the object are equal to the rate of change of the angular momentum of the body. An external force, when applied at a different...