Related Experiment Video
Updated: Jan 30, 2026
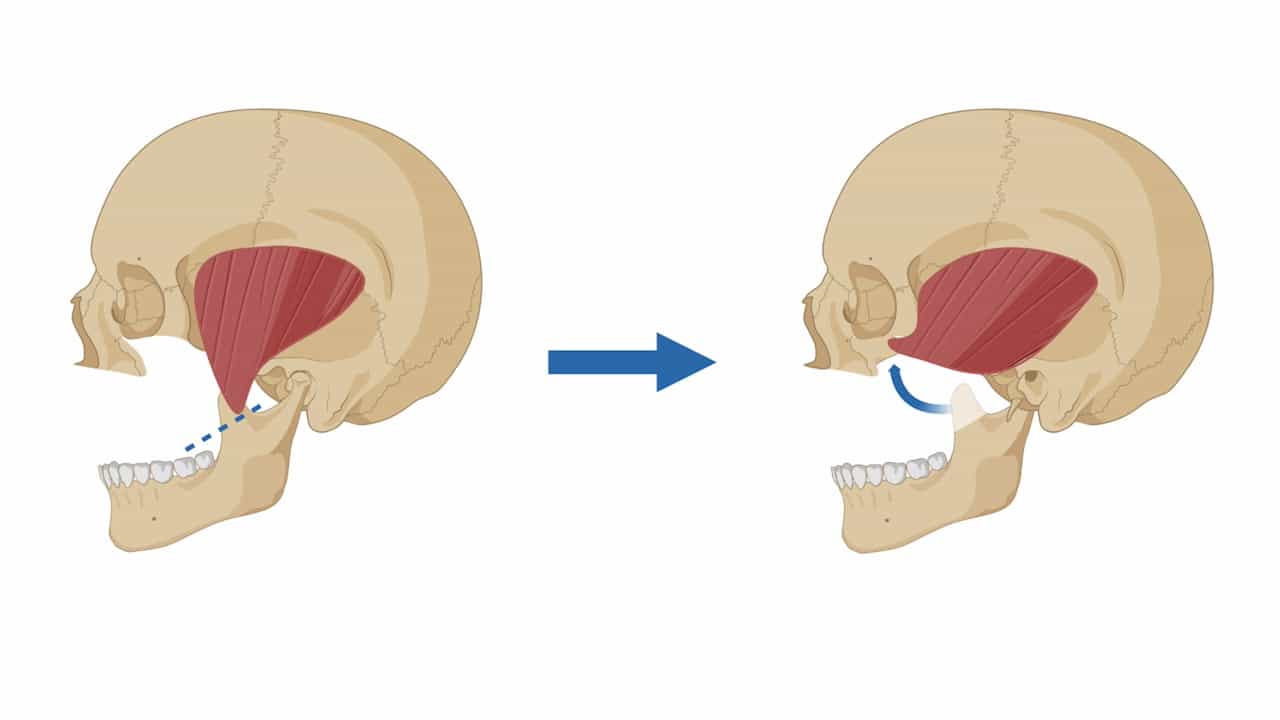

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Debunking a Surgical Myth: Do Not Touch the Temporalis
Katelyn G Bennett1, Russell E Ettinger1, Fan Liang2
1Section of Plastic Surgery, University of Michigan.

Background:
A longstanding dictum exists to avoid surgical manipulation of the temporalis muscle out of concern for an exceedingly high rate of muscle atrophy and recurrent temporal hollowing. The authors challenge this surgical myth, considering such advice to be erroneous. The authors hypothesize that elevation of the temporalis muscle, if performed using standard muscle flap principles, will demonstrate excellent results.
Methods:
To assess temporalis response to surgical manipulation, the authors reviewed patients who underwent calvarial vault remodeling by the senior author for craniosynostosis between 1988 and 2011. Nonsyndromic patients with single-suture synostosis and 5 years of follow-up were eligible for inclusion. The medical record was used to measure rates of reoperation, recurrent temporal hollowing, and persistent temporalis overcorrection.
Results:
Of the cohort reviewed, 196 patients met inclusion criteria. Ten patients (5.1%) exhibited recurrent bitemporal constriction. One patient (0.5%) underwent a revision temporalis turnover flap, and 2 patients (1.0%) underwent soft tissue augmentation. The overall reoperation rate was 1.5%. Temporalis overcorrection, in an attempt to prophylactically rectify the expected atrophy after temporalis manipulation, persisted in 11 patients (5.6%). Three of these patients required treatment with steroid injections, Botox injections, or operative muscle debulking. The overall reoperation rate for temporalis overcorrection was 1.5%.
Conclusions:
The authors' low reoperation rates for recurrent deformity, in combination with persistent temporalis overcorrection in 5.6% of patients, should dispel the myth that manipulation of the temporalis invariably results in atrophy. The muscle may be surgically manipulated, as long as plastic surgery principles are followed.
More Related Videos
Related Concept Videos
 02:26
Responses to Gravity and Touch
 01:15
Techniques of therapeutic communication I: Active Listening, Sharing Observations, Validation, and Using Touch
Therapeutic communication is not the same as social interaction. Social interaction has no goal or purpose and consists of casual information sharing, whereas therapeutic communication has a plan or purpose for the conversation. Therapeutic...
 01:26
Kidney Transplant II: Surgical Procedure
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease