Related Experiment Video
Updated: Jan 30, 2026

Non-invasive Optical Measurement of Cerebral Metabolism and Hemodynamics in Infants
Published on: March 14, 2013
Temporal Trends and Center Variation in Early Antibiotic Use Among Premature Infants
Dustin D Flannery1,2, Rachael K Ross1,3, Sagori Mukhopadhyay1,2
1Center for Pediatric Clinical Effectiveness, Children's Hospital of Philadelphia, Philadelphia, Pennsylvania.

Insights
Most premature infants receive early antibiotics, with little change over seven years. Wide variations in antibiotic use across hospitals highlight the need for better neonatal antimicrobial stewardship programs.
Area of Science:
- Neonatalogy
- Pediatric Infectious Diseases
- Health Services Research
Background:
- Premature infants often receive empirical antibiotic therapy at birth.
- Early and prolonged antibiotic exposure in infants without confirmed infections is linked to adverse outcomes.
Purpose of the Study:
- To analyze trends in early antibiotic use among premature infants over time.
- To assess variations in antibiotic administration across US hospitals.
Main Methods:
- Retrospective cohort study using a US administrative database.
- Included very low-birth-weight (VLBW) and extremely low-birth-weight (ELBW) infants surviving at least one day.
- Analyzed antibiotic initiation within 3 days and duration >5 days from 2009-2015.
Main Results:
- The majority of VLBW (78.6%) and ELBW (87.0%) infants received early antibiotics.
- No significant temporal changes in early antibiotic initiation were observed.
- A small decrease in prolonged antibiotic duration was noted for VLBW infants.
- Significant variation in antibiotic exposure rates existed across hospitals.
Conclusions:
- Empirical early antibiotic use is common in premature infants and has remained largely unchanged.
- Substantial inter-hospital variability in antibiotic exposure underscores the need for antimicrobial stewardship.
- Optimizing antibiotic use in VLBW and ELBW infants is crucial.
Importance:
Premature infants are frequently administered empirical antibiotic therapy at birth. Early and prolonged antibiotic exposures among infants without culture-confirmed infection have been associated with increased risk of adverse outcomes.
Objective:
To examine early antibiotic use among premature infants over time and across hospitals in the United States.
Design, Setting, And Participants:
This retrospective cohort study used a comprehensive administrative database of inpatient encounters from 297 academic and community hospitals across the United States to examine data concerning very low-birth-weight (VLBW) infants (<1500 g), including extremely low-birth-weight (ELBW) infants (<1000 g), who were admitted to the neonatal intensive care unit and survived for at least 1 day. Data collection took place in November 2015 and analysis took place from February 2016 to November 2016.
Exposures:
Antibiotic initiation within the first 3 days of age and subsequent antibiotic administration for more than 5 days.
Main Outcomes And Measures:
Temporal trends in early antibiotic initiation and duration from 2009 to 2015, and center variation in early antibiotic use from 2014 to 2015.
Results:
We identified 40 364 VLBW infants (20 447 female [50.7%]) who survived for at least 1 day, including 12 947 ELBW infants, from 297 centers. The majority of premature infants had early antibiotic initiation (31 715 VLBW infants [78.6%] and 11 264 ELBW infants [87.0%]), and no differences were observed over time in temporal trend analyses (P = .12 for VLBW and P = .52 for ELBW). The annual risk difference in the proportion of VLBW infants administered early antibiotic therapy ranged from -0.75% (95% CI, -1.61% to 0.11%) to -0.87% (95% CI, -2.04% to 0.30%); in ELBW infants the annual risk difference ranged from -0.34% (95% CI, -1.28% to 0.61%) to -0.38% (95% CI, -1.61% to 0.85%). There was a small but significant decrease over time in the rate of prolonged antibiotic duration for VLBW infants (P = .02), but not for ELBW infants (P = .22). The annual risk difference in the proportion of VLBW infants with prolonged antibiotic duration ranged from -0.94% (95% CI, -1.65% to -0.23%) to -1.08% (95% CI, -2.00% to -0.16%); in ELBW infants the annual risk difference ranged from -0.72% (95% CI, -1.83% to 0.39%) to -0.75% (95% CI, -1.96% to 0.46%). We also observed variation in early antibiotic exposures across centers. Sixty-nine of 113 centers (61.1%) started antibiotic therapy for more than 75% of VLBW infants, and 56 of 66 centers (84.8%) started antibiotic therapy for more than 75% of ELBW infants. The proportion of VLBW and ELBW infants administered prolonged antibiotics ranged from 0% to 80.4% and 0% to 92.0% across centers, respectively.
Conclusions And Relevance:
Most premature infants in this study received empirical early antibiotic therapy with little change over a recent 7-year period. The variability in exposure rates across centers, however, suggests that neonatal antimicrobial stewardship efforts are warranted to optimize antibiotic use for VLBW and ELBW infants.

Related Concept Videos
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 00:57
Antibiotic Selection
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:19
Variation
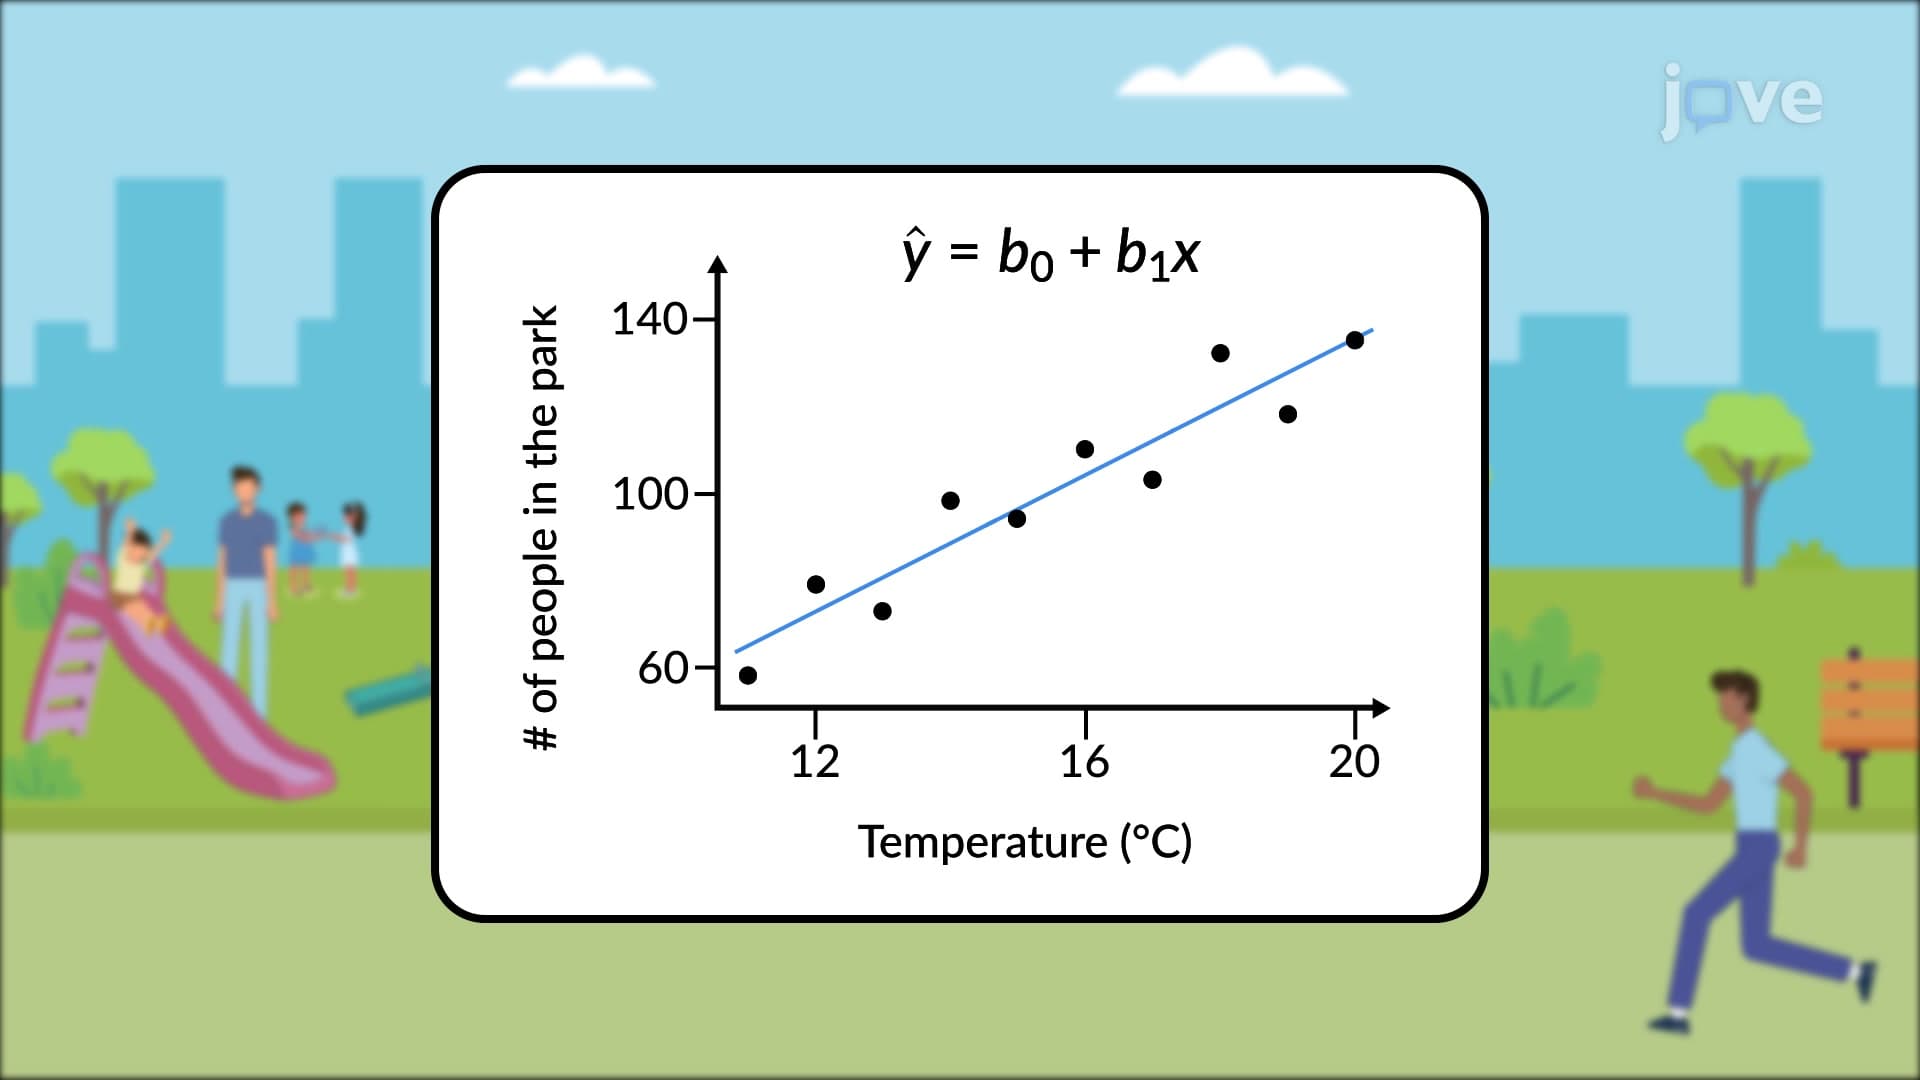
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 01:28
Current Trends in Nursing I
 01:30
Current Trends in Nursing II