Related Experiment Video
Updated: Jan 30, 2026

Laparoscopic Anatomical Hepatectomy Using Takasaki's Approach and Indocyanine Green Fluorescence Navigation
Published on: May 16, 2025
Donor Risk Index Has an Impact in Intraoperative Measure of Hepatic Artery Flow and in Clearance of Indocyanine
P Lozano1, M I Orue-Echebarria1, J M Asencio1
1Liver Transplant Unit, Hospital Universitario Gregorio Marañón de Madrid, Madrid, Spain; Faculty of Medicine, Universidad Complutense de Madrid, Madrid, Spain.

Background:
The increase in indications for liver transplantation has led to acceptance of donors with expanded criteria. The donor risk index (DRI) was validated with the aim of being a predictive model of graft survival based on donor characteristics. Intraoperative arterial hepatic flow and indocyanine green clearance (plasma clearance rate of indocyanine green [ICG-PDR]) are easily measurable variables in the intraoperative period that may be influenced by graft quality. Our aim was to analyze the influence of DRI on intraoperative liver hemodynamic alterations and on intraoperative dynamic liver function testing (ICG-PDR).
Methods:
This investigation was an observational study of a single-center cohort (n = 228) with prospective data collection and retrospective data analysis. Measurement of intraoperative flow was made with a VeriQ flowmeter based on measurement of transit time (MFTT). The ICG-PDR was obtained from all patients with a LiMON monitor (Pulsion Medical Systems AG, Munich, Germany). DRI was calculated using a previously validated formula. Normally distributed variables were compared using Student's t test. Otherwise, the Mann-Whitney U test or Kruskal-Wallis test was applied, depending on whether there were 2 or more comparable groups. The qualitative variables and risk measurements were analyzed using the chi-square test. P < .05 was considered statistically significant.
Results:
DRI score (mean ± SD) was 1.58 ± 0.31. The group with DRI >1.7 (poor quality) had an intraoperative arterial flow of 234.2 ± 121.35 mL/min compared with the group having DRI < 1.7 (high quality), with an intraoperative arterial flow of 287.24 ± 156.84 mL/min (P = .02). The group with DRI >1.70 had an ICG-PDR of 14.75 ± 6.52%/min at 60 minutes after reperfusion compared to the group with DRI <1.70, with an ICG-PDR of 16.68 ± 6.47%/min at 60 minutes after reperfusion (P = .09).
Conclusion:
Poor quality grafts have greater susceptibility to ischemia-reperfusion damage. Decreased intraoperative hepatic arterial flow may represent an increase in intrahepatic resistance early in the intraoperative period.
Related Concept Videos
 01:09
Hepatic Drug Clearance: Restrictive and Nonrestrictive Clearance
Most drugs undergo restrictive clearance, which is proportional to the...
 01:14
Hepatic Drug Clearance: Role of Transporters
 01:09
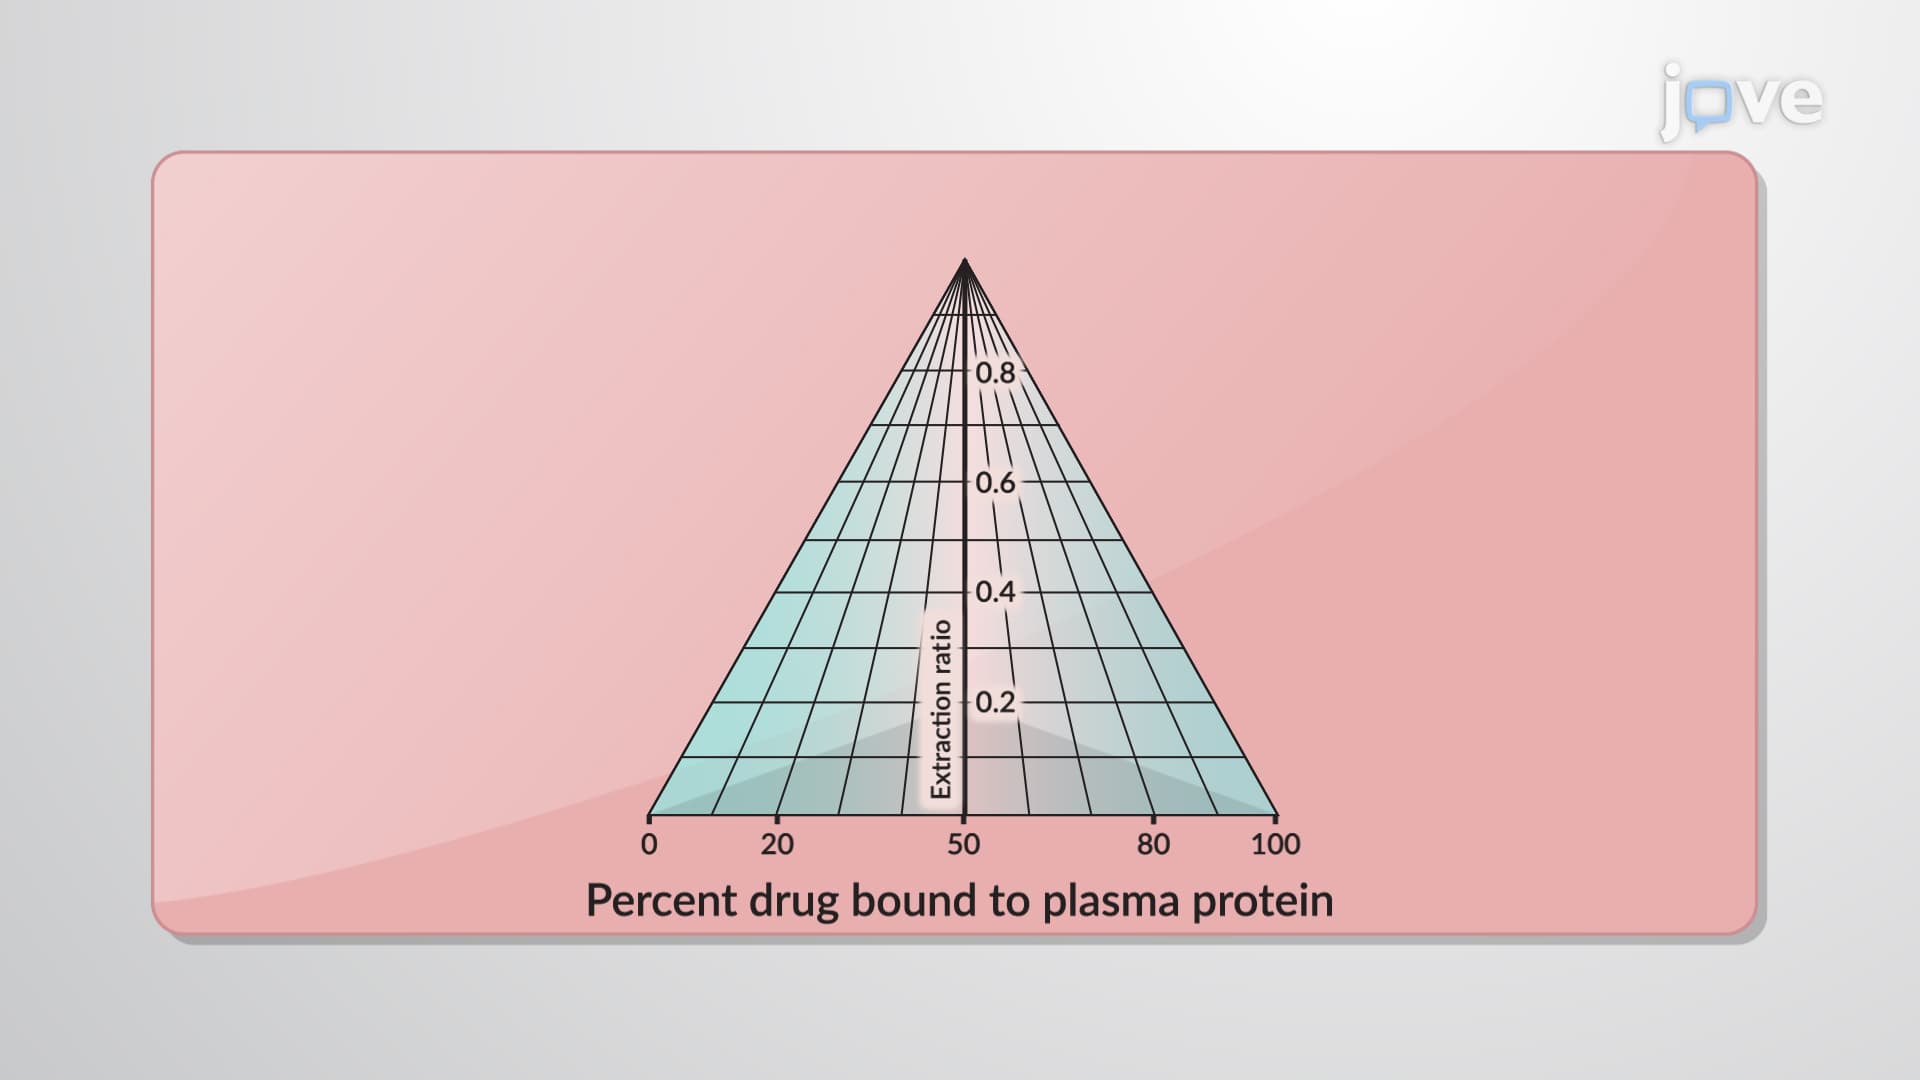
Hepatic Drug Clearance: Effect of Protein Binding
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:11
Observational Studies
There are three types of observational studies – Prospective, retrospective, and cross-sectional.
Prospective Study
Prospective studies, also known as longitudinal or cohort studies, are carried out by collecting future data from groups sharing similar characteristics. One...
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion,...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow